Oct 1, 2026 | TPC Global, Volume 16 - Issue 3
Godfrey Ddungu, Corinne W. Bridges, Cynthia A. Briggs
HIV/AIDS is the most stigmatized health condition globally, yet few studies have explored the needs of rural Ugandans diagnosed with HIV/AIDS. Uganda is one of the countries most affected by the AIDS pandemic and has an adult HIV prevalence of over 6.2% (UNAIDS, 2021). This transcendental phenomenological study revealed the lived experiences of women and men diagnosed with HIV in rural Uganda, and examined mental health counseling concerns. In-depth semi-structured interviews provided the data for this study. Three major themes emerged: (a) existential threat post–HIV/AIDS diagnosis, (b) resources relative to HIV/AIDS diagnosis, and (c) support from families and friends post–HIV diagnosis. The results of this study confirm a need for greater attention to and increased mental health support for people living with HIV/AIDS in rural Uganda, which may inform training strategies and support services in counselor education programs.
Keywords: HIV/AIDS, rural Uganda, existential threat, resources, counselor education
Although HIV/AIDS is a manageable chronic condition, people diagnosed with HIV/AIDS in Uganda continue to face reduced life expectancy, higher risk for comorbidities, and declines in quality of life (Li et al., 2018; Nasi et al., 2017). The fact that people living with HIV/AIDS (PLWHA) experience higher levels of comorbidity with mental health diagnoses, including depression, anxiety, and suicidal thoughts, is particularly relevant to counselors, as isolation, stigma, and difficulty accessing mental health services can exacerbate these concerns (National Institutes of Health, 2024). Disproportionate rates of HIV/AIDS diagnoses in some African countries, such as Uganda, make mental health concerns even more prevalent.
HIV statistics from the Uganda AIDS Commission (2020, 2022) showed that approximately 1.4 million people were living with HIV in Uganda, with women disproportionately affected. There, women are twice as likely to acquire HIV/AIDS than men are. National HIV surveillance data indicate that in 2021, about 54,000 new diagnoses were recorded, with the highest among young people aged 15–24 years (Obeagu & Obeagu, 2024; Uganda Ministry of Health, 2022). By comparison, the United States reports over 1 million people living with HIV (Centers for Disease Control and Prevention [CDC], 2021), while the burden of HIV in Uganda is much higher relative to population size and disproportionately affects rural communities.
HIV/AIDS in Uganda mirrors global and regional disparities. The Joint United Nations Programme on HIV/AIDS (UNAIDS, 2020) reported that of the 38 million people living with HIV worldwide, Eastern and Southern Africa accounted for 20.7 million, with Uganda being one of the most heavily affected countries. Within Uganda, HIV prevalence varies by demographic group, gender, sexual orientation, and geography, with rural populations experiencing challenges in testing, treatment access, and stigma (Akatukwasa et al., 2021). These rural disparities are echoed in parts of the United States where geographic isolation, poverty, and stigma similarly restrict access to care (De Jesus & Williams, 2018).
Uganda has made important progress in addressing HIV/AIDS through prevention, treatment, and care programs. The scale-up of antiretroviral therapy (ART) has been central to that progress; by 2020, approximately 84% of Ugandans living with HIV were on ART, and 75% had achieved viral suppression (UNAIDS, 2021). Akatukwasa et al. (2021) asserted that widespread HIV counseling and testing campaigns, prevention of mother-to-child transmission initiatives, and community-based outreach programs have significantly reduced AIDS-related deaths. Yet, challenges remain, including particularly low rates of testing among men and adolescents, delays in care engagement, and pervasive HIV-related stigma (Akatukwasa et al., 2021).
Stigma continues to pose barriers to care in Uganda. Kitara and Aloyo (2012) reported that many people living with HIV avoid seeking services because of conservative attitudes and discriminatory legislation. Hladik et al. (2017) studied HIV and psychosocial risk among men who have sex with men in Kampala, Uganda, and found that 40% of participants reported experiencing homophobic abuse and 44.5% reported lifetime suicidal ideation. Such stigma contributes to social isolation, mental health strain, and decreased adherence to ART (Kalichman et al., 2017). Despite their recognition as major problems in eradicating the HIV epidemic, few countries have prioritized reducing or eliminating stigma and discrimination in their national programs (Kumar et al., 2017). Counselors working in rural Uganda must therefore understand the complex intersections of stigma, mental health, and medical adherence in order to provide effective support. In sum, despite Uganda’s progress in expanding access to ART and reducing AIDS-related deaths, HIV/AIDS remains a major public health, mental health, and counseling concern. The persistence of new diagnoses, the disproportionate impact on young people and women, and ongoing stigma highlight the need for integrated biomedical, psychosocial, and community-based interventions.
Mental Health and HIV/AIDS
Rates of mental health issues among vulnerable populations whose members acquire HIV/AIDS are high when compared to the general population (Remien et al., 2019). An estimated 63% of people living with HIV have a mental health disorder, compared to 31% for people without HIV/AIDS (Byrd et al., 2020). People who have HIV/AIDS experience higher rates of mental health issues and mental health impairment, and those experiencing mental health issues have an increased risk of acquiring HIV/AIDS (Remien et al., 2019).
PLWHA experience higher rates of external and internal stigma in rural areas than they do in urban areas, which can affect all areas of individuals’ lives (Akatukwasa et al., 2021; Breslow & Brewster, 2020; Li et al., 2018). For instance, PLWHA in Uganda and Kenya deferred marriage and childbearing, distanced themselves from friends and family members, and avoided seeking treatment because of internalized stigma (Akatukwasa et al., 2021; Breslow & Brewster, 2020). Additionally, stigmatization and disease progression of HIV/AIDS have contributed to psycho-emotional disturbances, job losses, poverty, dependence, moving in with relatives, and concerns about strain on or disruption of relationships and families (Setlhare et al., 2014).
Mental Health Treatment Challenges in Rural Uganda
Rural African communities of Uganda face unique considerations related to the retention of patients for continuation of care and ongoing treatment of PLWHA. In much of rural Uganda, communities are dispersed across villages, with limited access to healthcare facilities and reliable transportation. Daily life is heavily influenced by subsistence farming, extended family networks, and communal living, which shape how health services are perceived and accessed. Mental health services are not widely integrated into community health systems, and discussions of mental illness often carry cultural stigma (Akatukwasa et al., 2021).
Although mental health counseling services are an important tool in HIV/AIDS treatment across Africa, fewer than 50% of PLWHA utilize HIV testing and mental health counseling services. Many avoid them because of fears of confidentiality breaches, social stigma, and discrimination associated with being HIV positive (Ijeoma et al., 2018; Kiene et al., 2015). In rural Uganda, people often rely on traditional healers or faith-based approaches before seeking biomedical or psychological care, which further complicates the uptake of evidence-based interventions. The limited availability of culturally appropriate evidence-based mental health interventions may undermine efforts to address the interconnected mental health and HIV treatment needs of PLWHA (Nakimuli-Mpungu et al., 2021). Consequently, counselors working in these areas often have few established models to draw upon that account for the cultural and social dynamics of rural Ugandan life.
The social realities of rural Uganda such as poverty, gender inequality, limited education, and fear of social rejection exacerbate the HIV epidemic and make eradication difficult. Yet, research shows that PLWHA who receive treatment services, including mental health care, are significantly more likely to live longer than 10 years compared to those who do not receive treatment services (Poorolajal et al., 2016). Reduced adherence to medication is strongly associated with stigma, discrimination, and worsening health outcomes (Costelloe et al., 2015; Kalichman et al., 2017). HIV/AIDS-related stigma operates at multiple levels of society—individual, family, community, and institutional—and is rooted in fear of death, rejection, and denial (Kumar et al., 2017).
Although existing research indicates that PLWHA in rural Uganda experience significant mental health challenges, including depression, stigma, and limited access to care, and that mental health services are often under-resourced, the literature has primarily focused on structural barriers and policy-level integration rather than individual experiences. What remains insufficiently understood is how PLWHA themselves perceive and make meaning of their lives and mental health counseling. This lack of insight into PLWHA’s lived experiences represents a critical gap in the literature. Therefore, our study employs a phenomenological design to explore the lived experiences of PLWHA in rural Uganda, with the aim of generating contextually grounded knowledge to inform more culturally appropriate and effective mental health counseling practices.
Purpose of the Study
The purpose of our qualitative transcendental phenomenological study was to describe the lived experiences of PLWHA in rural Uganda. According to Husserl (1931), transcendental researchers must strictly suspend attitudes, beliefs, and suppositions to capture the pure experiences of participants. Understanding the pure essence of the lived experiences of PLWHA in rural Uganda can provide deep insights into the intricacies of the HIV problem and the mental health counseling concerns for PLWHA. Our study was guided by the research question: What are the lived experiences of rural Ugandans diagnosed with HIV/AIDS? And the sub-question: How do rural Ugandans experience stigma in relation to their HIV/AIDS diagnosis?
Method
Transcendental phenomenology involves viewing knowledge as coming from outside participants’ immediate awareness (Giorgi, 2012a) and encourages researchers to suspend preconceived judgments of the phenomenon and adopt epoché or bracketing (Moustakas, 1994). Bracketing allows researchers to view the data with a fresh perspective without bias and to gain a broader understanding of the experiences of the population (Shelton & Bridges, 2022). In this qualitative approach, there is an alignment between the what, or noema, of the experience and how something is experienced, or the noesis (Sloan & Bowe, 2014). Grounded in phenomenology, the guiding framework for our study, this approach explores a shared phenomenon by examining how participants perceive, interpret, and make meaning of their experiences (Peoples, 2021).
Positionality
First Author
Our article stems from the dissertation research of Godfrey Ddungu. I (Ddungu) am originally from rural Uganda. My positionality is inseparable from the knowledge produced in this study. Coming from rural Uganda and having counseled PLWHA, I carry an insider’s understanding of how stigma, poverty, and gendered expectations shape health-seeking practices. Yet, these same experiences intersect with forms of privilege, education, institutional affiliation, and mobility that position me differently from the participants. This dual position as both insider and outsider creates possibilities for empathy but also introduces interpretive blind spots that need to be acknowledged.
Critical reflexivity requires that I remained attentive to how gendered and cultural norms not only shaped participants’ narratives but also structured my questions and interpretations (Mi Choi & Hyun, 2023). Although my background may predispose me to highlight women’s struggles for autonomy in healthcare access, it risks obscuring the less visible pressures on men to suppress vulnerability. To navigate these dynamics, I approached the research with humility, conscious of power asymmetries (Koskinen, 2025), and sought to create dialogical spaces that validated participants’ agency. Situating myself explicitly within the research process reflected a methodological and ethical stance: recognizing that all knowledge is co-constructed through relations of power, culture, and positionality.
Corinne W. Bridges and Cynthia A. Briggs served on my dissertation committee as research and content experts. Additionally, we are all licensed counselors with doctoral degrees in counselor education and supervision and have expertise in qualitative methods.
Procedure
The Walden University Institutional Review Board approved this study following a comprehensive ethical review of the research questions, data collection instruments, and data analysis procedures. I provided detailed descriptions of participant recruitment and data collection processes to ensure that potential risks to privacy and participant safety were minimized and appropriately managed. Because the study was conducted outside the United States, I assumed responsibility for understanding and complying with applicable human subjects protection laws in Uganda. I completed the Collaborative Institutional Training Initiative certification in order to ensure adherence to international research standards and listed Walden University as the affiliated institution.
Following IRB approval, purposive criterion sampling was used to recruit participants. Informed consent was obtained both verbally and in writing, with participants fully apprised of the study’s purpose, procedures, potential benefits and risks, and their rights to confidentiality and voluntary participation. Maintaining confidentiality was an ongoing process throughout the study. The research team retained exclusive access to all study files, with each participant assigned a pseudonym linked to their consent forms, audio recordings, transcripts, and related data. All electronic files were securely stored and password-protected in Dropbox. As a gesture of appreciation, participants received a USD $10 food voucher for their participation. Additionally, participants provided self-reported demographic information at the beginning of each interview (see Table 1).
Table 1
Participant Demographic Information
|
Participant
|
Age |
Marriage status |
Number of children |
Employment status |
Number of years with diagnosis |
Education level |
Sex |
|
Angella
|
32 |
Married |
8 |
Unemployed |
13 |
Grade 4 |
Female
|
|
Emma
|
35 |
Married |
2 |
Unemployed |
7 |
Grade 5 |
Male |
|
Eva
|
45 |
Unmarried |
3 |
Unemployed |
16 |
Grade 4 |
Female
|
|
Immaculate
|
44 |
Unmarried |
7 |
Unemployed |
16 |
Grade 3 |
Female
|
|
Joseph
|
45 |
Divorced |
4 |
Employed |
5 |
Grade 5 |
Male
|
|
Lucy
|
39 |
Unmarried |
5 |
Unemployed |
11 |
Grade 5 |
Female
|
|
Maria
|
45 |
Unmarried |
6 |
Unemployed |
16 |
Grade 4 |
Female
|
|
Teo
|
35 |
Unmarried |
7 |
Employed |
1 |
Grade 5 |
Female
|
Participants
All participants met the following inclusion criteria: adult participants between the ages of 18 and 45 who had been diagnosed with HIV and had contacted the AIDS clinic center in a rural village of the Luweero district, Uganda. Six of the eight participants were female and two were male. In accordance with Moustakas (1994), an electronic flyer and request for participants was sent to the director of the health center that outlined the purpose, criteria, time commitment, confidentiality, and incentives. Although there is no set sample size for a qualitative study, the sample size should be able to provide data saturation. Saturation is a core methodological principle in qualitative research, referring to the point at which no new data, themes, or codes emerge and recurring patterns are observed (Creswell & Creswell, 2018; Peoples, 2021; Shelton & Bridges, 2022). It is not defined by sample size alone but represents an analytic judgment shaped by the study’s aims, sample characteristics, and depth of inquiry (Fusch & Ness, 2015; Lim, 2026). Saturation is achieved when data are sufficient to support replication and additional collection yields no new insights, meaning that even small, homogeneous samples may reach saturation when thematic redundancy occurs (Creswell & Creswell, 2018; Fusch & Ness, 2015; Lim, 2026). To ensure saturation, we used a sample range of six to 10; saturation was achieved at eight participants.
Data Collection Measures
The data for this study were collected through semi-structured, face-to-face individual interviews with PLWHA who shared their lived experiences. Ddungu served as the primary instrument (Giorgi, 1997). Ddungu scheduled a 30-minute session with each participant to review the informed consent, discuss details such as confidentiality, permission to record the interview, and the participants’ right to voluntarily withdraw from the study.
All participants agreed to one 90-minute face-to-face semi-structured interview at a healthcare center, which provided safety and security for participants. A semi-structured interview protocol allowed for open-ended questions with follow-up questions to collect the most accurate textual and rich data of what participants experienced and their structured descriptions of how they experienced the phenomenon (Giorgi, 2009; Moustakas, 1994). All eight interviews were audio recorded and conducted in Luganda. Ddungu, who is bilingual in English and Luganda, ensured the completeness of meaning rather than word-for-word translation. After completing the Luganda transcripts, the texts were translated from Luganda into English. To ensure the accuracy of translation and avoid bias, the English and Luganda transcripts were examined by a secondary bilingual reviewer. To ensure the accuracy of the analysis and reduce researcher bias, we used memos to record immediate impressions and performed reflexive journaling (Chan et al., 2013).
Trustworthiness
Qualitative researchers promote trustworthiness in their work by safeguarding the credibility and confirmability of their methods and findings (Cope, 2014). Trustworthiness was ensured through strategies addressing credibility, confirmability, dependability, and transferability (Cope, 2014). Credibility was upheld through prolonged engagement with the data, including repeated readings of interview transcripts and systematic coding, as well as the use of verbatim participant quotations to maintain a clear connection between participants’ perspectives and the findings. Confirmability was achieved by maintaining a detailed audit trail documenting our methodology, and through reflexive journaling to bracket researcher assumptions and reduce bias. Dependability was supported by providing a transparent and thorough description of the research design, data collection procedures, and allowing other researchers to follow and evaluate the consistency of the process over time (Korstjens & Moser, 2018). Transferability was addressed through rich descriptions of the research context, setting, and participant characteristics, enabling readers to determine the applicability of the findings to other contexts (Peoples, 2021). We adhered to Giorgi’s descriptive phenomenological method (Giorgi et al., 2017) to ensure methodological rigor and consistency, and, in line with this approach, we did not conduct member checking because it could undermine the goals of the study and is not considered a universal test of accuracy (Giorgi et al., 2017; Shelton & Bridges, 2022).
Data Analysis
Phenomenological interviewing emphasizes the description of lived experiences; it is crucial to gather data through the perspective filter that provides a concrete understanding of the phenomenon (Peoples, 2021). Our goal for data analysis was to interpret the data with faithfulness and describe the meaning of an experience through emergent themes (Giorgi, 2009; Shelton & Bridges, 2022). We adopted the concept of bracketing throughout the data collection and analysis. To analyze the transcripts, we employed Giorgi’s descriptive phenomenological psychological method, which involves five steps (Giorgi et al., 2017). I adopted the concept of bracketing as I developed the interview questions, explored my personal experiences as someone who grew up in Uganda, and transcribed and analyzed the data that I collected (Chan et al., 2013).
I analyzed the data following the approach outlined by Giorgi et al. (2017). This process began with a thorough reading of each transcript to gain an overall understanding of the whole experience. I then adopted a phenomenological psychological reduction to bracket the natural attitude and focus on the phenomena as they were experienced. Next, the transcripts were broken down into smaller meaning units to facilitate analysis. These meaning units were subsequently transformed into phenomenologically and psychologically informed descriptions, with some units requiring multiple levels of transformation while others required only one. Finally, I organized these transformed meanings into a coherent general structure that captured the essence of the experience.
Results
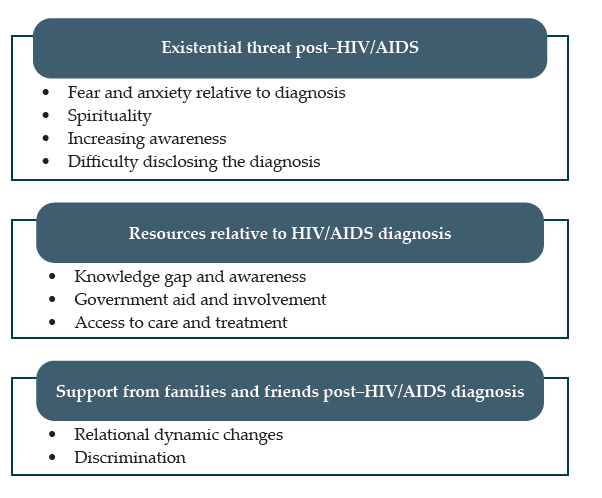
The meaning units discovered illuminated the following emergent themes: existential threat post HIV/AIDS, resources relative to HIV/AIDS diagnosis, and support from families and friends post–HIV diagnosis. Within each of the themes, subthemes emerged (see Figure 1).
Figure 1
Themes Derived From the Data
Existential Threat Post–HIV/AIDS Diagnosis
All participants shared heightened awareness of death and a sense of meaninglessness of life after receiving their HIV/AIDS diagnosis. They expressed their need to see beyond the diagnosis and hold onto something bigger and still contribute to the family, society, and self. Subthemes including fear and anxiety, spirituality, increasing awareness, and difficulty disclosing diagnosis emerged.
Fear and Anxiety Relative to Diagnosis
The lack of support through government resources in rural areas of Uganda added to the participants’ fear of disclosing their HIV status, as such disclosure could lead to discrimination, a disruption of their relationships, or even abandonment. All participants experienced a state of deep anxiety and worry post-diagnosis. For example, Teo reported that at 7 months pregnant, she went in for “a routine blood check for my pregnancy. It was found that I had the virus. I was scared and feared for my life and the life of the baby.”
Fear and anxiety were exacerbated by lack of knowledge and misconceptions about HIV transmission. Some of the participants worried, for example, that HIV could be transmitted through sharing eating utensils or drinking out of the same cup. Three out of eight participants shared their feelings of fear of transmitting the disease to their relatives, which led to them taking hygiene measures to ensure family safety. Maria stated, “I told my family not to use the utensils I was using to eat or mix them when washing out of fear of infecting the family members with the virus. I wanted to isolate myself to protect my family.”
Others shared their anxiety and fear because they transmitted HIV to their children during birth. Eva expressed her worry, stating, “I do not know if my son will ever love me.” Participants’ accounts revealed that awareness of their HIV-positive status, combined with internalized community stigma, deeply intensified their emotional burden. As a result, many struggled significantly with disclosing their HIV status.
Spirituality
The need to connect with God was expressed by most of the participants. Spirituality was described as playing an important role in helping them cope with feelings of fear and suffering following their HIV diagnosis (Sulung & Asyura, 2019). Six out of eight participants expressed a strong belief in God, which was considered a constant source of coping, strength, and hope that helped them come to terms with the virus. For example, Teo explained the presence of God in her life:
God has been good to me, and I’ve not been sick lately. I take my medication daily and I make sure I eat after taking medication. I wake up, go to the gardens morning and evenings to support my children and myself.
Lucy also shared how she experienced daily psychological distress and symptoms of depression because of her HIV-positive diagnosis. She explained that her faith in God enables her to remain strong for her family. She stated, “I tell my children every day that God knows our lives. God has helped me, and I have not gotten sick or had symptoms of the disease. Having these symptoms would scare my children. I am grateful to God.”
Teo’s and Lucy’s stories show how their connection to spirituality provided them with strength and hope in coping with their diagnosis. This indicates the importance of spirituality as a resilience resource that the participants used to overcome the challenges of living with HIV/AIDS. The ability to see beyond the diagnosis, hold onto something bigger, and contribute to family and society were important to them.
Increasing Awareness
The participants in our study expressed a strong desire to share their experiences with healthcare providers, the government, and the wider community, including mental health challenges, the need to refrain from sexual activity, the importance of taking medication as directed, and how the support of government resources can help people living with HIV/AIDS. Some participants explained how living with HIV/AIDS caused feelings of depression. Joseph said:
The government celebrating the AIDS Day should also involve the people living with HIV/AIDS in rural areas. We are not called to participate in this event, and yet this could be an opportunity for us to share our stories and have our ideas and experiences be heard. If the government gets involved and supports people with HIV/AIDS in rural areas to access mental health counseling services, this could improve our health and stop being depressed and stressed out all the time in our villages.
For Joseph, it was important for PLWHA to take an active role in their own care and for mental health professionals and the government to understand mental health concerns relative to the diagnosis. Joseph’s words were intended to increase awareness and support for PLWHA.
Difficulty Disclosing Diagnosis
All participants shared both positive and negative experiences regarding their disclosure of their diagnosis. Regardless of the support they had received from family, friends, partners, or the community, they expressed a preference for isolation. However, they also reported that social isolation resulted in depressed feelings and an increase in irrational thinking. Lucy did not want to disclose her HIV diagnosis because she feared being rejected and accused of giving the virus to her partner. She stated, “I never told the man about my HIV-positive status, and he never saw me taking medication the time we were together. I kept the results of my status secret and to my heart.” Because of the internalized feelings of HIV stigma, many participants decided to conceal their HIV status from family members and friends out of fear of being abandoned, compromising their relationships, or experiencing a violent response. Similarly, Teo did not share her status with her partner: “I have not told him and it’s hard. . . . I want this person to find out by himself. I do not want to put myself out there and end up being accused as one who brought the virus.” Participants feared disclosure because they suspected that their significant other’s response might include anger, violence, and possibly rejection.
Another concern that participants shared with respect to the idea of disclosing the diagnosis within an existing or new relationship was the advice they received from friends after disclosing their HIV status. One participant received misleading feedback from a friend that could have led to her premature death. Lucy stated:
After I was told that I was HIV positive, I did not take the medication. My friend told me that cooking and drinking local herbs like marijuana and other local herbs could kill or weaken the AIDS virus. I decided to follow her advice. I had three children at the time and when I was pregnant with the fourth child, I started to get sick and that is when I got on medication.
This demonstrates a widespread lack of knowledge about the virus, as people misunderstand how HIV is treated, resulting in the spread of misinformation.
Resources Relative to the HIV/AIDS Diagnosis
All eight participants discussed that without focused resources and concerted efforts from the government in addressing mental health services and social and economic needs as barriers, PLWHA will continue to experience negative health outcomes at each step of the HIV care continuum. All participants expressed a lack of knowledge of the government’s support regarding resources needed to manage issues like mental health problems, problems accessing care, and barriers to financial support and transportation.
Knowledge Gap and Awareness
All participants discussed gaps in their knowledge and awareness of the resources available to support them through the crisis. Maria stated:
Here in the villages, we do not have mental health counselors and yet this would have been very helpful for us. We have so many thoughts on our minds and some of these thoughts can lead one to committing suicide. I have heard people with HIV/AIDS in Kampala city have mental health services. I live very far from the town in the village and I would want to know if we have mental health counselors in our village. The only counselors I know of are the ones here at the center who took my blood.
Participants also lacked knowledge about engaging in sexual activities post-diagnosis. For example, following Joseph’s diagnosis, he engaged in sexual relationships with multiple women. Disclosure of the virus reportedly occurred; however, the women did not believe him because he had no visible signs associated with AIDS. Sexual relationships continued despite this disbelief, with the understanding that if the women later discovered that they had the virus, Joseph would take them to the clinic for treatment. This lack of awareness and understanding of available resources contributed to significant challenges in accessing necessary support, highlighting the broader issue of knowledge gaps that hinder effective HIV/AIDS management and prevention.
Government Aid and Involvement
Participants expressed a lack of resources to access treatment and the government’s inability to act on their behalf to navigate their HIV/AIDS issues. They felt that government aid and involvement would support their financial independence and their children’s ability to continue in school. For instance, Immaculate said:
Having government aid would make my life much better and easier. For instance, if the government can give us pigs, this can be very helpful because pigs can be a source of income when we sell them . . . one piglet can cost an equivalent of $26. Having such small businesses can help us become financially independent and be able to support our children to go to school and not drop out.
Similarly, Angella reported that the government had claimed they would support people with HIV/AIDS by supporting small scale farming; those with a plot of land would be given livestock. However, this governmental assistance never came to fruition.
All participants discussed increased psychological distress and symptoms of depression as a result of experiencing HIV-related stigma and a lack of mental health services. Participants reported that because of a lack of government involvement in aiding PLWHA, diagnoses were on the rise, while testing and treatment were in decline. Supporting rural areas to have mental health providers would lead to improvements in the overall well-being of PLWHA in rural Uganda. According to Joseph:
Receiving mental health services can increase my longevity. . . . a mental health counselor coming to my house or in our villages, makes me feel that I am valuable . . . that my country values my life, which in turn encourages me to live happily.
All participants expressed a lack of governmental support for PLWHA in rural Uganda and failure of the government to fulfil the promises it has made in past to PLWHA. For instance, Eva reported:
The government has not supported us. One time we had people from the government coming to our homes and [they] took our pictures, promising that they were going to build houses for us. But the only people who got housing support were the elderly and not people living with HIV/AIDS. Additionally, the government has supported elderly through goat farming but not the people living with HIV/AIDS.
This lack of mental health support, combined with minimal government intervention, not only worsened psychological distress but also contributed to broader systemic barriers, including difficulties in accessing care because of transportation challenges.
Access to Care
All eight participants discussed barriers to care, including transportation and traveling long distances to access HIV treatment, coupled with the high cost of public transportation in rural areas. Eva reported:
I am living with my mother. The distance from the healthcare center to my village is about 12 miles. I find it hard to walk this long distance on days when I do not have money for public transportation. Today, if I was not told that I was not going to be given money for transportation, I would not have come for my treatment. It is a very long distance to walk, especially when you are not feeling well.
Other participants highlighted financial problems as a barrier to accessing treatment. Participants reported difficulty paying healthcare center fees, and six out of eight participants were unemployed. For instance, Lucy said:
It is very expensive to get to the healthcare center, and yet we still are required to pay a fee of about 12.5 dollars, which is approximately 45,800 UG shillings, to get medication every month. Also, I did not have money this term to take my daughter back to school because I have to first pay for the last term. She was allowed to sit for her exams last term but does not get the school report card until I pay the school fees.
Another significant barrier that participants experienced was a lack of support from healthcare providers, including negative attitudes and delays in service. Participants reported that, at times, patients with extra money, often in the form of bribes, were served first, regardless of their arrival time at the healthcare center. Immaculate reported:
One time I got here very early at 6 am before the doors were opened at 7 am. I waited for my medication past 2 pm at the health center. I reported to the doctor that I had not received my medication and yet some people who came after me had received their medication. The doctor responded to me with a negative attitude and anger and asked me what I wanted him to do. He told me that he did not have many hands to look for my file and that I have to wait.
Despite these logistical and financial challenges, participants found solace in the support of some of their friends, highlighting the crucial role of social connections in navigating the difficulties of living with HIV.
Support From Families and Friends Post–HIV Diagnosis
Most of the participants experienced some form of support from their friends. After disclosing their HIV status, participants reported major shifts in family and social relationships, which could be either supportive or not supportive. In Uganda’s rural communities where close relationships are essential for survival, these changes were highly significant. For participants, disclosure marked a turning point, deeply reshaping their lived experiences and social support systems.
Relational Dynamic Changes
All participants stated that their relationships were affected after they shared their HIV status with their family members and friends. Two out of eight participants reported having the support of friends who played an active role in their well-being by interacting with them and providing resources they needed. Eva described friends who kept her accountable for taking her medication when she was unmotivated to do so and just wanted to die: “I have a few friends who have been supportive to me. They have encouraged me that some people live for over 40 years or more if you take your medication and do not stress yourself.” Similarly, Joseph shared positive relationship dynamics after the diagnosis:
Even though my girlfriend had not told me that she had the virus, she is the one who advised me to go for a blood test. After finding out that I was HIV positive, we stayed together because I loved her and we supported each other.
During other interviews, participants shared negative dynamics in spousal relationships. For instance, Immaculate reported:
After I became aware of my HIV-positive diagnosis via blood test, I told my husband that I had been healthy, and I believe he had infected me with the virus. He refuted my allegation and accused me, saying that I was the one with the virus and probably I had infected him. I accepted my situation and decided to separate from my husband.
Although some participants found support from friends who actively contributed to their well-being, the experience of stigma and discrimination created barriers to treatment and acceptance of their diagnosis.
Discrimination
Participants highlighted the issue of discrimination, and whether they had directly or indirectly experienced discrimination, as a barrier when accessing treatment, accepting the diagnosis, or addressing prejudice. For instance, Joseph reported:
I was isolated and discriminated [against] by my family members and close friends, who started to look at me like I was already dead—something that is not of any value waiting to be put in the dust bin. At first, it was hard for me to come and get treatment because people in the villages talk.
Participants also discussed experiencing discrimination from family members and physically being excluded from participating in family events because of their positive HIV status. For instance, Eva reported:
My family discriminated against me by not even wanting to touch me and be close to me. I was locked in a room and was given food by sliding a plate of food in my room. I could not use the same cup and utensils.
Participants also reported that the majority of people in the villages who are HIV positive are not seeking treatment because of fear of stigma and discrimination post-diagnosis. Despite the Ugandan government launching campaigns to encourage community outreach with the help of local leaders, participants in our study reported that many people in villages who have an HIV-positive diagnosis do not seek out early treatment because of the stigma and being discriminated against. For instance, Lucy said:
The majority of people who have HIV/AIDS do not come here to get treatment. Many people fear coming to the clinic because they do not want to be seen and judged. Some decided to go to another clinic, but many do not go for any treatment. They do not want people to know their status because people will go around talking about them and that they are on medication.
In another interview, Joseph reported discrimination related to employment:
One main challenge I have encountered is employment discrimination. This is so because the people who hire me, once they know that I have the virus, they start discriminating [against] me. Many times, I get hired, do the work, but I do not get paid. They keep promising me to be paid every other day, but they never pay me. My boss knows that I have the virus and I need money to get my treatment, but he refuses or delays my payment because he cares more about making his money and not my treatment.
Despite growing awareness of stigma and discrimination as major barriers to eradicating HIV, addressing these issues has not been prioritized in national programs. Participants highlighted discrimination as a significant obstacle to accessing treatment, accepting their diagnosis, and maintaining employment. Many faced exclusions from family and community events, while others avoided seeking treatment altogether because of fear of judgment. Even government-led outreach efforts have struggled to overcome the deep-seated stigma that prevents people from accessing essential care.
Discussion
The aim of this research was to understand the experiences of PLWHA in rural Uganda, rather than to generalize them with others outside of this context; the lived experiences of PLWHA are contingent upon the proximal and distal environment (Breslow & Brewster, 2020). Bearing in mind the transferability of the study findings, we provided robust information about adults living with HIV/AIDS in rural Uganda that can help to examine comparative experiences with those living in urban areas and to create a framework for similar comparisons in other parts of the world. This research study mirrored trends occurring across Uganda. Furthermore, the study participants represented a range of ages, genders, and years living with their diagnosis. Therefore, the findings of this study provide supportive information for similar research on PLWHA globally.
Implications for Clinical Practice
Our findings highlight critical implications for clinical practice by underscoring the need for contextually responsive, holistic mental health care for PLWHA in Uganda. In rural communities where relationships are vital for survival, relational changes caused by an HIV/AIDS diagnosis can profoundly affect psychological well-being, making it essential for clinicians to integrate psychosocial support with medical treatment. Addressing stigma, strengthening community ties, and tailoring interventions to differences in age, sex, and duration of illness can enhance the effectiveness of care and promote resilience. For U.S.-based practitioners, these insights underscore the importance of cultural humility and the recognition that environmental and relational contexts significantly influence the lived experiences of PLWHA. Applying these lessons can inform more individualized and culturally competent care for African diaspora populations and other marginalized groups, advancing patient-centered and equitable models of practice.
Implications for Social Change
The Bethany Land Institute (BLI), a nonprofit organization, provides a useful, real-world model for addressing not only the physical but also the psychosocial dimensions of HIV/AIDS in rural Uganda (BLI, 2025). Its approach aligns closely with key themes such as spirituality, knowledge gaps and awareness, discrimination, and fear and anxiety by embedding mental health support within community development and ecological programs. For instance, BLI integrates spirituality as a core component of healing and resilience, which is especially important in rural Ugandan contexts in which faith-based worldviews are central to daily life. Founded on Christian principles, BLI incorporates spiritual reflection, prayer, and values such as stewardship, hope, and dignity into its training programs. For PLWHA, spirituality helps reframe illness as part of a broader life journey rather than a moral failure, reducing internalized stigma while fostering a sense of belonging through shared community values. Also, BLI addresses knowledge gaps and limited awareness, which are major barriers in rural Uganda. By embedding health education into its livelihood and sustainability programs, participants engage in agricultural and ecological training to receive information about nutrition. This practical learning model uses hands-on demonstrations, such as nutrition-sensitive farming, to show how proper diet supports immune health for PLWHA. Once participants are trained, they are empowered with actionable knowledge to return to their villages and improve community health outcomes.
Professional counselors increasingly recognize the impact of social factors on individual well-being. Integrating mental and physical healthcare improves outcomes for PLWHA. In rural Africa, particularly Uganda, limited access to quality medical and counseling services is compounded by unemployment, poverty, and low socioeconomic status. Addressing these challenges requires meaningful conversations within the counseling profession in order to develop effective responses to HIV/AIDS in resource-limited settings.
This research confirms that health and social factors significantly impact PLWHA. Although professional counselors may not fully understand the lived experiences of individuals with HIV/AIDS in rural Uganda, fostering connections among service providers can improve treatment outcomes. Strengthening these networks helps identify available resources, address service gaps, and guide further research. The counseling profession has opportunities to engage with rural African communities through partnerships with organizations such as BLI. BLI supports individuals in rural Uganda affected by HIV/AIDS and other illnesses, many of whom have lost family members to this pandemic. By providing sustainable agriculture programs, BLI helps participants build stable livelihoods. Collaborating with such initiatives allows U.S.–based counselors and counseling programs to contribute to global mental health efforts, support sustainable development, and enhance culturally responsive care. This is one example of unique opportunities for the counseling profession in the United States to get more involved by connecting and partnering with these types of programs in Uganda and Africa.
Limitations
This study met the established criteria for qualitative research, and data saturation was achieved. In line with methodological guidance, we aimed for a sample of six to 10 participants and conducted 90-minute in-depth interviews, which supported saturation and enhanced trustworthiness (Shelton & Bridges, 2022). A potential limitation, however, was the influence of prior assumptions about the phenomenon. Despite the use of bracketing to set aside personal biases, achieving complete neutrality is challenging (Jackson et al., 2018). To further strengthen trustworthiness, we approached data collection with intentionality, focusing on describing participants’ lived experiences without judgment. Husserl introduced the concept of intentionality, a cornerstone of phenomenological research, to capture “life-world experiences or lived experiences” (Giorgi, 2012b, p. 132; Giorgi et al., 2017).
Recommendation for Further Research
Our study highlights several priorities for future research. Findings reveal unique considerations related to support, barriers, and existential crises affecting the quality of life of PLWHA in rural Uganda. Participants emphasized the lack of government support despite Uganda’s historical leadership in the HIV/AIDS response since the 1980s. This raises important questions about potential governmental disconnection or complacency, warranting further research on the evolving role of government support and public perceptions. Additionally, the study highlights the importance of relational support in rural Uganda, where family, social, and community connections are crucial for maintaining well-being and survival. Wissing et al. (2020) noted that relationships in the African context are rooted in interconnectedness, interdependence, solidarity, and belonging. A quantitative study could expand these findings to a broader sample, increasing generalizability.
Conclusion
The purpose of this qualitative transcendental phenomenological study was to describe the lived experiences of people living with HIV/AIDS in rural Uganda. Addressing the challenges facing PLWHA in rural Uganda requires urgent intervention from the Ugandan government, counselors, and educators. Although the United States has long engaged with Africa in healthcare, recent policy changes may threaten this collaboration (Schreiber, 2025). Strengthening global mental health initiatives is crucial, necessitating cultural competence in order to effectively support affected communities (American Counseling Association, 2014). This qualitative study provides essential insights into the complexities of HIV/AIDS and mental health counseling in rural Uganda, emphasizing the need for culturally informed global interventions.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
Akatukwasa, C., Getahun, M., El Ayadi, A. M., Namanya, J., Maeri, I., Itiakorit, H., Owino, L., Sanyu, N., Kabami, J., Ssemmondo, E., Sang, N., Kwarisiima, D., Petersen, M. L., Charlebois, E. D., Chamie, G., Clark, T. D., Cohen, C. R., Kamya, M. R., Bukusi, E. A., . . . Camlin, C. S. (2021). Dimensions of HIV-related stigma in rural communities in Kenya and Uganda at the start of a large HIV “test and treat” trial. PLoS ONE, 16(5), 1–17. https://doi.org/10.1371/journal.pone.0249462
American Counseling Association. (2014). ACA code of ethics. https://bit.ly/ACACodeofEthics
Bethany Land Institute. (2025, May 7). Who are we? https://www.bethanylandinstitute.org
Breslow, A. S., & Brewster, M. E. (2020). HIV is not a crime: Exploring dual roles of criminalization and discrimination in HIV/AIDS minority stress. Stigma and Health, 5(1), 83–93. https://doi.org/10.1037/sah0000177
Byrd, K. K., Hardnett, F., Hou, J. G., Clay, P. G., Suzuki, S., Camp, N. M., Shankle, M. D., Weidle, P. J., & Taitel, M. S. (2020). Improvements in retention in care and HIV viral suppression among persons with HIV and comorbid mental health conditions: Patient-centered HIV care model. AIDS and Behavior, 24(12), 3522–3532. https://doi.org/10.1007/s10461-020-02913-2
Centers for Disease Control and Prevention. (2021). About HIV. https://www.cdc.gov/hiv/about/?CDC_AAref_Val=https://www.cdc.gov/hiv/basics/whatishiv.html
Chan, Z. C. Y., Fung, Y., & Chien, W. (2013). Bracketing in phenomenology: Only undertaken in the data collection and analysis process. The Qualitative Report, 18(30), 1–9. https://doi.org/10.46743/2160-3715/2013.1486
Cope, D. G. (2014). Methods and meanings: Credibility and trustworthiness of qualitative research. Oncology Nursing Forum, 41(1), 89–91. https://doi.org/10.1188/14.ONF.89-91
Costelloe, S., Kemppainen, J., Brion, J., MacKain, S., Reid, P., Frampton, A., & Rigsbee, E. (2015). Impact of anxiety and depressive symptoms on perceptions of stigma in persons living with HIV disease in rural versus urban North Carolina. AIDS Care, 27(12), 1425–1428. https://doi.org/10.1080/09540121.2015.1114993
Creswell, J. W., & Creswell, J. D. (2018). Research design: Qualitative, quantitative, and mixed methods (5th ed.). SAGE.
De Jesus, M., & Williams, D. R. (2018). The care and prevention in the United States Demonstration Project: A call for more focus on the social determinants of HIV/AIDS. Public Health Reports, 133, S28–S33. https://doi.org/10.1177/0033354918801353
Fusch, P. I., & Ness, L. R. (2015). Are we there yet? Data saturation in qualitative research. The Qualitative Report, 20(9), 1408–1416. https://nsuworks.nova.edu/tqr/vol20/iss9/3
Giorgi, A. (1997). The theory, practice, and evaluation of the phenomenological method as a qualitative research procedure. Journal of Phenomenological Psychology, 28(2), 235–260. https://doi.org/10.1163/156916297×00103
Giorgi, A. (2009). The descriptive phenomenological research method in psychology: A modified Husserlian approach. Duquesne University Press.
Giorgi, A. (2012a). The descriptive phenomenological psychological method. Journal of Phenomenological Psychology, 43(1), 3–12. https://doi.org/10.1163/156916212X632934
Giorgi, A. (2012b). Review of “Subjectivity and lifeworld in transcendental phenomenology.” Journal of Phenomenological Psychology, 43(1), 131–135. https://doi.org/10.1163/156916212X632970
Giorgi, A., Giorgi, B., & Morley, J. (2017). The descriptive phenomenological psychological method. In C. Willig & W. S. Rogers (Eds.), The SAGE handbook of qualitative research in psychology (pp. 176–192). SAGE. https://doi.org/10.4135/9781526405555.n11
Hladik, W., Sande, E., Berry, M., Ganafa, S., Kiyingi, H., Kusiima, J., & Hakim, A. (2017). Men who have sex with men in Kampala, Uganda: Results from a bio-behavioral respondent driven sampling survey. AIDS and Behavior, 21(5), 1478–1490. https://doi.org/10.1007/s10461-016-1535-2
Husserl, E. (1931). Ideas: General introduction to pure phenomenology. [Trans. by W. R. B. Gibson]. Routledge.
Ijeoma, A., Ejikeme, A., Theodora, O., & Chika, O. (2018). Knowledge, attitude, willingness of HIV counseling and testing and factors associated with it, among long distant drivers in Enugu, Nigeria: An opportunity in reduction of HIV prevalence. African Health Sciences, 18(4), 1088–1097. https://doi.org/10.4314/ahs.v18i4.30
Jackson, C., Vaughan, D., R., & Brown, L. (2018). Discovering lived experiences through descriptive phenomenology. International Journal of Contemporary Hospitality Management, 30(11), 3309–3325. https://doi.org/10.1108/IJCHM-10-2017-0707
Kalichman, S., Katner, H., Banas, E., & Kalichman, M. (2017). Population density and AIDS-related stigma in large-urban, small-urban, and rural communities of the southeastern USA. Prevention Science, 18, 517–525.
https://doi.org/10.1007/s11121-017-0761-9
Kiene, S. M., Sileo, K., Wanyenze, R. K., Lule, H., Bateganya, M. H., Jasperse, J., Nantaba, H., & Jayaratne, K. (2015). Barriers to and acceptability of provider-initiated HIV testing and counselling and adopting HIV-prevention behaviors in rural Uganda: A qualitative study. Journal of Health Psychology, 20(2), 173–187. https://doi.org/10.1177/1359105313500685
Kitara, D. L., & Aloyo, J. (2012). HIV/AIDS stigmatization, the reason for poor access to HIV counseling and testing (HCT) among the youths in Gulu (Uganda). African Journal of Infectious Diseases, 6(1), 12–20. https://doi.org/10.4314/ajid.v6i1.77737
Korstjens, I., & Moser, A. (2018). Series: Practical guidance to qualitative research. Part 4: Trustworthiness and publishing. European Journal of General Practice, 24(1), 120–124. https://doi.org/10.1080/13814788.2017.1375092
Koskinen, C. (2025). Researcher vulnerability in qualitative research—A conceptual framework. Scandinavian Journal of Caring Sciences, 39(1), e70012. https://doi.org/10.1111/scs.70012
Kumar, N., Unnikrishnan, B., Thapar, R., Mithra, P., Kulkarni, V., Holla, R., Bhagawan, D., & Kumar, A. (2017). Stigmatization and discrimination toward people living with HIV/AIDS in a coastal city of south India. Journal of the International Association of Providers of AIDS Care, 16(3), 226–232. https://doi.org/10.1177/2325957415569309
Lim, W. M. (2026). Sample size in qualitative research: Moving from data saturation to theoretical saturation. Journal of Global Marketing, 39(2), 224–234. https://doi.org/10.1080/08911762.2025.2590757
Mi Choi, K., & Hyun, J. H. (2023). Perceptions and experiences of school counselor trainees on self-care grounded in mindfulness and social–emotional learning. The Professional Counselor, 13(2), 113–128. https://doi.org/10.15241/kmc.13.2.113
Moustakas, C. (1994). Phenomenological research methods. SAGE.
Nakimuli-Mpungu, E., Musisi, S., Smith, C. M., Von Isenburg, M., Akimana, B., Shakarishvili, A., Nachega, J. B., Mills, E. J., Chibanda, D., Ribeiro, M., Williams, A. V., & Joska, J. A. (2021). Mental health interventions for persons living with HIV in low- and middle-income countries: A systematic review. Journal of the International AIDS Society, 24(S2), 100–114. https://doi.org/10.1002/jia2.25722
Nasi, M., De Biasi, S., Gibellini, L., Bianchini, E., Pecorini, S., Bacca, V., Guaraldi, G., Mussini, C., Pinti, M., & Cossarizza, A. (2017). Ageing and inflammation in patients with HIV infection. Clinical and Experimental Immunology, 187(1), 44–52. https://doi.org/10.1111/cei.12814
National Institutes of Health. (2024, November 13). Living with HIV. HIVinfo. https://hivinfo.nih.gov/understanding-hiv/fact-sheets/hiv-and-mental-health
Obeagu, E. I., & Obeagu, G. U. (2024). Preventive measures against HIV among Uganda’s youth: Strategies, implementation, and effectiveness. Medicine, 103(44), e40317. https://doi.org/10.1097/MD.0000000000040317
Peoples, K. (2021). How to write a phenomenological dissertation: A step-by-step guide. SAGE.
Poorolajal, J., Hooshmand, E., Mahjub, H., Esmailnasab, N., & Jenabi, E. (2016). Survival rate of AIDS disease and mortality in HIV-infected patients: A meta-analysis. Public Health, 139, 3–12. https://doi.org/10.1016/j.puhe.2016.05.004
Remien, R. H., Stirratt, M. J., Nguyen, N., Robbins, R. N., Pala, A. N., & Mellins, C. A. (2019). Mental health and HIV/AIDS: The need for an integrated response. AIDS, 33(9), 1411–1420. https://doi.org/10.1097/QAD.0000000000002227
Schreiber, M. (2025, January 25). Trump’s “stop-work” order for PEPFAR cuts off anti-HIV drugs for patients. National Public Radio. https://www.npr.org/sections/goats-and-soda/2025/01/28/g-s1-45030/pepfar-trump-drugs-stop-work
Setlhare, V., Wright, A., & Couper, I. (2014). The experiences of people living with HIV/AIDS in Gaborone, Botswana: Stigma, its consequences and coping mechanisms. South African Family Practice, 56(6), 309–313. https://doi.org/10.1080/20786190.2014.975484
Shelton, D., & Bridges, C. W. (2022). A phenomenological exploration of adoptive parent experiences of support during the adoption process. Adoption Quarterly, 25(3), 212–243. https://doi.org/10.1080/10926755.2021.1976336
Sulung, N., & Asyura, R. (2019). The analysis of spirituality of patients with HIV/AIDS in taking lessons and self-acceptance. Indian Journal of Palliative Care, 25(2), 232–235. https://doi.org/10.4103/IJPC.IJPC_203_18
Uganda AIDS Commission. (2020). The monitoring and evaluation plan for the national HIV and AIDS strategic plan 2020/21-2024/25. https://www.prepwatch.org/wp-content/uploads/2022/07/Uganda-ME-Plan-2020-25.pdf
Uganda AIDS Commission. (2022). 2022 fact sheet: Facts on HIV and AIDS in Uganda 2022. https://uac.go.ug/images/2024/facttsheets/hiv-aids-factsheet-2022.pdf
Uganda Ministry of Health. (2022). Health alerts and services. https://uac.go.ug/images/2024/jar-2024/jar-report-_-final_2021_nov-12.pdf
UNAIDS. (2020). Fact sheet – World AIDS Day 2020. https://uac.go.ug/media/attachments/2021/09/13/unaids_factsheet_en.pdf
UNAIDS. (2021). UNAIDS data 2021. https://www.unaids.org/sites/default/files/media_asset/JC3032_AIDS_Data_book_2021_En.pdf
Wissing, M. P., Wilson Fadiji, A., Schutte, L., Chigeza, S., Schutte, W. D., & Temane, Q. M. (2020). Motivations for relationships as sources of meaning: Ghanaian and South African experiences. Frontiers in Psychology, 11. https://doi.org/10.3389/fpsyg.2020.02019
Godfrey Ddungu, PhD, NCC, ACS, LCPC, ASDCS, is an assistant professor at California State University Fresno. Corinne W. Bridges, EdD, NCC, BC-TMH, LPCC, is an associate professor at Walden University. Cynthia A. Briggs, PhD, NCC, LCMHC(NC), is an associate professor at Walden University. Correspondence may be addressed to Godfrey Ddungu, Department of Counselor Education and Rehabilitation, Kremen School of Education and Human Development, California State University Fresno, 5005 N Maple Ave MS ED1, 455, Fresno, CA 93740, goddungu@mail.fresnostate.edu.
Apr 1, 2026 | Volume 16 - Issue 1
Danielle Pester Boyd, Laura K. Jones, Courtney Maier, Danica G. Hays
The intentional exploration or broaching of topics related to the social determinants of mental health (SDoMH) throughout the counseling process helps align clinical practice with the profession’s focus on multicultural and social justice counseling competency. This article identifies six SDoMH broaching behaviors for counselors: (a) counselor development, (b) client psychoeducation, (c) contextualization, (d) attending to differences, (e) addressing emergent needs, and (f) termination practices. These SDoMH broaching behaviors span counselor preparation, assessment, intervention, and termination, empowering counselors to address SDoMH in their work. We conclude with implications for fostering SDoMH broaching behaviors within counselor education.
Keywords: broaching, social determinants of mental health, multicultural, counseling competency, counselor education
Counselors are increasingly called upon to integrate multicultural competence and social justice advocacy into their practice, particularly when addressing systemic and environmental factors that shape client well-being. The Multicultural and Social Justice Counseling Competencies (MSJCC; Ratts et al., 2016) and relevant constructs, such as the social determinants–based counseling model (SDCM; Pester Boyd et al., 2025) and the multidimensional model of broaching behavior (MMBB; Day-Vines et al., 2020), provide guiding frameworks for ensuring culturally responsive care. Taken together, these models inform concrete methods for integrating discussions of systemic, environmental, and structural influences into counselor–client interactions, which create a foundation for a set of broaching behaviors focused specifically on the social determinants of mental health (SDoMH).
Social determinants of health (SDOH) refer to “the conditions in which people are born, grow, live, work, and age that shape health outcomes” (World Health Organization [WHO], 2025, para. 1). These determinants include economic stability (e.g., employment, income), health care access, education, neighborhood safety, and social relationships, all of which impact physical and mental health. The SDoMH focus specifically on the social and structural factors influencing mental health outcomes, such as exposure to discrimination, adverse childhood experiences, community violence, economic disparities, and barriers to mental health care (Compton & Shim, 2020), influences that are reflected in the MSJCC.
The SDCM is an empirically based systemic framework for addressing SDoMH across various practice settings (Pester Boyd et al., 2025). It guides counselors in identifying barriers, such as economic hardship, discrimination, and limited access to resources, and then provides a structured process for broaching these concerns in session. Beyond simple recognition, the SDCM emphasizes implementing culturally responsive interventions, including connecting clients with community supports, advocating for policy changes, or adapting treatment plans to account for systemic stressors. This systemic responsiveness communicates to clients that their external challenges are legitimate and central to their mental health care, which reinforces the therapeutic alliance by integrating advocacy with clinical practice. Given the links among the MSJCC, SDoMH, and therapeutic outcomes, it is imperative that counselors are familiar with SDoMH, understand their impact, and are prepared to broach topics related to SDoMH with clients. Therefore, integrating the SDCM with known broaching models like the MMBB can serve to operationalize these action strategies as concrete methods to demonstrate the MSJCC.
The MMBB provides a framework to explicitly explore or broach racial, ethnic, and cultural (REC) factors with clients throughout the therapeutic process (Day-Vines et al., 2020, 2021). These broaching behaviors focus on four distinct contexts: intracounseling, intraindividual, intra-REC, and inter-REC domains. Specifically, counselors acknowledge REC concerns that impact the counselor–client relationship (intracounseling), the intersections of the client’s identity (intraindividual), the client’s cultural group membership (intra-REC), and their experiences with structural inequality (inter-REC). By intentionally attending to these layers, counselors demonstrate cultural humility and multicultural competency that affirms the realities of clients’ REC concerns. Effective broaching has been linked to enhanced client trust, increased depth of client self-disclosure, higher levels of client satisfaction, and improved therapeutic outcomes, which make it a critical component of effective multicultural counseling (Depauw et al., 2025; Gantt-Howrey et al., 2024; King & Borders, 2019; Zhang & Burkard, 2008).
By integrating the SDCM with the MMBB, we developed a set of SDoMH-specific broaching behaviors. The MMBB strengthens the relational dimension of counseling through cultural engagement while the SDCM equips counselors to act on systemic barriers that influence client well-being. Together, these models ultimately foster trust, collaboration, and empowerment and establish counseling as a space where both individual experiences and broader structural inequities are acknowledged and addressed.
SDoMH Broaching Behaviors
This article describes six SDoMH broaching behaviors for counselors grounded in the MMBB and the SDCM: counselor development, client psychoeducation, contextualization, attending to differences of lived experience, addressing emergent needs, and SDoMH-informed termination practices. These SDoMH broaching behaviors represent an interactive approach in which counselors shift among the behaviors throughout their own development as well as during assessment, intervention, and termination within the counseling relationship.
Counselor Development
The first SDoMH broaching behavior is initiated during a counselor’s preparation to work with clients. In alignment with the MSJCC (Ratts et al., 2016), counselors are expected to continually foster both knowledge and self-awareness related to the multicultural and social justice issues facing their clients, including client experiences with SDoMH. In order to develop their knowledge of SDoMH scholarship, counselors can familiarize themselves with the seminal SDOH/SDoMH frameworks (e.g., Compton & Shim, 2020; Lund et al., 2018; WHO, 2025); guiding practice models related to broaching behaviors and best practices for addressing the SDoMH (e.g., MMBB, SDCM; Day-Vines et al., 2020; Pester Boyd et al., 2025); general scholarship on SDoMH application in training, practice, and research (e.g., Johnson et al., 2023; Lenz & Lemberger-Truelove, 2023; Lenz & Litam, 2023; Mason et al., 2023; Neal Keith et al., 2023; Pester et al., 2023); and, when applicable, setting-specific SDoMH resources for school counselors (e.g., Brookover, 2024; Johnson & Brookover, 2021), career counselors (Johnson et al., 2024), and family counselors (Robins et al., 2022).
Next, to facilitate self-awareness, counselors are encouraged to engage in reflective practices that identify areas of strength in addressing SDoMH with clients and areas that require skill and dispositional development. First, counselors should reflect on any personal experiences with SDoMH and how those experiences may both inform and potentially bias their work with clients. For example, counselors who have dealt with their own experiences of economic instability may need to watch for emerging countertransference with clients having similar experiences. We recommend that counselors review existing SDoMH frameworks and identify which determinants have affected them personally and interpersonally with peers, family members, and colleagues. In addition, they can consider what strategies were helpful or harmful as they personally navigated SDoMH.
Counselors should also reflect on any prior experiences working with clients who were dealing with SDoMH and how those prior professional experiences might inform and potentially bias their ability to help new clients with SDoMH. For example, counselors might view clients as resistant if they do not consistently attend counseling sessions, although those clients may be dealing with circumstances impacted by SDoMH (e.g., unstable transportation, lack of childcare, unreliable internet access). Mechanisms such as supervision or consultation can be helpful for facilitating counselor awareness and development related to being nonjudgmental, showing unconditional positive regard, and embodying congruence, which are all vital components of creating and maintaining a strong therapeutic alliance.
Additionally, counselors or counseling supervisors can administer the Addressing Client Needs with Social Determinants of Health Scale (ACN:SDH, Johnson, 2023) to more formally assess readiness for addressing SDoMH. This tool measures a provider’s SDOH competency related to knowledge, awareness, biases, skills, and preparedness. The ACN:SDH findings can be reviewed within supervision or consultation. For areas where data reflect a lack of readiness, counselors can process feelings associated with their limited readiness and brainstorm resources that may be useful for building readiness. Ultimately, as counselors focus inward to broach and support their professional development related to the SDoMH framework, they will be more prepared to implement the remaining SDoMH broaching behaviors in client interactions.
Client Psychoeducation
Client psychoeducation is the next SDoMH broaching behavior that begins during the intake and assessment process. Psychoeducation is an evidence-based intervention that integrates client education into the counseling process by connecting clinical outcomes to increased client self-awareness and skill development across many mental health presenting concerns (e.g., anxiety, depression, schizophrenia; Dolan et al., 2021; Luo et al., 2025). We suggest that counselors mindfully introduce SDoMH psychoeducation into the intake and assessment process to increase client knowledge and awareness about the potential impact of SDoMH on well-being.
Furthermore, there is growing support for universal SDoMH screening (Gantt-Howrey et al., 2024; Johnson & Brookover, 2021; Johnson et al., 2023), with many available screeners for counselors to use, including the Protocol for Responding to and Assessing Patients’ Assets, Risks, and Experiences (PRAPARE; 2022); the Accountable Health Communities Health-Related Social Needs Screening Tool (Center for Medicare and Medicaid Innovation, n.d.); and the WE CARE Survey (Garg et al., 2007). These screeners can be incorporated into intake processes to establish a baseline of SDoMH data for clients. For example, the PRAPARE assessment identifies both individual areas of risk related to social determinants and an overall risk tally score. Counselors can use this data to inform both the focus of the psychoeducation intervention and the client’s treatment plan.
Many clients may not fully understand why they are being asked about these areas of their lives or be aware of how these determinants may influence well-being. Therefore, counselors should first define SDoMH and explain the overall framework using jargon-free language. For example:
Social determinants of mental health are different social and environmental factors that can positively or negatively influence our physical and mental health. These can be factors like having your basic needs of food, housing, and employment met; having access to quality education and health care; living in a safe environment free of violence and risk; and having strong social and community support. The more people are surrounded by supportive social and environmental conditions, the easier it is to improve overall health and mental health. When people do not have adequate access to these conditions, it can lead to a higher risk of health and mental health concerns. It is important for the work that we are going to do together to have a clear picture of how your environment is influencing your physical and mental health so that we can work to increase conditions that will support the positive mental health changes you are wanting to make.
Counselors can also consider using visual tools in session, such as handouts that depict SDoMH in an easily understandable format (see Figure 1 for a sample).
Counselors should then use the SDoMH data collected through the assessment process to provide data-driven psychoeducation about the specific social determinant risk areas identified in a client’s assessment, outlining the research and known physical and mental health risks and outcomes of those determinants. For example, one item on the PRAPARE assessment asks, “How often do you see or talk to people that you care about and feel close to?” If a client answers less than three times per week, they are flagged for a risk tally on this item; the counselor could provide psychoeducation on the impact of social connection and community support alongside the risks of social isolation (U.S. Department of Health and Human Services, 2023). A counselor might broach the topic by saying:
I noticed when you were asked how many times you see or talk to people you care about that you answered less than three times per week. I ask this question on the screener because at times the number and quality of our social connections can have an influence on our physical and mental health. For example, social isolation has been linked to increased risk of anxiety and depression, lower academic and job performance, greater susceptibility to viruses and respiratory illnesses, and even long-term risk of diseases such as heart disease and stroke. Healthy social connection can protect us from disease and increase our sense of safety, meaning, and resilience. Tell me more about what social connection looks like in your life.
By broaching the subject in this way, the counselor can intentionally assess the impact of a specific social determinant on the client’s overall well-being and health. In the example, the counselor would seek to understand the quantity, quality, and impact of the client’s relationships while also screening for any potential physical symptoms that might require an external referral. This practice of broaching SDoMH through client psychoeducation and assessment allows the counselor to implement data-driven practices that provide a multitiered therapeutic framework to conceptualize client concerns across various socioecological levels (e.g., individual, interpersonal, community, public policy). This in turn supports the development of a more holistic treatment plan that incorporates both individual and community interventions.
Figure 1
Visual Depiction of the Social Determinants of Mental Health for Clinical Use
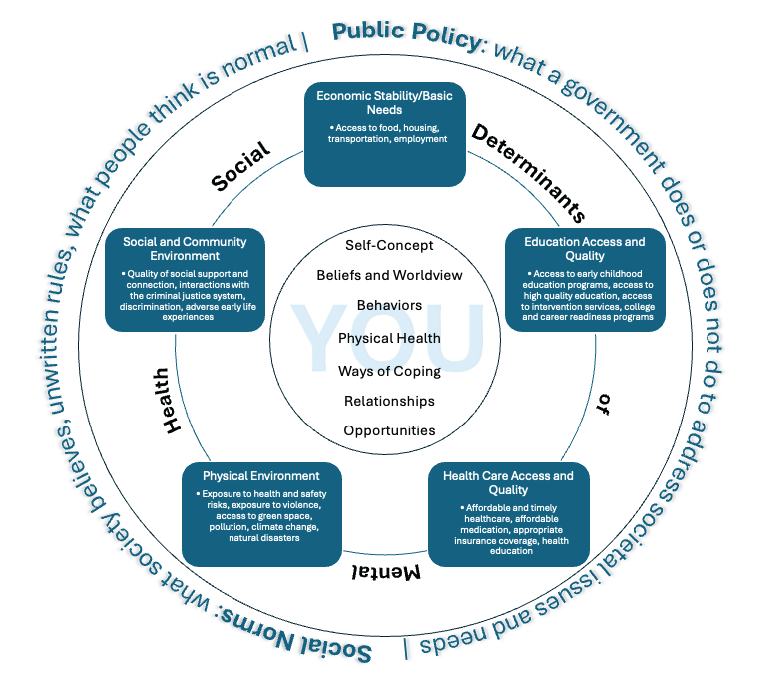
Note. Adapted from Social Determinants of Health, by Office of Disease Prevention and Health Promotion, 2025 (https://odphp.health.gov/healthypeople/objectives-and-data/social-determinants-health) and “Social Determinants of Mental Health” by Compton, M. T., & Shim, R. S., 2015, Focus, 13(4), p. 420 (https://doi.org/10.1176/appi.focus.20150017).
Contextualizing SDoMH for Each Client
As a client develops understanding and awareness of the social determinants impacting their well-being, the counselor should also use broaching to contextualize that knowledge on an individual level. In this way, counselors go beyond educating clients about SDoMH in general and instead seek to collaborate with the client to understand how they are uniquely impacted by those factors. This practice of contextualizing SDoMH allows the client to make connections between their lived experiences, intrapsychic concerns, and the larger social and environmental context.
This broaching behavior aligns well with the MMBB and its intraindividual, intra-REC, and inter-REC broaching dimensions. Counselors can apply these broaching dimensions to the contextualization process. For example, intraindividual broaching can be used to acknowledge how SDoMH impact a client’s identity dimensions (e.g., race, gender, socioeconomic status, sexual orientation, immigration status). A counselor could say, “It sounds like financial strain has limited your transportation options to get to your appointments. Let’s find some free or low-cost alternatives that might better fit within your budget.” Intra-REC broaching, or the exploration of within–cultural group concerns, can help the counselor discuss any client issues impacted by SDoMH that are culture-specific. A counselor might say to the client, “I imagine it could be difficult to ask family and friends for a ride to your appointments if mental health is stigmatized in those relationships.” Finally, a counselor may apply inter-REC broaching by exploring a client’s experiences with discrimination:
Relying on public transportation resources in this city has caused you to miss important appointments and events. It sounds like these public resources don’t meet the needs of residents. I plan to write a letter to the city council explaining some of the issues. Is there anything specific that you would like me to communicate or any way that you would like to advocate for changes?
By integrating these specific broaching dimensions, counselors can help clients gain both self and situational awareness by better understanding the possible role of social determinants in their own lives. In turn, this allows the counselor and client to better address challenges by understanding the client’s unique needs in context. From the previous example, the counselor might consider the following: Does the client need help identifying additional transportation resources? Would virtual counseling sessions be a more accessible option? Can I advocate for improved public transportation in the local community by providing key context to local leaders about how unreliable transportation affects the health of their constituents? Are there self-advocacy skills that I could help the client develop? Through targeted discussions on SDoMH like these, counselors can ensure that they are providing culturally responsive care that meets their clients’ unique needs.
Broaching Differences in the Counselor–Client Relationship
As SDoMH factors are integrated into the therapeutic process, counselors must also attend to the interpersonal process of the therapeutic alliance by intentionally broaching any differences that may exist between the counselor and client. Clients from historically marginalized backgrounds may experience factors that may differ significantly from their counselor’s lived experiences, such as heightened economic instability, community violence, and health care barriers (Compton & Shim, 2015). The MMBB, through its intracounseling domain, emphasizes that a counselor must actively acknowledge and explore REC differences between the counselor and client to attend to any disruptive interpersonal processes that might impact the therapeutic relationship (Day-Vines et al., 2020). We suggest that differences in lived experience related to SDoMH be treated comparably to ensure culturally responsive and effective care.
Research suggests that counselors who fail to broach REC concerns and SDoMH-related disparities risk reinforcing dominant cultural narratives that dismiss or minimize the structural challenges clients face, potentially leading to client disengagement, cultural miscommunication, and premature termination of counseling services (Day-Vines et al., 2021; Drinane et al., 2018; Owen et al., 2014). Thus, it is incumbent upon counselors to broach these differences with cultural humility, openness, and a willingness to engage in difficult but necessary conversations (Newton & Steele, 2025). To effectively broach these conversations, a counselor should adopt a collaborative, client-centered approach by acknowledging potential differences in lived experiences while affirming the client’s perspective.
One strategy is for the counselor to invite open discussions by saying:
I recognize that my experiences may be different from yours, and I don’t want to make assumptions about the challenges that you face. I’d like to understand more about how factors like financial stress, health care access, or discrimination may be affecting your mental health. Would you be open to sharing what that has been like for you?
This type of broaching explicitly acknowledges differences in identity, privilege, and lived experience between the counselor and client while creating a nonjudgmental and validating therapeutic space for the client to share their reality (Day-Vines et al., 2021).
Another example of effective intracounseling broaching can be seen in a case where a White counselor works with a Black client who describes frequent racial discrimination in the workplace. To avoid deflecting or minimizing the client’s experience, the counselor might say, “I want to acknowledge that my lived experience may not reflect what you’re describing, but I want to understand how these challenges impact your well-being.” This affirming, non-defensive approach allows for deeper exploration of SDoMH factors such as racial stress, economic opportunity, and access to mental health care (Newton & Steele, 2025). Such intentional broaching behaviors can also help mitigate client mistrust, validate sociocultural realities, and strengthen the therapeutic alliance (Day-Vines et al., 2021).
Building rapport and trust is central to the broaching process, particularly when addressing systemic disparities. Trust building requires empathy, active listening, and a willingness to acknowledge one’s own biases (Day-Vines et al., 2021). Integrating clients’ interests, cultural values, and lived experiences into sessions makes counseling more relevant, while creating a safe space grounded in unconditional acceptance encourages openness and authenticity. Together, these broaching practices foster trust, empower clients to take an active role in the process, and strengthen the foundation for growth and change.
Broaching Emergent Needs in Session
Counselors should also be mindful to broach emergent client needs throughout the therapeutic process. Though counselors may assess clients for SDoMH at the beginning of the counseling process, that information must be viewed within a dynamic client context that requires an ongoing response rather than a one-time assessment. Therefore, counselors must remain attuned to emerging SDoMH needs throughout the therapeutic process and utilize immediacy skills to broach and address concerns as they arise.
Many clients face barriers related to income, health care access, transportation, and social support networks, all of which can create stressors that directly influence mental health outcomes because they add layers of stress that can overshadow therapeutic work (Compton & Shim, 2015). When basic needs are not met, clients may experience heightened anxiety, hopelessness, or distraction, which can limit their ability to fully engage in treatment.
Ongoing systemic barriers can also reinforce feelings of disempowerment and make it harder for clients to trust the counseling process or believe change is possible. As a result, unresolved SDoMH challenges often lead to inconsistent attendance, premature termination, or reduced treatment effectiveness. By addressing these barriers within the counseling process, counselors not only improve client retention and engagement but also enhance overall wellness by affirming that external stressors are legitimate and integral to mental health care.
For example, a client who discloses heightened anxiety over an overdue utility bill may struggle to engage in therapy until the pressing financial stressor is addressed. A counselor might broach this concern by saying, “I can see how this situation is overwhelming and I want to support you in finding a solution. Would it be helpful to take a few minutes to explore assistance programs or a payment plan?” This response validates the client’s distress while offering immediate, actionable support to address a pressing external challenge. Similarly, a client struggling with transportation barriers may benefit from a session in which the counselor helps them identify local transit options, employer benefits, or community-based ride services to ensure consistent access to mental health care. Meeting such immediate, concrete needs within the session fosters greater trust, retention, and engagement in the counseling process (Day-Vines et al., 2021; Newton & Steele, 2025). Additionally, addressing pressing SDoMH concerns in real time reinforces the message that both psychological distress and external stressors are valid therapeutic concerns. This approach ensures that counseling remains responsive and supportive of the client’s holistic well-being.
Beyond directly helping clients address pressing needs in session, the counselor can support self-advocacy and empowerment by equipping clients with the knowledge and skills to independently resolve their emergent needs. Developing self-advocacy skills enables clients to engage more effectively with health care providers, employers, and social service agencies providing skills that bridge the counseling office into everyday life (Compton & Shim, 2020). Self-advocacy intervention empowers clients to actively pursue resources, assert their rights, and confront systemic barriers with confidence. Moreover, self-advocacy skills foster resilience and equip clients to not only overcome immediate obstacles but to also sustain progress in the face of future challenges. In this way, developing self-advocacy skills is not just a counseling technique but a vital outcome that supports long-term growth and empowerment.
The counselor can facilitate the development of self-advocacy skills by helping clients identify resources, role-play difficult conversations, and anticipate potential barriers they may encounter when seeking support. For example, a client experiencing housing insecurity may feel intimidated about reaching out to a local housing agency because of past negative experiences or uncertainty about eligibility requirements. A counselor might role-play the conversation by saying, “Let’s practice how you might explain your situation when calling the housing agency. You could start by saying, ‘I’m looking for assistance with securing stable housing. Can you help me understand the eligibility requirements and next steps?’” This approach allows the client to rehearse the interaction in a supportive setting, boosting their confidence before making the actual call. Additionally, the counselor can help the client identify potential challenges, such as long wait times or required documentation, and develop strategies to navigate them, ensuring that they feel prepared and empowered when seeking resources.
Through active collaboration, counselors can help clients recognize their strengths; build resilience to adapt, recover, and grow when faced with adversity; and gain confidence in advocating for themselves in settings that may otherwise feel disempowering. This approach fosters an environment where clients feel seen, supported, and empowered to navigate both personal and systemic challenges as they arise.
Termination Considerations
Finally, SDoMH need to be broached in the context of termination because of their impact on client dropout rates and early termination of treatment (Roberts et al., 2022). Although counselors are traditionally taught that termination should be gradual and that clients should share readiness, that is not always the reality because of the influence of social determinants. For example, electricity or phone service may be terminated because of an inability to pay bills, thereby limiting the client’s access to virtual sessions; limited transportation or childcare may prevent continued session attendance. Although counselors hope that they will be able to have a final session, that is not always realistic.
Nevertheless, the termination period represents a critical phase of the clinical process and must be attended to as part of the counseling process (Baum, 2005; Goode et al., 2017; Knox et al., 2011; Lee et al., 2023; Vasquez et al., 2008). Therefore, incorporating SDoMH broaching behaviors throughout the counseling relationship lays the foundation for effective clinical termination, even if termination occurs prematurely. For example, enhancing skills such as self-advocacy and incorporating discussions of resource identification and utilization can help empower clients in the event of unexpected termination.
When a formal termination is possible, continuing to broach SDoMH throughout that process can strengthen therapeutic gains and enhance overall therapeutic outcomes. As such, a counselor may engage clients in discussions around how SDoMH have impacted their therapeutic experience and goal attainment during counseling. This conversation can extend to how SDoMH may influence goal attainment after counseling, including brainstorming potential challenges that may arise. Discussions around how to apply skills gained during counseling to navigate those challenges and address relevant social determinants can also be impactful.
Additionally, a counselor should recognize that clients who discontinue care because of SDoMH-related barriers may choose to reengage in counseling once those barriers have been resolved. Thus, using a screen door approach (Pester Boyd et al., 2025) to termination can be helpful. This may include broaching the process of how clients can return to counseling (e.g., whether a new intake is required, potential waitlist considerations), available options for returning (e.g., in person, telehealth, in-home), and factors that might warrant reengagement in counseling.
Broaching SDoMH during termination should also include providing and discussing a list of referrals and resources to support clients beyond counseling. These resources should address both immediate mental health needs and the social determinants that impact overall well-being. Clients may wish to discuss these referrals and resources further to better understand the process of accessing them. This may include empowering clients with language they can use in various settings, such as navigating legal, social services, or medical resources, or even role-playing those conversations.
Given the potential role of SDoMH in early termination, such discussions should begin early in the clinical process. For example, a counselor might say, “You mentioned concerns that you may lose your health insurance. Can we talk through what that may look like if that were to happen?” This helps the counselor address factors related to counseling and mental health while also helping the client brainstorm challenges, solutions, and resources. Using the other SDoMH broaching behaviors to sustain these conversations throughout the counseling process can lead to effective client termination, even if termination occurs unexpectedly.
SDoMH Broaching Behaviors and Counselor Education
There is a growing call within counseling and related mental health fields to enhance SDoMH training and increase counselor readiness to broach these topics in practice (Gantt-Howrey et al., 2024; Johnson & Robins, 2021; Newton & Steele, 2025; Pester Boyd et al., 2025). As such, counselor education programs at the master’s and doctoral levels should incorporate discussion and clinical practice opportunities to help counselors-in-training (CITs) build awareness of SDoMH and develop best practices for broaching and addressing their impact on client well-being. Counselor education programs can embed SDoMH broaching across coursework, supervision, and experiential learning to prepare CITs for ethical and effective practice.
Integrating SDoMH in Coursework and Supervision
SDoMH training may be integrated in a number of counselor education courses and aligns with Council for the Accreditation of Counseling and Related Educational Programs (CACREP; 2023) standards (Gantt-Howrey et al., 2024; Pester Boyd et al., 2025). For example, suggested activities per course/CACREP core area include: (a) examining ethical considerations of broaching SDoMH, including advocacy responsibilities and potential boundary issues when addressing systemic barriers (i.e., professional orientation and ethics); (b) helping CITs connect the MSJCC to SDoMH through case study analysis (i.e., social and cultural diversity); (c) highlighting how developmental outcomes are shaped by SDoMH (i.e., human growth and development); (d) addressing how economic stability, employment, and educational inequities intersect with career counseling (i.e., career development); (e) having CITs practice broaching SDoMH through role-plays to become aware of how SDoMH affects rapport, trust, and client disclosure (i.e., counseling and helping relationships); (f) integrating experiential activities in which students design psychoeducational groups focused on wellness promotion, social support, or navigating systemic barriers (i.e., group counseling and group work); (g) teaching CITs to administer and interpret SDoMH screening tools and to incorporate results into case conceptualizations (i.e., assessment and evaluation); and (h) requiring that CITs design projects to investigate the impact of SDoMH on client outcomes or evaluate community-based interventions (i.e., research and program evaluation).
In addition, practicum and internship supervision provides an important space for modeling SDoMH broaching and supporting CITs in developing cultural humility and ethical decision-making through structured activities. Supervisors might, for example, guide CITs in identifying protective factors through a strengths mapping exercise that charts client supports across individual, relational, community, and cultural identities. They can also facilitate role-plays in which CITs practice acknowledging the protective role of extended family, religious communities, cultural traditions, or neighborhood engagement. Site supervisors may also connect practicum activities to systemic issues, such as collaborating with schools or agencies on wellness or resource initiatives. Finally, reflective supervision discussions can help CITs analyze their own responses to client strengths and SDoMH barriers and notice whether they default to problem-solving or strength-building.
SDoMH Broaching in Experiential Learning
Experiential activities provide CITs with opportunities across coursework, practicum, and internship to connect theory to practice. Experiential activities may include case analysis, role-plays, assessment practice, community engagement, and classroom discussions focused on ethical dilemmas. First, CITs can analyze case vignettes to examine how SDoMH affect individuals and families. For example, dyads might review a case through the lens of a specific determinant such as housing insecurity or underemployment, discuss the client’s presenting concerns in context, and brainstorm broaching strategies. Second, structured role-plays further allow students to develop confidence in directly addressing SDoMH with clients. For example, in triadic supervision, CITs can rotate roles as counselor, client, and observer, while peers and supervisors provide feedback on the clarity and effectiveness of broaching behaviors.
Third, assignments that incorporate SDoMH assessment tools (e.g., PRAPARE, WE CARE Survey) also prepare CITs to integrate systemic factors into case conceptualization. CITs may practice administering and interpreting screeners with hypothetical clients and then learn to translate results into simple, jargon-free explanations for use in sessions. Fourth, community engagement projects deepen this preparation by connecting CITs to the systemic realities clients face. Examples include researching local issues such as food insecurity and mapping neighborhood resources.
Ethical reflection is also a part of experiential learning. Classroom discussions may explore balancing advocacy efforts with professional boundaries or managing countertransference when counselors share similar systemic challenges with their clients. In addition, classroom dialogue can highlight positive determinants of mental health by fostering empathy and compassion. Storytelling circles or guided conversations can invite CITs to share their own lived experiences of belonging or exclusion and consider how these experiences influence their empathy and ethical decision-making.
Cultural humility is the foundation for effective SDoMH broaching. To strengthen cultural humility and responsiveness, counselor education programs can embed the abovementioned experiential learning strategies across coursework and supervision. Self-reflection exercises may include journaling prompts such as: “What identities give me privilege and how might that shape my assumptions with clients?”; “How have I responded when a client’s worldview or values conflicted with my own? What could I do differently to remain open and nonjudgmental?”; and “Recall a time you felt excluded, misunderstood, or powerless. How does that experience shape your empathy for clients navigating systemic inequities?” These reflections can be revisited across the program to track growth in self-awareness and cultural responsiveness.
Guided discussions can be facilitated through fishbowl discussions in which CITs share and listen to experiences of privilege, discrimination, or cultural differences, followed by role-plays that practice broaching these issues in counseling. Counselor educators can model effective broaching and provide feedback on student language and presence during these exercises.
Promoting Positive Social Determinants
In addition to addressing negative SDoMH (e.g., discrimination, housing insecurity, poverty, community violence), counselor educators can help CITs recognize and promote positive SDoMH that build resilience. These determinants include self-care practices, strong social support, inclusive environments, cultural affirmation, and opportunities for growth and connection. In addition, counselor educators can model and encourage strengths-based approaches that affirm client identities, such as validating cultural, gender, or spiritual expressions, during intake and treatment planning.
Wellness models and self-care planning can be integrated into coursework to benefit both CITs and future clients. For example, assignments might include creating a personal self-care plan; evaluating wellness models and interventions across cultures; or designing a client-friendly handout that translates wellness strategies (e.g., mindfulness, exercise, nutrition, social connection) into accessible, culturally responsive language.
Counselor education programs can embed advocacy projects across coursework to promote systemic conditions that support mental health equity. Examples include partnering with schools to develop anti-bullying campaigns; creating culturally inclusive mental health awareness workshops for parents and teachers; and collaborating with community agencies to expand access in areas such as housing assistance, after-school programs, health care access, or transportation services. CITs might also design stigma-reduction campaigns with public health organizations.
Service-learning projects can further immerse students in community contexts by mapping resources, conducting needs assessments, or partnering with organizations addressing issues such as refugee resettlement, food insecurity, or housing justice. As service-learning projects conclude, CITs can be asked, “What systemic barriers did you observe and how might they affect mental health?”; “How did this experience shape your understanding of your role as advocate?”; and “How might insights from this project influence how you broach SDoMH with clients in practice?”
Preparing for SDoMH Broaching Challenges
Although broaching SDoMH is a critical counseling skill, CITs may face obstacles when attempting to apply it in future practice. Agency settings may limit the time available to explore systemic issues, and some trainees may feel anxious about making missteps when discussing topics such as poverty, discrimination, or community violence. Clients themselves may hesitate to disclose experiences of marginalization out of fear of judgment or because such issues have been dismissed in past encounters with helping professionals.
Counselor educators can support student development by intentionally acknowledging these challenges within the classroom and supervision spaces. For example, they might facilitate a structured dialogue in which CITs share their concerns about broaching while the counselor educator normalizes discomfort and models language for difficult conversations. In these dialogues, they might ask CITs, “What feelings come up for you when you think about broaching SDoMH with a client?”; “What makes these conversations challenging in practice?”; or “How might you respond if a client resists or shuts down when SDoMH are introduced?” Such discussions can help trainees recognize that hesitation is common and that growth comes from practice and feedback rather than perfection.
Another way to strengthen readiness is through guided debriefing of role-plays or client simulations. After a broaching exercise, counselor educators can ask CITs to reflect on moments in which they felt stuck, explore how power dynamics may have shaped the exchange, and brainstorm alternative approaches. For instance, a CIT might role-play broaching transportation barriers with a hypothetical client who frequently misses sessions. After the role-play, other CITs within the classroom or supervision session could examine the CIT’s wording and the client’s reaction and then suggest alternative ways to frame the issue that both validate the client’s struggle and highlight systemic factors.
Counselor educators can also discuss the limitations of broaching within supervision. When reviewing case presentations, supervisors might ask CITs not only how they addressed SDoMH but also what structural limitations they encountered and how those shaped the counseling process. For example, a CIT might describe working with a client who lacked consistent childcare and therefore missed several sessions. The supervisor could guide the student to consider how systemic gaps in affordable childcare both constrained the counseling process and required exploration of advocacy or referral options. These conversations emphasize that although broaching can validate client experiences, it cannot by itself dismantle inequities, thus highlighting the importance of community collaboration and ongoing advocacy. As counselor educators intentionally and thoroughly analyze the process together, CITs can learn to approach barriers not as failures but as opportunities to deepen cultural humility.
Evaluating SDoMH Broaching Behaviors
Currently, there are no existing measures to evaluate SDoMH broaching behaviors, and future research should prioritize the development of validated tools to assess both counselor competency in SDoMH broaching and client perceptions of these efforts. Quantitative studies could focus on designing and testing new measures that assess the clarity, timing, cultural responsiveness, and impact of SDoMH broaching within the counseling relationship. Counseling researchers could utilize these instruments to conduct longitudinal studies and controlled intervention studies exploring the influence that SDoMH broaching has on client trust, client engagement in counseling, and therapeutic outcomes.
Until instruments specific to SDoMH broaching have been developed, researchers can use existing scales that independently measure broaching behaviors (e.g., Day-Vines et al., 2013; Day-Vines et al., 2024), SDoMH readiness (e.g., Johnson, 2023) and SDoMH assessment (e.g., Gantt-Howrey et al., 2024) to understand effective counseling behavior related to these constructs.
In addition to quantitative approaches, qualitative studies can help inform the impact of broaching behaviors on clients, CITs, and counselors. Studies that explore client experiences with counselors who broach SDoMH can provide contextual nuance and enhance multiculturally competent practice. For instance, interviews or focus groups with clients might uncover how broaching influences their feelings of safety, empowerment, or stigma reduction. Furthermore, researchers could conduct case studies of counselors in varied settings to examine how SDoMH broaching unfolds in practice. Data from session transcripts and client and counselor interviews could reveal additional best practices for addressing SDoMH, promoting positive social determinants, and counteracting challenges that counselors may have while broaching SDoMH.
Conclusion
Learning to effectively broach SDoMH provides an opportunity for counselors to further operationalize Ratts et al.’s (2016) MSJCC. As the cross-disciplinary call for universal SDoMH screening practices continues to grow across health professions, to remain leaders among the mental health professions, counselors must begin intentionally broaching SDoMH with clients. However, as a profession, broaching SDoMH may require reexamining the professional counselor identity, expanding advocacy roles, and reviewing ethical standards that may inadvertently create barriers to effectively addressing the impact of social determinants on clients’ lives.
Preliminary research suggests that effectively broaching SDoMH throughout the counseling process supports a number of short- and long-term benefits to clinical practice, which warrants its further integration and evaluation in the counseling profession. Counselors perceive that in the short term, broaching SDoMH strengthens the therapeutic relationship while fostering MSJCC (Pester Boyd et al., 2025). These early benefits can give way to enhanced client empowerment and improved access to interprofessional resources and services, both of which can lead to better treatment outcomes. Long-term, effectively broaching SDoMH can result in improved overall health of the client, improved community health, and decreased marginalization.
The MMBB (Day-Vines et al., 2020) and SDCM (Pester Boyd et al., 2025) provide needed frameworks to enhance these client outcomes. Using the integration of these frameworks as a foundation, we identified six SDoMH broaching behaviors for counselors: (a) counselor development, (b) client psychoeducation, (c) contextualization, (d) attending to differences of lived experience, (e) addressing emergent needs, and (f) SDoMH-informed termination practices. These broaching behaviors provide specific guidance for how to integrate SDoMH into counseling practice, which operationalizes the mandate of the MSJCC to address systemic and environmental factors impacting client mental health. We suggest that counselors integrate the identified SDoMH broaching behaviors throughout all stages of the therapeutic process to support a strong counselor–client relationship, enhanced client self-disclosure, increased client satisfaction, and improved therapeutic outcomes.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
Baum, N. (2005). Correlates of clients’ emotional and behavioral responses to treatment termination. Clinical Social Work Journal, 33(3), 309–326. https://doi.org/10.1007/s10615-005-4946-5
Brookover, D. L. (2024). The career development and social determinants framework: An integrative approach. Professional School Counseling, 28(1), 1–12. https://doi.org/10.1177/2156759X241290494
Center for Medicare & Medicaid Innovation. (n.d.). The accountable health communities health-related social needs screening tool. https://innovation.cms.gov/files/worksheets/ahcm-screeningtool.pdf
Compton, M. T., & Shim, R. S. (2015). The social determinants of mental health. Focus, 13(4), 419–425. https://doi.org/10.1176/appi.focus.20150017
Compton, M. T., & Shim, R. S. (2020). Why employers must focus on the social determinants of mental health. American Journal of Health Promotion, 34(2), 215–219. https://doi.org/10.1177/0890117119896122c
Council for the Accreditation of Counseling and Related Educational Programs. (2023). 2024 CACREP standards. https://www.cacrep.org/wp-content/uploads/2024/04/2024-Standards-Combined-Version-4.11.2024.pdf
Day-Vines, N. L., Bryan, J., and Griffin, D. (2013). The Broaching Attitudes and Behavior Survey (BABS): An exploratory assessment of its dimensionality. Journal of Multicultural Counseling and Development, 41(4), 210–223. https://doi.org/10.1002/j.2161-1912.2013.00037.x
Day-Vines, N. L., Cluxton-Keller, F., Agorsor, C., & Gubara, S. (2021). Strategies for broaching the subjects of race, ethnicity, and culture. Journal of Counseling & Development, 99(3), 348–357. https://doi.org/10.1002/jcad.12380
Day-Vines, N. L., Cluxton-Keller, F., Agorsor, C., Gubara, S., & Otabil, N. A. A. (2020). The multidimensional model of broaching behavior. Journal of Counseling & Development, 98(1), 107–118. https://doi.org/10.1002/jcad.12304
Day-Vines, N. L., Zhang, J., Cluxton-Keller, F., Hicks, D., Jones, C., Spann, R. T., Daga, D., & Agorsor, C. (2024). The development and validation of an instrument to examine clients’ perspectives about their counselors’ ability to broach racial, ethnic, and cultural concerns. Journal of Multicultural Counseling and Development, 52(3), 173–188. https://doi.org/10.1002/jmcd.12300
Depauw, H., Van Hiel, A., Talal, H., Dierckx, K., Geenen, F., Valcke, B., & De Clercq, B. (2025). The development of the Broaching Assessment Scale: A client-rated measure of therapists’ broaching behaviour in clinical counselling. Psychotherapy Research, 35(3), 424–440. https://doi.org/10.1080/10503307.2024.2301948
Dolan, N., Simmonds-Buckley, M., Kellett, S., Siddell, E., & Delgadillo, J. (2021). Effectiveness of stress control large group psychoeducation for anxiety and depression: Systematic review and meta-analysis. British Journal of Clinical Psychology, 60(3), 375–399. https://doi.org/10.1111/bjc.12288
Drinane, J. M., Owen, J., & Tao, K. W. (2018). Cultural concealment and therapy outcomes. Journal of Counseling Psychology, 65(2), 239–246. https://doi.org/10.1037/cou0000246
Gantt-Howrey, A., Lin, M., Shaikh, A., Johnson, K. F., Preston, J. W., & Wilson, L. (2024). Assessing social determinants of mental health: Client experiences and counselor practices. Journal of Counseling & Development, 102(4), 394–405. https://doi.org/10.1002/jcad.12519
Garg, A., Butz, A. M., Dworkin, P. H., Lewis, R. A., Thompson, R. E., & Serwint, J. R. (2007). Improving the management of family psychosocial problems at low-income children’s well-child care visits: The WE CARE Project. Pediatrics, 120(3), 547–558. https://doi.org/10.1542/peds.2007-0398
Goode, J., Park, J., Parkin, S., Tompkins, K. A., & Swift, J. K. (2017). A collaborative approach to psychotherapy termination. Psychotherapy, 54(1), 10–14. https://doi.org/10.1037/pst0000085
Johnson, K. F. (2023). Development and initial validation of the Addressing Client Needs with Social Determinants of Health Scale (ACN: SDH). BMC Health Services Research, 23(1), 374. https://doi.org/10.1186/s12913-023-09292-z
Johnson, K. F., & Brookover, D. L. (2021). School counselors’ knowledge, actions, and recommendations for addressing social determinants of health with students, families, and in communities. Professional School Counseling, 25(1). https://doi.org/10.1177/2156759X20985847
Johnson, K. F., Cunningham, P. D., Tirado, C., Moreno, O., Gillespie, N. N., Duyile, B., Hughes, D. C., Scott, E. G., & Brookover, D. (2023). Social determinants of mental health considerations for counseling children and adolescents. Journal of Child and Adolescent Counseling, 9(1), 21–33. https://doi.org/10.1080/23727810.2023.2169223
Johnson, K. F., Gantt-Howrey, A., Duyile, B. E., Robins, L. B., & Dockery, N. (2024). Career counselors addressing social determinants of mental health in rural communities. The Professional Counselor, 14(1), 1–14. https://doi.org/10.15241/kfj.14.1.1
Johnson, K., & Robins, L. B. (2021). Counselor educators experiences and techniques teaching about social-health inequities. Journal of Counselor Preparation and Supervision, 14(4). https://research.library.kutztown.edu/jcps/vol14/iss4/ 7
King, K. M., & Borders, L. D. (2019). An experimental investigation of White counselors broaching race and racism. Journal of Counseling & Development, 97(4), 341–351. https://doi.org/10.1002/jcad.12283
Knox, S., Adrians, N., Everson, E., Hess, S., Hill, C., & Crook-Lyon, R. (2011). Clients’ perspectives on therapy termination. Psychotherapy Research, 21(2), 154–167. https://doi.org/10.1080/10503307.2010.534509
Lee, P.-S., Wang, L.-F., & Swift, J. K. (2023). Clients’ and counselors’ termination decisions and experiences in counseling. Current Psychology, 42, 3734–3744. https://doi.org/10.1007/s12144-021-01725-4
Lenz, A. S., & Lemberger-Truelove, M. E. (2023). The social determinants of mental health and professional counseling: A call to action. Journal of Counseling & Development, 101(4), 375–380. https://doi.org/10.1002/jcad.12489
Lenz, A. S., & Litam, S. D. A. (2023). Integrating the social determinants of mental health into case conceptualization and treatment planning. Journal of Counseling & Development, 101(4), 416–428. https://doi.org/10.1002/jcad.12487
Lund, C., Brooke-Sumner, C., Baingana, F., Baron, E. C., Breuer, E., Chandra, P., Haushofer, J., Herrman, H., Jordans, M., Kieling, C., Medina-Mora, M. E., Morgan, E., Omigbodun, O., Tol, W., Patel, V., & Saxena, S. (2018). Social determinants of mental disorders and the sustainable development goals: A systematic review of reviews. The Lancet Psychiatry, 5(4), 357–369. https://doi.org/10.1016/S2215-0366(18)30060-9
Luo, H., Li, Y. L., Luo, X. J., Xia, L., Xiao, J., Xiao, H., & Chen, J. (2025). The efficacy of psychoeducation-based programs on internalized stigma in patients with schizophrenia: A systematic review and meta-analysis. Psychiatry Research, 350, 116540. https://doi.org/10.1016/j.psychres.2025.116540
Mason, S., Ragan, M., Gilbert, S. H., & Lenz, A. S. (2023). Social determinants of mental health: Implications for measurement, research, and evaluation. Journal of Counseling & Development, 101(4), 440–448. https://doi.org/10.1002/jcad.12490
Neal Keith, S., Coleman, M. L., Hicks Becton, L. Y., & Springfield, J. (2023). Assessing the social determinants of mental health in counseling practice. Journal of Counseling & Development, 101(4), 381–391. https://doi.org/10.1002/jcad.12470
Newton, C., & Steele, J. M. (2025). The broaching readiness framework: A path for psychologists to embrace cultural opportunities. Counselling Psychology Quarterly, 38(4), 1135–1152. https://doi.org/10.1080/09515070.2025.2458034
Office of Disease Prevention and Health Promotion. (2025). Social determinants of health. https://odphp.health.gov/healthypeople/objectives-and-data/social-determinants-health
Owen, J., Tao, K. W., Imel, Z. E., Wampold, B. E., & Rodolfa, E. (2014). Addressing racial and ethnic microaggressions in therapy. Professional Psychology: Research and Practice, 45(4), 283–290. https://doi.org/10.1037/a0037420
Pester, D. A., Jones, L. K., & Talib, Z. (2023). Social determinants of mental health: Informing counseling practice and professional identity. Journal of Counseling & Development, 101(4), 392–401. https://doi.org/10.1002/jcad.12473
Pester Boyd, D. A., Hays, D. G., & Jones, L. K. (2025). Assessing and addressing social determinants of mental health in counseling: A grounded theory investigation. Journal of Counseling & Development, 103(4), 469–483. https://doi.org/10.1002/jcad.70003
PRAPARE. (2022). Protocol for responding to and assessing patient assets, risks, and experiences: Implementation and action toolkit. https://prapare.org/wp-content/uploads/2022/09/Full-Toolkit_June-2022_Final.pdf
Ratts, M. J., Singh, A. A., Nassar-McMillan, S., Butler, S. K., & McCullough, J. R. (2016). Multicultural and social justice counseling competencies: Guidelines for the counseling profession. Journal of Multicultural Counseling and Development, 44(1), 28–48. https://doi.org/10.1002/jmcd.12035
Roberts, T., Esponda, G. M., Torre, C., Pillai, P., Cohen, A., & Burgess, R. A. (2022). Reconceptualising the treatment gap for common mental disorders: A fork in the road for global mental health? The British Journal of Psychiatry, 221(3), 553–557. https://doi.org/10.1192/bjp.2021.221
Robins, L. B., Johnson, K. F., Duyile, B., Gantt-Howrey, A., Dockery, N., Robins, S. D., & Wheeler, N. (2022). Family counselors addressing social determinants of mental health in underserved communities. The Family Journal, 31(2), 213–221. https://doi.org/10.1177/10664807221132799
U.S. Department of Health and Human Services. (2023). Our epidemic of loneliness and isolation: The U.S. Surgeon General’s advisory on the healing effects of social connection and community. https://www.hhs.gov/sites/default/files/surgeon-general-social-connection-advisory.pdf
Vasquez, M. J. T., Bingham, R. P., & Barnett, J. E. (2008). Psychotherapy termination: Clinical and ethical responsibilities. Journal of Clinical Psychology, 64(5), 653–665. https://doi.org/10.1002/jclp.20478
World Health Organization. (2025). Social determinants of health. https://www.who.int/health-topics/social-determinants-of-health#tab=tab_1
Zhang, N., & Burkard, A. W. (2008). Client and counselor discussions of racial and ethnic differences in counseling: An exploratory investigation. Journal of Multicultural Counseling and Development, 36(2), 77–87. https://doi.org/10.1002/j.2161-1912.2008.tb00072.x
Danielle Pester Boyd, PhD, NCC, LPC (TX), RPT, is an assistant professor at Auburn University. Laura K. Jones, PhD, is an associate professor at the University of North Carolina at Asheville. Courtney Maier, MEd, NCC, APC, is a doctoral student at Auburn University. Danica G. Hays, PhD, is a dean and professor at the University of Nevada Las Vegas. Correspondence may be addressed to Danielle Pester Boyd, 345 West Samford Avenue, Suite 3188, Auburn, AL 36849, danielle.boyd@auburn.edu.
Aug 26, 2025 | Volume 15 - Issue 3
Julie C. Hill, Toni Saia, Marcus Weathers, Jr.
Ableism is often neglected in conversations about oppression and intersectionality within counselor education programs. It is vital to expand our understanding of disability as a social construct shaped by power and oppression, not a medical issue defined by diagnosis. This article is a call to action to combat ableism in counselor education. Actionable recommendations include: (a) encouraging professionals to define and discuss ableism; (b) including disability representation in course materials; (c) engaging in conversations about disability with students; (d) collaborating with, responding to, and supporting disabled people and communities; and (e) reflecting on personal biases to help dismantle ableism within counselor education. Implications for counselor educators highlight the ongoing need for more ableism content within the profession.
Keywords: ableism, disability, counselor education, representation, biases
Disability is rarely examined through intersectionality and critical consciousness, despite its deep connections to race, class, gender, and other social identities (Berne et al., 2018). As the United States becomes increasingly diverse, the need for counselors who can competently address the complex, intersecting needs of disabled people has never been more urgent (Dollarhide et al., 2020). Disabled people are the largest and fastest-growing minority group, with approximately 60 million people reporting some form of disability (Elflein, 2024). Despite this increasing prevalence, ableism, known as the systemic discrimination and exclusion of disabled people, remains persistent in our society. Slesaransky-Poe and García (2014) further discuss ableism as the belief that disability makes someone less deserving of many things, including respect, education, and access within the community.
Ableism and ableist beliefs have profoundly shaped how society perceives and interprets the disability experience. Historically, the medical model has framed disability as an inherent defect within the individual, requiring treatment, rehabilitation, or correction to restore “normal” functioning (Leonardi et al., 2006). This deficit-based perspective, reinforced by legal definitions, has shaped societal attitudes and policies, often prioritizing intervention over community integration. In contrast, the social model of disability shifts the focus from the individual to the broader societal structures, emphasizing how inaccessible environments, exclusionary policies, and ableist attitudes create disabling conditions (Bunbury, 2019; Friedman & Owen, 2017; Shakespeare, 2006). This model asserts that disability is not simply a medical issue, but a social justice concern requiring systemic change to remove barriers and promote full participation. Within counselor education programs, the biopsychosocial model is often taught as a more integrative framework that acknowledges disability as a complex interplay of biological, psychological, and social factors. Although medical interventions may be necessary for some individuals, this model emphasizes addressing environmental and attitudinal barriers contributing to marginalization. By adopting this holistic approach, counselors can better advocate for equity, inclusion, and meaningful accessibility for all.
This article provides an asset-based framework that views disability as a valuable aspect of diversity rather than a deficit or limitation. This approach recognizes the strengths, perspectives, and contributions that disabled people bring to communities and educational spaces (Olkin, 2002; Perrin, 2019). By embracing disability as an aspect of diversity, this framework challenges societal norms rooted in ableism, which often prioritize conformity and cure over anti-ableism (Bogart & Dunn, 2019). Through this lens of power and oppression, disability is celebrated as a source of innovation, creativity, and cultural richness, encouraging practices that empower disabled individuals to thrive both in the classroom and in the community. To reinforce this shift in thinking to disability as an asset, we use identity-first language, recognizing that many disabled people prefer it as a positive affirmation of their lived experiences and their connection to the disability community (Sharif et al., 2022; Taboas et al., 2023).
Intersectionality and Disability
Scholars recognize intersectionality as an analytical tool to investigate how multiple systems of oppression interact with an individual’s social identities, creating complex social inequities and unique experiences of oppression and privilege for individuals with multiple marginalized identities (Collins & Bilge, 2020; Crenshaw, 1989; Grzanka, 2020; Moradi & Grzanka, 2017; Shin et al., 2017). The topic of disability is often absent in conversations regarding power, oppression, and privilege (Ben-Moshe & Magaña, 2014; Erevelles & Minear, 2010; Frederick & Shifrer, 2018; Mueller et al., 2019; Wolbring & Nasir, 2024) despite the potential for disability to intersect with other marginalized identities (e.g., racial/ethnic identity, gender identity, socioeconomic status, religious and spiritual beliefs, citizenship/immigration status) that lead to intersectionality-based challenges that conflict with the marginalization of being disabled (Wolbring & Nasir, 2024). For example, Lewis and Brown (2018) condemned the lack of accountability in reporting on disability, race, and police violence, which often irresponsibly neglects the coexistence of disability in conversations of experienced violence. Using the framework of intersectionality responsibly in disability discourse within counselor education holds significant potential for the professional development of counselors to work toward unmasking and dismantling ableism.
Challenges and Gaps in Anti-Ableism in Counselor Education and Training
How counselor educators teach about disability is crucial to dismantling ableism, yet history reveals a troubling lack of cultural humility in educational approaches. Cultural humility is a process-oriented approach that continuously emphasizes the counselor’s openness to learn about a client’s culture and invites counselors to consistently incorporate self-reflective activities to enhance their self-awareness (Mosher et al., 2017). Although cultural humility may be well intended, it may also have a harmful impact and fall flat if inherent biases go unrecognized. For example, counselor educators heavily relied on simulation exercises to address disability in the classroom (e.g., having students blindfold themselves for an activity to simulate blindness or having them sit in a wheelchair for a short period). Simulation exercises reinforce a deeply medicalized and reductive view of disability, one rooted in fear, pity, and misconception, ultimately erasing disability as both a culture and an identity (Öksüz & Brubaker, 2020; Shakespeare & Kleine, 2013). Beatrice Wright (1980, as cited in Herbert, 2000), cautioned that simulation experiences evoke fear, aversion, and guilt. These exercises rarely foster meaningful or constructive perspectives on disability. Instead of deepening understanding, these exercises risk reinforcing harmful stereotypes, further marginalizing disabled individuals rather than empowering them. Instead of disability simulations, honor the voices and experiences of disabled individuals through their narratives, such as Being Heumann by Judy Heumann, as well as documentaries and movies like Crip Camp, Patrice, or CODA. Contact with disabled individuals has been shown to reduce stigma against disabled people (Feldner et al., 2022; Smith et al., 2011). Additionally, incorporate analyzing ableism through case studies, readings, or media, followed by a structured discussion.
Topics of multiculturalism and diversity have increased over the years; the same cannot be said for disability (Rivas, 2020). Davis (2011) poignantly asked, “Is this simply neglect, or is there something inherent in the way diversity is considered that makes it impossible to recognize disability as a valid human identity?” (p. 4). More than a decade later, this question remains painfully relevant. Atkins et al. (2023) explored this issue through a study using the Counseling Clients with Disabilities Scale to evaluate professionals’ attitudes, competencies, and preparedness when working with disabled clients. The findings underscore the critical need for education and exposure to disability-related topics in counselor training, demonstrating that such efforts improve competency, reduce biases, and foster more inclusive, equitable, and empowering support. However, disability continues to receive significantly less attention than other cultural and identity groups in professional training and discourse (Deroche et al., 2020).
Furthermore, ableist microaggressions continue to be a concern for disabled individuals. Cook and colleagues (2024) conducted a study looking at microaggressions experienced by disabled individuals and found four categories of microaggressions: minimization, denial of personhood, otherization, and helplessness. They also found that experiencing ableist microaggressions affected participants’ mental health and wellness. Additionally, they found that those with visible disabilities were more likely to experience ableist microaggressions than those with invisible disabilities. Given these findings, counselor educators need to be aware that ableist microaggressions exist, what those microaggressions may sound like, and how they impact disabled clients.
Concerns exist about the extent to which counselor education programs cover disability content; there is also a need to examine instructors’ preparedness for covering such content. In a survey of counselor educators in programs accredited by the Council for the Accreditation of Counseling and Related Educational Programs (CACREP), 36% of the faculty surveyed believed their program was ineffective at addressing disability topics and that programs did not address disability and ableism to the extent necessary to produce competent professionals. Only 10.6% felt their program to be “very effective” in this content area, with the belief that their students were only somewhat prepared to work with disabled people (Feather & Carlson, 2019). Notably, these oversights in education translate into inadequacy in practice. A sample of mental health professionals who all reported working with disabled clients indicated the least amount of perceived disability competence in skills, the second least competence in knowledge, and the most competence in awareness (Strike et al., 2004). Faculty self-assessment of their ability to teach disability-related content was strongly linked to their prior work or personal experience with disability. This highlights the importance of integrating exposure to and training on disability-related concepts throughout core areas (Pierce, 2024). Although separated by a decade, these studies can be tied to a unifying, persistent issue: the lack of disability competence in counseling and counselor education spaces.
The 2024 CACREP standards call for an infusion of disability competencies into counseling curricula (CACREP, 2023), meaning that counselor educators and counselors-in-training must reimagine the available literature to provide adequate professional development and growth. Pierce (2024) advised that disability competence areas be focused on the following topics: accessibility, able privilege, disability culture, and disability justice. We must seek to dismantle ableism by infusing disability into curricula in an authentic manner that highlights the societal values and attitudes in which multiple forms of oppression work in tandem to create unique, intersectional experiences for disabled people.
Training Recommendations for Counselor Education Programs
The authors aim to ensure counselor educators have tangible strategies to dismantle ableism and teach their students to do the same. Counselor educators and counselors-in-training must look inward and rid themselves of negative attitudes and biases to eradicate ableism. Part of this process includes the critical skill of self-reflection and examining and understanding biased and ableist beliefs held by individuals and perpetuated by society. Until that happens, counselors will continue to do a disservice to disabled people (Friedman, 2023). For students who have never interacted with disabled people or thought about ableism, these conversations and strategies have the very real possibility of making them uncomfortable. Discomfort is okay. Disabled people often feel awkward or out of place every day because of ableism. It is not our job as counselor educators to make students comfortable; it is our job to make them competent, informed, and ethical professionals.
The following are five tangible strategies to thoughtfully and intentionally dismantle ableism. These strategies are purposefully broad and aim to expose counseling professionals and those in training to an intersectional perspective of disability that acknowledges disability as a valid aspect of diversity, identity, and culture. Rather than siloing these discussions to disability-related training, these strategies belong in all settings within counseling. Counseling professionals must include ableism in the conversations happening in places where they learn and work to shift the way they think, view, respond to, and construct disability. To begin, counselor education programs should consider hosting a workshop or seminar focused on ableism by disabled people to ensure that all students and faculty are on the same page and are using the same terminology. Once this has been established, ableism and disability content and knowledge should be incorporated into lectures, assignments, discussions, and exams across the counselor education curriculum. Further information on this integration is described in the first strategy below.
Define Ableism
One of the factors that further perpetuates ableism is the lack of clarity on what ableism is and how it intersects with other forms of oppression. Counselor educators must share definitions of ableism that center on the perspective of the disabled community. Talia Lewis (2022) provided a working definition of ableism that disabled Black/negatively racialized communities developed:
A system of assigning value to people’s bodies and minds based on societally constructed ideas of normalcy, productivity, desirability, intelligence, excellence, and fitness. These constructed ideas are deeply rooted in eugenics, anti-Blackness, misogyny, colonialism, imperialism, and capitalism. This systemic oppression leads to people and society determining people’s value based on their culture, age, language, appearance, religion, birth or living place, “health/wellness,” and/or their ability to satisfactorily re/produce, “excel,” and “behave.” You do not have to be disabled to experience ableism. (para. 4–6)
This definition expands on the definition provided earlier of ableism as the systemic discrimination and exclusion of disabled people. It rejects the notion that ableism can be dismantled or separated from other forms of oppression (e.g., racism, sexism, and other systems of oppression). Within counseling curricula, we often use the term intersectionality, but it is impossible to address intersectionality with our students if we do not thoughtfully include ableism. We should challenge the idea that disability is a monolithic experience as we seek to build a more complex, interconnected, and whole understanding of disability (Mingus, 2011).
It is also essential to acknowledge internalized ableism, which is ableism directed inward when a disabled person consciously or unconsciously believes in the harmful messages they hear about disability. They project negative feelings onto themselves. They start to believe and internalize the message that society labels disability as inferior. They begin to accept the stereotypes. Internalized ableism occurs when individuals are so heavily influenced by stereotypes, misconceptions, and discrimination against disabled people that they start to think that their disabilities make them inferior (Presutti, 2021). For example, a disabled student may not participate in class because they believe their contributions are inferior compared to their nondisabled peers, or a disabled client may experience feeling undeserving, undesirable, and burdensome.
To effectively implement this awareness, ask students to define ableism in their own words. Coming up with their definition of ableism encourages critical thinking and allows the counselor educator to gauge students’ existing understanding. Then, introduce the Lewis (2022) definitions above to provide a more comprehensive framework. To reinforce these concepts, incorporate case studies illustrating real-world examples of ableism. Analyzing these cases in class discussions or group activities will help students identify ableist structures, challenge assumptions, and explore solutions for creating more welcoming environments. Counselors can examine ableism in societal contexts by viewing movies or television shows that feature disabled characters and analyzing how ableism is portrayed in media. Because of societal barriers to access and the taboos surrounding discussions of disability, the entertainment and news media serve as a key source for many people to form opinions about disability and disabled individuals. Unfortunately, these portrayals are limited and often spread misinformation and harmful stereotypes (Pierce, 2024). One way to help combat this could be by watching a movie or show together as a class and then having a discussion or having students watch on their own and write a short reflection followed by a class discussion. Some suggested movies include Crip Camp, Murderball, The Temple Grandin Story, Patrice, and Out of My Mind. Some suggested television shows include Speechless, Love on the Spectrum, Special, Raising Dion, Atypical, and The Healing Powers of Dude.
Include Disability Representation in Course Content
The phrase “representation matters” also applies to disability. Counselor educators should include disability and discussions of the impact of systemic ableism throughout course content, not only in a single lecture or reading on the course syllabus. Decisions about course content send powerful messages about what the counselor educator, the program, and the broader counseling profession prioritize and value. Including or excluding specific topics reflects the educator’s perspective and shapes future counselors’ professional identity and competencies. When disability is overlooked or inadequately addressed, it signals to students that it is not a central concern in counseling practice, which reinforces systemic gaps in knowledge, awareness, and advocacy. To counter this erasure and to ensure meaningful representation, intentionally incorporate guest speakers, videos, readings, memoirs, and research that center on the perspectives of disabled people. This gives students an authentic and multifaceted understanding of disability beyond theoretical discussions. Consider integrating a book or memoir that centers a disabled perspective alongside the course textbook to bridge the gap between academic content and real-life experiences. This approach not only deepens students’ engagement but also challenges ableist assumptions by highlighting the lived realities, resilience, and contributions of disabled people.
Engage in Conversation About Disability With Students
Disability is not a bad word. Counselor educators must instill this simple yet profound truth in students. Euphemisms like differently abled, handicapable, or special needs perpetuate ableism when used in place of the term disability, implying that disability is something shameful or in need of softening; they do more harm than good. Counselor educators must allow students the opportunity to engage in discussion about disability to challenge the idea that disability is taboo and move into a space where students can appreciate that disability is a natural part of life. Counselor educators must foster a safe and supportive learning community that allows students to engage in dialogue and discussion about their beliefs and experiences that have shaped their beliefs, and examine how those beliefs led to the development or perpetuation of ableist ideas and microaggressions. This allows students to learn, grow, and reshape their beliefs and understanding together. This quote sums it up best: “Disabled people are reclaiming our identities, our community, and our pride. We will no longer accept euphemisms that fracture our sense of unity as a culture: #SaytheWord” (Andrews et al., 2019, p. 6). To empower students to #SayTheWord in both classroom discussions and professional practice, dedicate time, especially during the first weeks of class, to explicitly affirm that disability is not a bad word. Normalize its use by providing historical context, sharing first-person perspectives, and emphasizing the importance of language in shaping attitudes. By reinforcing disability as an act of recognition rather than avoidance, you help students develop confidence in using identity-affirming language and challenging the stigma often associated with the term.
Collaborate, Respond, and Support Disabled People
Counselor educators, counselors, and counselors-in-training should seek opportunities to listen to, respond to, support, and collaborate with disabled counselors and other disabled scholars. Thoughtful collaborations allow for authentic exposure and conversation that support the unlearning of ableist beliefs. This approach is consistent with the disability rights mantra “nothing about us without us” (Charlton, 1998, p. 3), which implies that no change can occur without the direct input of disabled individuals. One opportunity for collaboration includes professional conferences and attending presentations by disabled academics and professionals. Other opportunities for collaboration include working with and supporting local disabled business owners and seeking out organizations such as independent living centers to bring in disabled speakers to share their lived experience and interactions with ableism and microaggressions. Be sure to compensate these individuals for their time so that the work of collaboration is mutually beneficial to all parties.
Disabled people are the experts of their experiences, not professionals. This statement is not synonymous with implementing a client-centered or person-centered approach. Instead, the focus of this statement is to make sure counselors have the tools to trust, support, uplift, and dismantle ableism with disabled clients. If it starts in the classroom, counselors-in-training will be better prepared in practice and life outside of work. As professionals know, trust in the counselor-client relationship is essential for the disabled community. It often develops when individuals feel heard, trusted, and validated, rather than being second-guessed or minimized, especially as they share about the external and internal ableism they face daily. Lund (2022) recommended consulting with both disabled psychologists and trainees to bring a “critical insider-professional perspective” (p. 582) to the profession. By consulting and bringing these disabled professionals in for training or speaking about personal experiences, we can ensure that disabled voices are heard and recognized.
Another way to amplify disabled voices is through the teaching of disability justice. The Disability Justice framework affirms that every person’s body holds inherent value, power, and uniqueness. It recognizes that identity is shaped by the interconnected influences of ability, race, gender, sexuality, class, nationality, religion, and other factors. It stresses the importance of viewing these influences together rather than separately. From this perspective, the fight for a just society must be grounded in these intertwined identities while also acknowledging Berne et al.’s (2018) critical insight that the current global system is “incompatible with life” (para. 13). Central principles of disability justice, such as centering leadership by those most impacted, fostering interdependence, ensuring collective access, building cross-disability solidarity, and pursuing collective liberation, prioritize intersectionality and cross-movement collaboration to guarantee that no one is excluded or left behind. (Pierce, 2024).
Helping students understand and internalize these ideas and principles should lead to the development of more aware and anti-ableist counselors in several ways. Rather than viewing client struggles as isolated or purely personal issues, understand that many forms of suffering, especially those faced by disabled people and people with intersecting marginalized identities, are rooted in larger social, economic, and political systems that devalue certain lives. For example, ableism, racism, and capitalism often create conditions that threaten people’s survival, whether through limited access to health care, environmental injustice, or social exclusion.
Counselors-in-training should be attuned to how multiple aspects of identity (such as disability, race, gender, and class) interact to shape each client’s lived experience. This approach moves counseling away from a one-size-fits-all perspective and helps address the unique, layered barriers that clients face. Traditional counseling and counselor preparation often focus on assisting clients to adapt to oppressive systems. The Disability Justice perspective instead calls for counselors-in-training to see their role as also advocating for systemic change, working toward environments and policies that are actually supportive of all people’s well-being. Rather than idealizing independence, disability justice values interdependence and community care. Counselors and counselors-in-training can foster this by helping clients build supportive networks and by modeling collaborative, relational approaches in practice.
Regularly Reflect on Personal Biases and Be Open to Feedback
Counselor educators often ask counselors-in-training to reflect on their own biases in terms of race, gender, and sexual orientation. However, ableism and disability are often forgotten or left out of those conversations. It is essential for these conversations about bias to include disability so that everyone has opportunities to explore and discuss their own potential biases. Embedding disability representation in the classroom allows everyone to see how they respond to disabled people, especially when that representation is in the form of case studies and client role-play. Then, everyone, including supervisors, can constructively receive feedback from a trusted figure and can change or improve their reactions and responses if necessary. Furthermore, counselor educators and counselors-in-training can keep reflective journals, seek supervision or peer discussions, and review case notes with an anti-ableist lens, which can help identify areas for growth. Additionally, counselor educators should actively solicit feedback from the disability community, welcoming their perspectives without defensiveness. When possible, attend training led by disabled professionals and the disabled community to reinforce a commitment to continuous learning and accountability.
Implications for Counselor Educators
Counselor educators are responsible for training counselors to work with all types of clients, including disabled clients. Counselors will encounter disabled clients, no matter the setting that they are working in. Disability can impact anyone and does not discriminate across gender, race, socioeconomic status, sexual orientation, or geographic location. Disability is the one minority group that anyone can become a part of at any time in their life. Most people will age into disability as they get older (Shapiro, 1994). Counselor educators need to be sure that counselors are confronting and dismantling their own ableism and ableist beliefs and that they understand that they may need to assist clients in processing their own experiences with ableism in society and interactions with others. One self-assessment for self-reflection and insight is the Systematic Ableism Scale (SAS; Friedman, 2023). The SAS has four underlying themes: individualism, recognition of continuing discrimination, empathy for disabled people, and excessive demands. The SAS is a tool that can be used to help understand how contradicting disability ideologies manifest in modern society to determine how best to counteract them. By using this assessment as a self-evaluation tool, both students and counselor educators can identify where their beliefs may be problematic or ableist and then set goals to address and improve in those areas.
We recommend that counselors intentionally occupy spaces where discussions on disability advocacy are occurring. Universities are often regarded as a primary source of knowledge production, but a common misconception is that the people themselves produce the knowledge. The reality is that not all disability content is produced by disabled individuals or organizations. Thus, we encourage counselor educators to expand access to knowledge about disability by seeking spaces outside the institution that share insider perspectives on the disability experience and organizations dedicated to empowering disabled communities. This may involve engaging with informal educational organizations such as Sins Invalid, AXIS Dance Company, and Krip Hop Nation or getting involved with formal professional organizations such as APA Division 22, the American Rehabilitation Counseling Association, or the National Rehabilitation Counseling Association. Some strategies that can be used to advocate for and in support of disabled clients include client-centered advocacy, understanding disability as a cultural identity, and building knowledge of the disability rights movement, ableism, and intersectionality, as well as integrating disability-inclusive language, avoiding ableist assumptions, and incorporating clients’ lived experiences into treatment (Chapin et al., 2018; Smart, 2015; Smith et al., 2011).
The foundation for a competent and qualified counselor begins with their training. This training can be formal education or ongoing professional development. For those responsible for educating counselors-in-training, laying the foundation for anti-ableism practices begins in the classroom. A universal design for learning (UDL) framework, developed by the Center for Applied Special Technology (CAST, 2018), aims to create accessible material and inclusive environments that are usable for all people by intentionally incorporating multiple representations of content to enhance student expression of learning and increase a variety of opportunities for engagement with the learning environment (Black et al., 2015; Dolmage, 2017; Fornauf & Erickson, 2020). UDL principles support anti-ableist practice by encouraging an ongoing partnership between students and instructors that facilitates consistent and practical feedback to promote student belongingness (Hennessey & Koch, 2007; Oswald et al., 2018). Promoting belonging and acceptance in counselor education programs requires intentional strategies that foster inclusivity, respect for diversity, and a strong sense of community. Effective techniques include: 1) Use inclusive curriculum design. Integrate diverse perspectives throughout the curriculum, with special attention paid to marginalized voices, such as disabled voices. 2) Use culturally responsive pedagogy. This includes employing a range of instructional methods to cater to diverse learning styles. Use trauma-informed practices by creating a learning environment that is sensitive to trauma, both past and present. 3) Implement community-building activities such as structuring programs around cohorts and encouraging the formation of affinity groups and peer support groups. 4) Encourage active dialogue and reflection around tough conversations such as diversity, ableism, inequality, and marginalization. This can be done both in person and online via discussion boards. Faculty can also encourage students to explore their thoughts, reflections, and experiences around issues of identity, belonging, and ableism in a reflective journal. 5) Collect feedback to guide continuous improvement. Faculty can assess students’ experiences with inclusion and ableism through climate surveys.
Additionally, the adoption of multiple methods for delivering information in alternate formats and continuous assessment of student progress reduces barriers to student engagement and expression in the learning environment, which in turn systematically challenges normative ableist practice that values a one-size-fits-all perspective that often neglects disabled thought and existence in pedagogical practices (Oswald et al., 2018). UDL strategies to disrupt ableist thought and practices may include using closed captioning on visual multimedia content (e.g., videos, PowerPoint presentations), incorporating movement breaks, creating interactive activities (e.g., role-play activities, gamification, debates on critical topics), and receiving feedback on instruction.
Hill and Delgado (2023) discussed the importance of including disability coursework and content across multiple domains to effectively address ableism in counselor education programs. Building upon their work, we suggest that the following key types of coursework and content be included. At a minimum, disability content should be integrated into the core CACREP curriculum areas: professional counseling orientation and ethical practice, social and cultural foundations, lifespan development, career development, counseling practice, group counseling, assessment and diagnosis, and research and program evaluation (CACREP, 2023).
Foundational Disability Studies
Students should explore and understand how ableism developed and its systemic nature, especially in the current political climate (Campbell, 2009; Dolmage, 2017). Additionally, students can learn about models of disability: medical, sociopolitical, functional, religious, moral, and biopsychosocial (Engel, 1977; Shakespeare, 2006; Smart, 2015). Students must also understand the concept of intersectionality, which examines how disability interacts with race, gender, sexuality, and socioeconomic status (Erevelles & Minear, 2010; Garland-Thompson, 2005).
Ethics and Multicultural Competence
Students should understand the intersection of disability and ethics by being able to apply the ACA Code of Ethics to disability issues (Chapin et al., 2018; Feather & Carlson, 2019). In either an ethics class or a multicultural class, students must learn about crucial disability-related legislation, such as the Rehabilitation Act of 1973, the Americans with Disabilities Act, the Individuals with Disabilities Education Act, and the Workforce Innovation and Opportunity Act. In the multicultural class, students need to understand disability cultural competence and receive training on disability as a cultural identity and recognizing ableism as a form of oppression (Feldner et al., 2022; Smith et al., 2011). Additionally, in the multicultural class, students should be taught about biases and microaggressions, as well as how to identify and address ableist language and behavior.
Counseling Skills and Practice
In a counseling skills class, students must learn accessible counseling techniques, such as modifying approaches for different abilities (e.g., sensory, cognitive, mobility). Students should also be presented with case studies involving disabled clients, with an emphasis on strengths-based and person-centered approaches. Additionally, students ought to receive supervision and advocacy training on how to support and advocate for clients with disabilities in clinical settings. Counselor educators can use the strategies listed here in the classroom and in practice.
Directions for Future Research
Two of the three authors of this article are disabled and bring lived experience to their teaching, writing, research, and engagement with the nondisabled world. This real-world experience informs the strategies presented and has been applied in both classroom and professional settings. However, these approaches have not yet been empirically tested through formal research. Future research could focus on empirically validating these strategies through qualitative or quantitative studies, particularly in evaluating confidence when working with disabled clients before and after implementing these strategies. Strategies include incorporating disability knowledge into the counselor education curriculum coursework (Hill & Delgado, 2023), using critical pedagogy and disability justice frameworks when teaching (Dolmage, 2017; Erevelles & Minear, 2010), providing experiential learning and opportunities for contact with disabled individuals (Smith et al., 2011), giving disability-related education and training for faculty and supervisors (Feldner et al., 2022), and encouraging the development of allyship and advocacy skills (Feldner et al., 2022; Goodman et al., 2004). Additional studies are also needed to examine ableism and confidence in teaching anti-ableist concepts and disability-related competencies by counselor educators. Finally, scales or measures to assess ableism, specifically in counselor education, could be created and validated.
Conclusion
These strategies do not aim to be an all-encompassing, definitive, or exhaustive checklist, as there are many ways to dismantle ableism. These strategies are a starting point, a reminder, a point of reflection, or an opportunity to affirm current strategies. Significantly, these strategies extend beyond counseling and are relevant across various educational and professional settings, from K–12 classrooms to higher education, social work, health care, and beyond. Wherever you land, we invite you to continue learning, growing, and committing to change with us. Alice Wong (2020) proclaimed, “There is so much that able-bodied people could learn from the wisdom that often comes with disability. However, space needs to be made. Hands need to reach out. People need to be lifted up” (p. 17). Together, we can extend our hands, challenge systemic barriers, and work to dismantle ableism in counseling settings and across all aspects of society.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
Andrews, E. E., Forber-Pratt, A. J., Mona, L. R., Lund, E. M., Pilarski, C. R., & Balter, R. (2019). #SaytheWord: A disability culture commentary on the erasure of “disability.” Rehabilitation Psychology, 64(2), 111–118. https://doi.org/10.1037/rep0000258
Atkins, K. M., Bell, T., Roy-White, T., & Page, M. (2023). Recognizing ableism and practicing disability humility: Conceptualizing disability across the lifespan. Adultspan Journal, 22(1). https://doi.org/10.33470/2161-0029.1151
Ben-Moshe, L., & Magaña, S. (2014). An introduction to race, gender, and disability: Intersectionality, disability studies, and families of color. Women, Gender, and Families of Color, 2(2), 105–114. https://doi.org/10.5406/womgenfamcol.2.2.0105
Berne, P., Morales, A. L., Langstaff, D., & Invalid, S. (2018). Ten principles of disability justice. Women’s Studies Quarterly, 46(1–2), 227–230. https://doi.org/10.1353/wsq.2018.0003
Black, R. D., Weinberg, L. A., & Brodwin, M. G. (2015). Universal design for learning and instruction: Perspectives of students with disabilities in higher education. Exceptionality Education International, 25(2), 1–26.
Bogart, K. R., & Dunn, D. S. (2019). Ableism special issue introduction. Journal of Social Issues, 75(3), 650–664. https://doi.org/10.1111/josi.12354
Bunbury, S. (2019). Unconscious bias and the medical model: How the social model may hold the key to transformative thinking about disability discrimination. International Journal of Discrimination and the Law, 19(1), 26–47. https://doi.org/10.1177/1358229118820742
Campbell, F. K. (2009). Contours of ableism: The production of disability and abledness. Palgrave Macmillan.
CAST. (2018). Universal design for learning guidelines version 3.0. http://udlguidelines.cast.org
Chapin, M., McCarthy, H., Shaw, L., Bradham-Cousar, M., Chapman, R., Nosek, M., Peterson, S., Yilmaz, Z., & Ysasi, N. (2018). Disability-related counseling competencies. American Rehabilitation Counseling Association. https://www.counseling.org/docs/default-source/competencies/arca-disability-related-counseling-competencies-v51519.pdf?sfvrsn=984f4bd0_1
Charlton, J. I. (1998). Nothing about us without us: Disability oppression and empowerment. California University Press.
Collins, P. H., & Bilge, S. (2020). Intersectionality (2nd ed.). Wiley.
Cook, J. M., Deroche, M. D., & Ong, L. Z. (2024). A qualitative analysis of ableist microaggressions. The Professional Counselor, 14(1), 64–82. https://doi.org/10.15241/jmc.14.1.64
Council for the Accreditation of Counseling and Related Educational Programs. (2023). 2024 CACREP standards. https://www.cacrep.org/wp-content/uploads/2024/04/2024-Standards-Combined-Version-4.11.2024.pdf
Crenshaw, K. (1989). Demarginalizing the intersection of race and sex: A Black feminist critique of antidiscrimination doctrine, feminist theory and antiracist politics. University of Chicago Legal Forum, 1989(1), 139–167. https://chicagounbound.uchicago.edu/cgi/viewcontent.cgi?article=1052&context=uclf
Davis, L. J. (2011, September 25). Why is disability missing from the discourse on diversity? The Chronicle of Higher Education, 25, 38–40. https://www.chronicle.com/article/why-is-disability-missing-from-the-discourse-on-diversity
Deroche, M. D., Herlihy, B., & Lyons, M. L. (2020). Counselor trainee self-perceived disability competence: Implications for training. Counselor Education and Supervision, 59(3), 187–199. https://doi.org/10.1002/ceas.12183
Dollarhide, C. T., Rogols, J. T., Garcia, G. L., Ismail, B. I., Langenfeld, M., Walker, T. L., Wolfe, T., George, K., McCord, L., & Aras, Y. (2020). Professional development in social justice: Analysis of American Counseling Association conference programming. Journal of Counseling & Development, 98(1), 41–52. https://doi.org/10.1002/jcad.12298
Dolmage, J. T. (2017). Academic ableism: Disability and higher education. University of Michigan Press. https://doi.org/10.3998/mpub.9708722
Elflein, J. (2024, November 19). Topic: Disability in the U.S. – Statistics & facts. Statista. https://www.statista.com/topics/4380/disability-in-the-us
Engel, G. L. (1977). The need for a new medical model: A challenge for biomedicine. Science, 196(4286), 129–136. https://doi.org/10.1126/science.847460
Erevelles, N., & Minear, A. (2010). Unspeakable offenses: Untangling race and disability in discourses of intersectionality. Journal of Literary & Cultural Disability Studies, 4(2), 127–145. https://doi.org/10.3828/jlcds.2010.11
Feather, K. A., & Carlson, R. G. (2019). An initial investigation of individual instructors’ self-perceived competence and incorporation of disability content into CACREP-accredited programs: Rethinking training in counselor education. Journal of Multicultural Counseling and Development, 47(1), 19–36.
https://doi.org/10.1002/jmcd.12118
Feldner, H. A., Evans, H. D., Chamblin, K., Ellis, L. M., Harniss, M. K., Lee, D., & Woiak, J. (2022). Infusing disability equity within rehabilitation education and practice: A qualitative study of lived experiences of ableism, allyship, and healthcare partnership. Frontiers in Rehabilitation Sciences, 3, 947592.
https://doi.org/10.1080/09638288.2022.9397845
Fornauf, B. S., & Erickson, J. D. (2020). Toward an inclusive pedagogy through universal design for learning in higher education: A review of the literature. Journal of Postsecondary Education and Disability, 33(2), 183–199. https://files.eric.ed.gov/fulltext/EJ1273677.pdf
Frederick, A., & Shifrer, D. (2018). Race and disability: From analogy to intersectionality. Sociology of Race and Ethnicity, 5(2), 200–214. https://doi.org/10.1177/2332649218783480
Friedman, C. (2023). Explicit and implicit: Ableism of disability professionals. Disability and Health Journal, 16(4), 101482. https://doi.org/10.1016/j.dhjo.2023.101482
Friedman, C., & Owen, A. L. (2017). Defining disability: Understandings of and attitudes towards ableism and disability. Disability Studies Quarterly, 37(1).
Garland-Thomson, R. (2005). Feminist disability studies. Signs: Journal of Women in Culture and Society, 30(2), 1557–1587. https://doi.org/10.1086/423352
Goodman, L. A., Liang, B., Helms, J. E., Latta, R. E., Sparks, E., & Weintraub, S. R. (2004). Training counseling psychologists as social justice agents: Feminist and multicultural principles in action. The Counseling Psychologist, 32(6), 793–836. https://doi.org/10.1177/0011000004268802
Grzanka, P. R. (2020). From buzzword to critical psychology: An invitation to take intersectionality seriously. Women & Therapy, 43(3–4), 244–261. https://doi.org/10.1080/02703149.2020.1729473
Hennessey, M. L., & Koch, L. (2007). Universal design for instruction in rehabilitation counselor education. Rehabilitation Research, Policy, and Education, 21(3), 187–194. https://doi.org/10.1891/088970107805059689
Herbert, J. T. (2000). Simulation as a learning method to facilitate disability awareness. Journal of Experiential Education, 23(1), 5–11. https://doi.org/10.1177/105382590002300102
Hill, J. C., & Delgado, H. (2023). Incorporating disability knowledge and content into the counselor education curriculum. ACES Teaching Practice Briefs, 21(2), 18–31. https://www.researchgate.net/publication/388758290_Incorporating_Disability_Knowledge_and_Content_into_the_Counselor_Education_Curriculum
Leonardi, M., Bickenbach, J., Ustun, T. B., Kostanjsek, N., & Chatterji, S. (2006). The definition of disability: What is in a name? The Lancet, 368(9543), 1219–1221. https://doi.org/10.1016/S0140-6736(06)69498-1
Lewis, T. A. (2022, January 1). Working definition of ableism—January 2022 update. https://www.talilalewis.com/blog/working-definition-of-ableism-january-2022-update
Lewis, T. A., & Brown, L. X. Z. (2018). Accountable reporting on disability, race & police violence: A community response to the “Ruderman Foundation paper on the media coverage of use of force and disability.” https://www.talilalewis.com/blog/archives/06-2018
Lund, E. M. (2022). Valuing the insider-professional perspective of disability: A call for rehabilitation psychologists to support disabled psychologists and trainees across the profession. Rehabilitation Psychology, 67(4), 582–586. https://doi.org/10.1037/rep0000452
Mingus, M. (2010, February 12). Changing the framework: Disability justice. Leaving Evidence. https://leavingevidence.wordpress.com/2011/02/12/changing-the-framework-disability-justice
Moradi, B., & Grzanka, P. R. (2017). Using intersectionality responsibly: Toward critical epistemology, structural analysis, and social justice activism. Journal of Counseling Psychology, 64(5), 500–513. https://doi.org/10.1037/cou0000203
Mosher, D. K., Hook, J. N., Captari, L. E., Davis, D. E., DeBlaere, C., & Owen, J. (2017). Cultural humility: A therapeutic framework for engaging diverse clients. Practice Innovations, 2(4), 221–233. https://doi.org/10.1037/pri0000055
Mueller, C. O., Forber-Pratt, A. J., & Sriken, J. (2019). Disability: Missing from the conversation of violence. Journal of Social Issues, 75(3), 707–725. https://doi.org/10.1111/josi.12339
Öksüz, E., & Brubaker, M. D. (2020). Deconstructing disability training in counseling: A critical examination and call to the profession. Journal of Counselor Leadership and Advocacy, 7(2), 163–175. https://doi.org/10.1080/2326716X.2020.1820407
Olkin, R. (2002). Could you hold the door for me? Including disability in diversity. Cultural Diversity and Ethnic Minority Psychology, 8(2), 130–137. https://doi.org/10.1037/1099-9809.8.2.130
Oswald, G. R., Adams, R. D. N., & Hiles, J. A. (2018). Universal design for learning in rehabilitation education: Meeting the needs for equal access to electronic course resources and online learning. Journal of Applied Rehabilitation Counseling, 49(1), 19–22.
Perrin, P. B. (2019). Diversity and social justice in disability: The heart and soul of rehabilitation psychology. Rehabilitation Psychology, 64(2), 105–110. https://doi.org/10.1037/rep0000278
Pierce, K. L. (2024). Bridging the gap between intentions and impact: Understanding disability culture to support disability justice. The Professional Counselor, 13(4), 486–495. https://doi.org/10.15241/klp.13.4.486
Rivas, M. (2020). Disability in counselor education: Perspectives from the United States. International Journal for the Advancement of Counselling, 42, 366–381. https://doi.org/10.1007/s10447-020-09404-y
Shakespeare, T. (2006). The social model of disability. In L. J. Davis (Ed.), The Disability Studies Reader (2nd ed.; pp. 197–204). Routledge. https://disabilitystudies.nl/sites/default/files/beeld/onderwijs/lennard_davis_the_disability_studies_reader_secbookzz-org_0.pdf
Shakespeare, T., & Kleine, I. (2013). Educating health professionals about disability: A review of interventions. Health and Social Care Education, 2(2), 20–37. https://doi.org/10.11120/hsce.2013.00026
Shapiro, J. P. (1994). No pity: People with disabilities forging a new civil rights movement. Three Rivers Press.
Sharif, A., McCall, A. L., & Bolante, K. R. (2022). Should I say “disabled people” or “people with disabilities”? Language preferences of disabled people between identity- and person-first language. ASSETS ’22: Proceedings of the 24th International ACM SIGACCESS Conference on Computers and Accessibility, 1–18. https://doi.org/10.1145/3517428.3544813
Shin, R. Q., Welch, J. C., Kaya, A. E., Yeung, J. G., Obana, C., Sharma, R., Vernay, C. N., & Yee, S. (2017). The intersectionality framework and identity intersections in the Journal of Counseling Psychology and The Counseling Psychologist: A content analysis. Journal of Counseling Psychology, 64(5), 458–474. https://doi.org/10.1037/cou0000204
Slesaransky-Poe, G., & García, A. M. (2014). The social construction of difference. In D. Lawrence-Brown, M. Shapon-Shevin, & N. Erevelles (Eds.), Condition critical: Key principles for equitable and inclusive education (pp. 66–85). Teachers College, New York.
Smart, J. (2015). Disability, society, and the individual (3rd ed.). ProEd, Inc.
Smith, W. T., Roth, J. J., Okoro, O., Kimberlin, C., & Odedina, F. T. (2011). Disability in cultural competency pharmacy education. American Journal of Pharmaceutical Education, 75(2), 26. https://doi.org/10.5688/ajpe75226
Taboas, A., Doepke, K., & Zimmerman, C. (2023). Preferences for identity-first versus person-first language in a US sample of autism stakeholders. Autism, 27(2), 565–570. https://doi.org/10.1177/13623613221130845
Strike, D. L., Skovholt, T. M., & Hummel, T. J. (2004). Mental health professionals’ disability competence: Measuring self-awareness, perceived knowledge, and perceived skills. Rehabilitation Psychology, 49(4), 321–327. https://doi.org/10.1037/0090-5550.49.4.321
Wolbring, G., & Nasir, L. (2024). Intersectionality of disabled people through a disability studies, ability-based studies, and intersectional pedagogy lens: A survey and a scoping review. Societies, 14(9), 176. https://doi.org/10.3390/soc14090176
Wong, A. (Ed.). (2020). Disability visibility: First-person stories from the twenty-first century. Vintage.
Julie C. Hill, PhD, NCC, BC-TMH, LPC, CRC, is an assistant professor at the University of Arkansas. Toni Saia, PhD, CRC, is an associate professor at San Diego State University. Marcus Weathers, Jr., PhD, CRC, LPC-IT, is an assistant professor at Mississippi State University. Correspondence may be addressed to Julie C. Hill, 751 W. Maple St., Fayetteville, AR 72701, jch029@uark.edu.
Sep 13, 2024 | Volume 14 - Issue 2
Sapna B. Chopra, Rebekah Smart, Yuying Tsong, Olga L. Mejía, Eric W. Price
This mixed methods program evaluation study was designed to assist faculty in better understanding students’ multicultural and social justice training experiences, with the goal of improving program curriculum and instruction. It also offers a model for counselor educators to assess student experiences and to make changes that center social justice. A total of 139 first-semester students and advanced practicum students responded to an online survey. The Consensual Qualitative Research-Modified (CQR-M) method was used to analyze brief written narratives. The Multicultural Counseling Competence and Training Survey (MCCTS) and the Advocacy Competencies Self-Assessment Survey (ACSA) were used to triangulate the qualitative data. Qualitative findings revealed student growth in awareness, knowledge, skills, and action, particularly for advanced students, with many students reporting a desire for more social justice instruction. Some students of color reported microaggressions and concerns that training centers White students. Quantitative analyses generally supported the qualitative findings and showed advanced students reporting higher multicultural and advocacy competencies compared to beginning students. Implications for counselor education are discussed.
Keywords: social justice, program evaluation, training, multicultural counseling, counselor education
In the midst of the COVID-19 pandemic and the long-standing inequities it brought to light, many universities began examining the ways that injustice unfolds within their institutions (Mull, 2020). Arredondo et al. (2020) noted that counseling and counselor education continue to uphold white supremacy and center the experiences of White people within theories, training, and research. White supremacy culture promotes Whiteness as the norm and standard, intersects with and reinforces other forms of oppression, and shows up in institutions in both overt and covert ways, such as emphasis on individualism, avoidance of conflict, and prioritizing White comfort (Okun, 2021). Arredondo et al. (2020) called for counselor educators to engage in social justice advocacy and to unpack covert White supremacy in training programs. The present study investigated the multicultural and social justice training experiences of students in a Western United States counseling program so that counseling faculty can be empowered to uncover biases and better integrate social justice in the curriculum.
Counselor education programs are products of the larger sociopolitical environment and dominant patriarchal, cis-heteronormative, Eurocentric culture that often fails to “challenge the hegemonic views that marginalize groups of people” which “perpetuate deficit-based ideologies” (Goodman et al., 2015, p. 148). For example, the focus on the individual in traditional counseling theories can reinforce oppression by failing to address the role of systemic oppression in a client’s distress (Singh et al., 2020). Counseling theory textbooks usually provide an ancillary section at the end of each chapter focusing on multicultural issues (Cross & Reinhardt, 2017). White supremacy culture is so ubiquitous that it is typically invisible to those immersed within it (DiAngelo, 2018). It is not surprising then that counseling is often viewed as a White, middle-class endeavor, and BIPOC (Black, Indigenous, and People of Color) clients frequently perceive that they should leave their cultural identities and experiences outside the counseling session (Turner, 2018). Counselor educators have been encouraged to reflect on how Eurocentric curricula and pedagogy may marginalize students and seek liberatory teaching practices that promote critical consciousness (Sharma & Hipolito-Delgado, 2021).
Students’ Perceptions of Their Growth, Learning Process, and Critiques of Their Training
Studies of mostly White graduate students show gains in expanding awareness of their own biases and privilege, knowledge about other cultures and experiences of oppression, as well as the importance of empowering and advocating for clients (Beer et al., 2012; Collins et al., 2015; Sanabria & DeLorenzi, 2019; Singh et al., 2010). Others indicated the benefits of integrating feminist principles in treatment (Hoover & Morrow, 2016; Singh et al., 2010). Consciousness-raising and self-reflection were key parts of multicultural and social justice learning (Collins et al., 2015; Hoover & Morrow, 2016), and could be emotionally challenging. Indeed, Goodman et al. (2018) identified a theme of internal grappling reflecting students’ experiences of intellectual and emotional struggle; others noted students’ experiences of overwhelm and isolation (Singh et al., 2010), as well as resistance, such as withdrawing or dismissing information that challenged their existing belief system (Seward, 2019). Researchers have also documented student complaints about their social justice training; for example, that social justice is not well integrated or that there was inadequate coverage of skills and action (Collins et al., 2015). Kozan and Blustein (2018) found that even among programs that espouse social justice, there was a lack of training in macro level advocacy skills. Barriers to engaging in advocacy included: lack of time (Field et al., 2019; Singh et al., 2010), emotional exhaustion stemming from observations of the harms caused by systemic inequities (Sanabria & DeLorenzi, 2019), and ill-informed supervisors (Sanabria & DeLorenzi, 2019).
The studies reviewed thus relied on samples of mainly White, cisgender, heterosexual women. Some noted that education on social justice is often centered on helping White students expand their awareness (Haskins & Singh, 2015). In one study focused on challenges faced by students of color, participants expressed frustration with the lack of diversity among their professors, classmates, and curriculum (Seward, 2019). Participants also experienced marginalization and disconnection when professors and students made offensive or culturally uninformed comments and when course content focused on teaching students with privileged identities. Students from marginalized communities also face isolation in academic settings and sometimes question the multicultural competence of their professors (Haskins & Singh, 2015), which in turn contributes to the underrepresentation of students of color in counseling and psychology (Arney et al., 2019).
The Present Study
Counselor educators must critically examine their curriculum, course materials, and overall learning climate for students (Haskins & Singh, 2015). Listening to students’ experiences and perceptions of their training offers faculty an opportunity to model cultural humility, gain useful feedback, and make necessary changes. Given the increased recognition of racial trauma and societal inequities, it is critical that counseling programs engage with students of diverse backgrounds as they seek to shift their pedagogy. Historically, academic institutions have responded to student demands with performative action rather than meaningful change (Zetzer, 2021). This mixed methods study is part of a larger process of counseling faculty working to invite student feedback and question internalized assumptions and biases in order to implement real change. The goal of program evaluation is to investigate strengths and weaknesses in order to improve the program (Royse et al., 2010). According to the 2024 Council for Accreditation of Counseling and Related Educational Programs (CACREP) standards, program evaluation is essential to assess and improve the program (CACREP, 2023). Thus, the purpose of this program evaluation study was to understand students’ self-assessment and experiences with the counseling program’s curriculum in the area of multicultural and social justice advocacy, with the overarching goal of program curriculum and instruction improvement. This article offers counselor educators a model of how to assess program effectiveness in multicultural and social justice teaching and practical suggestions based on the findings. The research questions were: What are beginning and advanced students’ self-perceptions regarding their multicultural and social justice advocacy competencies? What are beginning and advanced students’ perceptions of the multicultural and social justice advocacy competencies training they are receiving in their program?
Method
We employed a mixed method, embedded design in which the quantitative data offered a supportive and secondary role to the qualitative results (Creswell et al., 2003). Qualitative and mixed methods research designs are particularly useful in program evaluation (Royse et al., 2010). Mixed method approaches also offer value in research that centers social justice advocacy, as the integration of diverse methodological techniques within a single study fosters the understanding of multiple perspectives and facilitates a deeper comprehension of intricate issues (Ponterotto et al., 2013). We used an online survey to collect written narratives (qualitative) and survey data (quantitative) from two counseling courses: a beginning counseling course in the first semester (beginning students), and an advanced practicum course, taken by those who had completed at least part of their year-long practicum (advanced students).
Participants
Participants were counseling students enrolled in a CACREP-accredited program at a large West Coast public university in the United States that is both a federally designated Hispanic-serving institution and an Asian American and Native American Pacific Islander–serving institution. Responses were collected from two courses, which included 94 beginning students (84% response rate) and 62 advanced students (71% response rate). Twelve percent of the advanced practicum students also completed the survey when they were first-semester (beginning) students. The mean age of the 139 participants was 27.7 (SD = 7.11), ranging from 20 to 58 years. Racial identifications were 40.3% White, 33.1% Latinx, 14.4% Asian, 7.2% Biracial or Multiracial, 2.9% Black, 0.7% Middle Eastern, 0.7% American Indian/Alaska Native, and 0.7% Native Hawaiian/Pacific Islander. The majority identified as women (82.0%), followed by 14.4% as men, and 2.9% as nonbinary/queer. Students self-identified as heterosexual (71.2%), bisexual (11.5%), lesbian/gay (6.5%), queer (4.3%), pansexual (1.4%), and about 1% each as asexual, heteroflexible, and unsure. About 19.4% of students were enrolled in a bilingual/bicultural (Spanish/Latinx) emphasis within the program.
Procedure
After receiving university IRB approval, graduate students enrolled in the first-semester beginning counseling course (fall 2018 and 2019) or the advanced practicum course (summer 2019 and 2020) were asked to complete an online survey through Qualtrics with both quantitative measures and open-ended questions as part of their preparation for class discussion. Students were informed that this homework would not be graded and was not intended to “test” their knowledge but rather would serve as an opportunity to reflect on their experience of the program’s multicultural and social justice training. Students were also given the option to participate in the current study by giving permission for their answers to be used. Those who consented were asked to continue to complete the demographic questionnaire. In accordance with the American Counseling Association Code of Ethics (2014), students were informed that there would be no repercussions for not participating. A faculty member outside the counseling program managed the collection of and access to the raw data in order to protect the identities of the students and ensure that their participation or lack of participation in the study could not affect their grade for the course or standing in the program. All students, regardless of participation status, were given the option to enter an opportunity drawing for a small cash prize ($20 for data collection in 2018 and 2019, $25 for 2020) through a separate link not connected to their survey responses.
Data Collection
We collected brief written qualitative data and responses to two quantitative measures from both beginning and advanced students.
Qualitative Data
The faculty developed open-ended questions that would elicit student feedback on their multicultural and social justice training. Prior to beginning the counseling program, first-semester students were asked two questions about their experiences and impressions: How would you describe your knowledge about and interest in multiculturalism/diversity and social justice from a personal and/or academic perspective? and How would you describe your initial impressions or experience of the focus on multicultural and social justice in the program so far? They were also asked, if it was relevant, to include their experience in the Latinx counseling emphasis program component. Advanced students, who were seeing clients, were asked the same questions and also asked to: Consider/describe how this experience of multiculturalism and social justice in the program may impact you personally and professionally (particularly in work with clients) in the future.
Quantitative Data
Two instruments were selected to quantitatively assess students’ perceptions of their own multicultural and advocacy competencies. The Multicultural Counseling Competence and Training Survey (MCCTS; Holcomb-McCoy & Myers, 1999) is designed to assess counselors’ perceptions of their multicultural competence and the effectiveness of their training. The survey contains 32 statements for which participants answer on a 4-point Likert scale (not competent, somewhat competent, competent, extremely competent). Sample items include: “I can discuss family therapy from a cultural/ethnic perspective” and “I am able to discuss how my culture has influenced the way I think.” The reliability coefficients for each of the five components of the MCCTS ranged from .66 to .92: Multicultural Knowledge (.92), Multicultural Awareness (.92), Definitions of Terms (.79), Knowledge of Racial Identity Development Theories (.66), and Multicultural Skills (.91; Holcomb-McCoy & Myers, 1999). In this study, the Cronbach’s alpha coefficients ranged from .75 to .96.
The Advocacy Competencies Self-Assessment Survey (ACSA; Ratts & Ford, 2010) assesses for competency and effectiveness across six domains: (a) client/student empowerment, (b) community collaboration, (c) public information, (d) client/student advocacy, (e) systems advocacy, and (f) social/political advocacy. It contains 30 statements that ask participants to respond with “almost always,” “sometimes,” or “almost never.” Sample questions include “I help clients identify external barriers that affect their development” and “I lobby legislators and policy makers to create social change.” Although Ratts and Ford (2010) did not provide psychometrics of the original ACSA, it was validated with mental health counselors (Bvunzawabaya, 2012), suggesting an adequate internal consistency for the overall measure, but not the specific domains. In this study, the Cronbach’s alpha coefficients ranged from .69 to.79 for the six domains, and .94 for the overall scale. For the purposes of this study, we were not interested in specific domains and used the overall scale to assess students’ overall social justice/advocacy competencies.
Data Analysis
Qualitative Data Analysis
To analyze the qualitative data, we used Consensual Qualitative Research-Modified (CQR-M; Spangler et al., 2012), which was based on Hill et al.’s (2005) CQR but modified for larger numbers of participants with briefer responses. In contrast to the in-depth analysis of a small number of interviews, CQR-M was ideal for our data, which consisted of brief written responses from 139 participants. CQR-M involves a consensus process rather than interrater reliability among judges, who discuss and code the narratives, and relies on a bottom-up approach, in which categories
(i.e., themes) are derived directly from the data rather than using a pre-existing thematic structure. Frequencies (i.e., how many participants were represented in each category) are then calculated. We analyzed the beginning and advanced students’ responses separately, as the questions were adjusted for their time spent in the program.
After immersing themselves in the data, the first two authors, Sapna B. Chopra and Rebekah Smart, met to outline a preliminary coding structure, then met repeatedly to revise the coding into more abstract categories and subcategories. The computer program NVivo was used to organize the coding process and determine frequencies. After all data were coded, the fifth author, Eric W. Price, served as auditor and provided feedback on the overall coding structure. Both the consensus process and use of an auditor are helpful in countering biases and preconceptions. Brief quantitative data, as used in this study, can be used effectively as a means of triangulation (Spangler et al., 2012).
Quantitative Data Analysis
To examine for significant differences in the self-perceptions of multicultural competencies and advocacy competencies between White and BIPOC students as well as between beginning and advanced students, a two-way (2×2) ANOVA was conducted with the overall MCCT as the criterion variable and student levels (beginning, advanced) and race (White, BIPOC) as the two independent variables. In addition, two (5×2) multivariate analyses of variances (MANOVAs) were conducted with the five factors of multicultural competencies (knowledge, awareness, definition of terms, racial identity, and skills) as criterion variables and with student levels (beginning, advanced) and student races (White, BIPOC) as independent variables in each analysis. Data for beginning and advanced students were analyzed separately to assess whether time in the counseling program helped to expand their interest and commitment to social justice.
Research Team
We were intentional in examining our own social identities and potential biases throughout the research process. Chopra is a second-generation South Asian American, heterosexual, cisgender woman. Smart is a White European American, heterosexual, cisgender woman. Yuying Tsong identifies as a genderqueer first-generation Taiwanese and Chinese American immigrant. Olga L. Mejía is an Indigenous-identified Mexican immigrant, bisexual, cisgender woman. Price is a White, gay, cisgender male. All have experience as counselor educators and in qualitative research methods, and all have been actively engaged in decolonizing their syllabi and incorporating multicultural and social justice into their pedagogy.
Results
The research process was guided by the overarching question: What are beginning and advanced counseling students’ perceptions of their multicultural and social justice competencies and training and how can their feedback be used to improve their counselor education program? We explore the qualitative findings first, as the primary data for the study, followed by the quantitative data.
Qualitative Findings for Beginning Counseling Students
Two higher-order categories emerged from the beginning students’ narratives: developing competencies and learning process so far.
Developing Competencies
Students’ descriptions of the competencies they were developing included themes of awareness, knowledge, and skills and action. Some students entered the program with an already heightened awareness, while others were making new discoveries. Awareness included subthemes of humility (24.5%), awareness of own privilege (6.4%), and awareness of bias (3.2%). “There’s a lot to learn” was a typical sentiment, particularly from White students. One White female student wrote: “I definitely need more and I believe that open discussions, even hard ones would be some of the best ways to go about this.” A large group expressed knowledge of oppression and systemic inequities (33%); a smaller group referenced intersectionality (3.2%). Within skills and action, some students expressed specific intentions in allyship (11.7%); a number of students expressed commitment to social action but felt unsure how to engage in social justice (11.7%).
Learning Process So Far
Central themes in this category were support for growth, concerns in training, and internal challenges. Some students felt excited and supported, while some were cautiously optimistic or concerned. Support for growth was a strong theme that reflected excited and enthusiastic to learn (22.3%); appreciation for the Latinx emphasis (18.1%); and receiving support from professors and program (17.0%). For example, one Mexican student in the Latinx emphasis who noted that mental health was rarely discussed in her family shared: “For me to see that there is a program that teaches students how to communicate to individuals who are unsure of what counseling is about, gave me a sense of happiness and relief.”
A few students were adopting a wait-and-see attitude and expressed some concerns about their training. Although the percentage for these subthemes is low, they provide an important experience that we want to amplify. This theme had multiple subthemes. The subtheme concerns from students of color included centering White students (3.2%), microaggressions (3.2%), and lack of representation (1.1%). A student who identified as a Mexican immigrant shared experiences of microaggressions, including classmates using a hurtful derogatory phrase referring to immigrants with no comment from the professor until the student raised the issue. Concerns in training also included the subtheme concerns with how material is presented in classes (7.0%). For some, the concern related to the potential for harm in classes in which White and BIPOC students were encouraged to process issues of privilege and oppression. For example, one Asian Pacific Islander student wrote that although they appreciated the emphasis on social justice, “Time always runs out and I believe it’s careless and dangerous to cut off these types of conversations in a rushed manner.” A small minority seemed to suggest a backlash to the emphasis on social justice, stating that the content was presented in ways that were too “politically correct,” “biased,” or “repetitive.”
Multiple subthemes emerged from the theme of internal challenges. Both BIPOC and White students shared feeling afraid to speak up (5.3%). BIPOC students expressed struggling with confidence or wanting to avoid conflict, while White students’ fear of speaking up was also connected to discomfort and uncertainty as a White person (2.1%). A small minority of White students did not express explicit discomfort but seemed to engage in a color-blind strategy, as indicated in the theme of people are people (2.1%): “I find people are people, regardless of any differences, and love hearing the good and bad about everybody’s experiences.” Some students of color expressed limited knowledge about cultures other than one’s own (4.3%). For example, an Asian American student stated that they had gravitated to “those who were most similar to me” growing up. Lastly, a few students shared feeling overwhelmed and exhausted (3.2%).
Qualitative Findings for Advanced Counseling Students
Four higher-order themes emerged: competencies in process, multiculturalism and diversity in the program, social justice in the program, and the learning process.
Competencies in Process
Similar to beginning students, advanced students described growing self-awareness, knowledge and awareness of others, skills, and action. Their disclosures often related to clinical work, now that they had been seeing clients. Self-awareness included strong subthemes of: humility and desire to keep learning (25.8%); increased open-mindedness, acceptance of others, and compassion (22.6%); awareness of personal privilege and oppression (17.7%); awareness of personal bias and value systems (17.7%); and awareness of personal cultural identity (14.5%). One Mexican American student wrote: “I have also gained an increased awareness of how my prejudices can impact my work with clients and learned about how to check-in with myself.”
Knowledge and awareness of others had subthemes of privilege and oppression (19.4%) and increased knowledge of culture (14.5%), with awareness of the potential impact on clients. The advanced students also had more to say about skills, which included subthemes of diversity considerations in conceptualization (29%), and in treatment (12.9%), and cultural conversations in the therapy room (21%). One White student wrote: “I have been able to have difficult conversations that once were unheard of. I have also been able to bring culture, ethnicity, and oppression into the room so that my clients can feel understood and safe.” Within the theme of action, 52% wrote about their commitment to social justice and intention to advocate. Although this strongest subtheme suggested action was still more aspirational than currently enacted, a smaller group also wrote about the experiences that they have already had with client advocacy (12.9%), community and/or political action (12.9%), and unspecified action (11.3%).
Multiculturalism and Diversity in the Program
Many students (44%) indicated that they appreciated that multicultural issues were integrated or addressed well within the program. However, with more time spent in the program, 26% felt that there was more nuance, depth, or scope needed. Some wanted more attention to specific issues, such as disability, gender identity, and religion/spirituality. One Asian American student wrote that the focus had been “basic and surface-level,” adding “I feel like it has also generally catered to the protection of White feelings and voices, which is inherently complicit in the system of White supremacy, especially in higher ed.” Others (9.7%) said more training in clinical application was needed.
Social Justice in the Program
Students expressed a variety of opinions. The largest number (29%) were satisfied that social justice issues were well integrated into the program. Although more students were satisfied than not, many (24%) noted that social justice is addressed but not demonstrated. Similarly, 24% noted minimal attention, specifically that social justice was not addressed much beyond the one course focused on culture, and 24% noted a desire for more opportunities within the program to engage in advocacy. Some suggested requiring social justice work rather than leaving it as an optional activity. Others (13%), mostly from 2020, noted the relevance of current events and sociopolitical climate. One White student shared about a presentation on Black Lives Matter: “This project opened my eyes to my limited knowledge of systemic oppression in the U.S. and impacted me in ways that I will NEVER be the same.” A small number of students (3%) reported that there was no need or room for more training in social justice. One White student wrote that they felt “frustrated” and that the social justice “agenda is so in my face all the time,” adding “sometimes I feel like I am being trained to be an advocate and an activist, which is/are a different job.”
The Learning Process
Three central themes emerged: enrichment experienced, challenges, and suggestions for change. Many students were appreciative of their experience. A strong subtheme within enrichment experienced was professors’ encouragement and modeling (24%). Others commented on how much came from learning from peers (21%). Some shared feeling personally empowered (14.5%). For example, a student who identified as coming from an Asian culture wrote about the hesitancy to be an activist, stating, “There is an underlying belief that our voices will not really ever be heard which is strongly tied to systemic oppression and racism throughout history. Consequently, I appreciate this challenge to grow more in social justice issues.” Others shared ways that the program prompted them to engage in social justice outside the classroom (11.3%). For example, one student wrote: “This program gave me the knowledge and education I needed to make sure that when I did speak out I wasn’t just talking to talk. I would actually have facts, stats, evidence-based research to back up my argument.” A number of students noted the unique benefits of the Latinx program (9.7%). One Mexican American student reflected that they had learned about diversity within Latinx cultures, and that, “As a result, I feel more confident in being able to serve clients from various Latinx cultures or at least know where to obtain relevant information when needed.” Many students expressed a sense of belonging (8.1%).
Challenges. Nearly 10% wrote about struggling to make time [for social justice] and 6.5% noted the emotional impact. For example, one White student wrote: “It was a rude and brutal awakening, to say the least. It was riddled with emotion and heartache but was worth the process.” A few had conflicted or mixed feelings (8.1%)—they felt appreciative but wanted more. A few noted possible harm to marginalized students (6.5%). One Asian American student wrote that faculty should be “calling out microaggressions . . . otherwise, their stance on social justice feels more performative and about protecting their own liability rather than caring for their students of color.” A smaller number (4.8%) struggled with peers and colleagues who seemed uninformed.
Suggestions for Change. Students offered suggestions for improvement, with a strong theme to develop more diverse representation (16.1%), including more representation in faculty, students, case examples, and class discussions. Some comments were specifically about needed attention to Black experiences; one concerned teaching about resiliencies and strengths in the face of oppression. Almost 15% suggested making changes to courses or curriculum. One White student wrote: “If it were me running the program (lol) I would . . . remove the culture class and have all those topics embedded into the fabric of each class because culture and diversity are in all those topics.” A few suggested that faculty require social justice assignments (8.1%), adding that many students will not act unless required. A few also suggested that the program provide more education of White students (8.1%).
Quantitative Findings
Quantitative analyses were conducted to provide triangulation for the qualitative findings and a different view of the data, including possible differences between BIPOC and White students and beginning and advanced students. Table 1 includes descriptive statistics providing an overview of beginning and advanced students’ self-perception of their multicultural and social justice competencies.
Table 1
Descriptive Statistics of Competencies
|
|
|
Multicultural |
Social Justice/Advocacy |
|
|
N |
Mean |
SD |
Mean |
SD |
| White |
Beginning |
35 |
2.58 |
.50 |
62.97 |
24.23 |
| Advanced |
27 |
3.09 |
.38 |
76.07 |
19.11 |
| Total |
62 |
2.80 |
.52 |
68.68 |
22.93 |
| BIPOC |
Beginning |
59 |
2.66 |
.56 |
63.05 |
29.30 |
| Advanced |
35 |
3.01 |
.30 |
77.14 |
20.71 |
| Total |
94 |
2.79 |
.51 |
68.30 |
27.19 |
| Total |
Beginning |
94 |
2.63 |
.54 |
63.02 |
27.39 |
| Advanced |
62 |
3.05 |
.34 |
76.68 |
19.87 |
| Total |
156 |
2.80 |
.51 |
68.45 |
25.51 |
To examine if there were discernable differences between the beginning and advanced students’ perceptions of their competencies, and if there were differences between White and BIPOC students, a two-way (2×2) ANOVA was conducted with the overall MCCT as the criterion variable and student levels (beginning, advanced) and race (White, BIPOC) as the two independent variables. Results indicated that although there were no interaction effects between race and student levels, there were significant differences in overall multicultural competencies between beginning and advanced students, F(1, 152) = 30.54, p < .001, indicating that advanced practicum students reported significantly higher overall multicultural competencies than beginning students. There were no statistically significant differences between White and BIPOC students in their overall multicultural competencies. Two (5×2) MANOVAs were conducted with the five factors of multicultural competencies as criterion variables (knowledge, awareness, definition of terms, racial identity, and skills). Student levels (beginning, advanced) and student race (White, BIPOC) were independent variables. Results indicated that there were significant differences between beginning and advanced students in at least one of the multicultural competencies components, Wilks’ Lambda = .72, F(5, 150) = 11.97, p < .001. More specifically, follow-up univariate ANOVAs indicated that advanced students reported significantly higher multicultural competencies in their knowledge, F(1, 154) = 43.74, p < .001, µ2 = .22; awareness, F(1, 154) = 6.20, p = .014, µ2 = .04; and racial identity, F(1, 154) = 43.17, p < .001, µ2 = .21. However, there were no significant differences in definitions of terms or skills. Even though there were no significant differences between White and BIPOC students in their overall multicultural competencies, the results of the 5×2 MANOVA indicated that there were significant differences in at least one of the components, Wilks’ Lambda = .87, F(5, 150) = 4.49, p = .001. Follow-up univariate ANOVAs indicated that White students reported higher multicultural competencies in racial identity than BIPOC students in this study, F(1, 154) = 4.51, p = .035, µ2 = .03. There were no differences in the other areas.
A two-way (2×2) ANOVA was conducted with the overall ACSA as the criterion variable and student levels (beginning, advanced) and race (White, BIPOC) as the two independent variables. Results indicated that while there were no interaction effects between race and student levels, there were significant differences in overall advocacy competencies between beginning and advanced students, F(1, 152) = 10.78, p = .001, indicating that advanced students reported significantly higher overall advocacy competencies (M = 76.68) than beginning students (M = 63.02). There were no statistically significant differences between White and BIPOC students in their overall advocacy competencies.
Discussion
This study was designed to examine students’ experiences of their multicultural and social justice training as an aspect of program evaluation, specifically to assist faculty in improving curriculum and instruction with regard to multicultural and advocacy competencies; the study also offers a unique contribution to existing literature by including a more racially diverse (60% BIPOC) sample. Students reported growth in the core areas of multicultural and social justice competency as outlined by Ratts et al. (2016): awareness, knowledge, skills, and action. Consistent with Field et al.’s (2019) findings, students reported more growth in awareness and knowledge than in social justice action, with some differences as students moved through the program. Although beginning students identified personal biases, the theme of self-awareness was more complex for them later in the program. This suggests that a longer time spent in the program contributed to personal growth; although this seems expected, these outcomes have not necessarily been examined before and confirm that the programs’ increasing effort on multiculturalism and social justice are showing gains. The advanced students wrote about clinical application as well and made overt statements of their commitment to social justice. The quantitative results supported these qualitative findings, with advanced students reporting higher multicultural competencies in knowledge, awareness, and racial identity and higher overall advocacy competencies compared to beginning students. With one exception, there were no significant differences between White and BIPOC students in their self-assessment of multicultural or advocacy competencies. Across racial groups, students expressed humility and desire to learn more.
Although students expressed mixed opinions about their experience of the multicultural and social justice training, a greater number of advanced students reported that they thought multicultural (44%) and social justice issues (30%) were well integrated into the program compared to the number of students with critiques. Students reported that support from faculty and peers facilitated their growth and learning, consistent with previous research (e.g., Beer et al., 2012; Keum & Miller, 2020). Some students noted a sense of belonging, particularly those in the Latinx emphasis.
Similar to other researchers, we found that many students wanted social justice issues to be integrated across the curriculum rather than into one course (Beer et al., 2012; Collins et al., 2015); they also wanted more focus on skills and action (Collins et al., 2015; Kozan & Blustein, 2018). Students’ scores on the ACSA advocacy competencies scale reflect this gap in training as well. Though fewer students offered critiques of their training, these responses are important to amplify because some of these concerns are rarely solicited or acknowledged. For example, BIPOC students echoed the challenges faced by students in Seward’s (2019) study, including lack of representation in their faculty, classmates, and curriculum as well as feelings of marginalization when microaggressions in the classroom went unchecked and when instruction centered the needs of White students. Additionally, a few advanced students from 2020, during a time of significant racial-sociopolitical uprising in the United States, expressed concern that class discussions potentially caused harm to students from marginalized communities. Though more students expressed a desire for greater in-depth training, a small minority of mostly White students indicated that they did not want more social justice training and would rather focus solely on traditional counseling skills. These different student perspectives point to the challenges of teaching social justice amidst diverse political and ideological backgrounds and the need to increase community and collaboration.
Listening to Student Feedback and Implications for Decolonizing Program Curriculum
This study’s findings support the benefits of listening to students’ voices related to multicultural and social justice to inform counselor educators on program strengths and areas for growth. Although student feedback was not the sole impetus for making program changes, accessing this more detailed response was helpful in refining our purpose and direction, as well as highlighting weaknesses. Perhaps more important was the faculty’s willingness to engage in this self-reflective process and to take necessary actions. Rather than waiting for exit interview feedback from graduating students, counselor educators can conduct ongoing program evaluations through anonymous online surveys as well as town hall meetings that invite students to share their process of learning, perceptions of the cultural climate, and experiences of microaggressions. We have a growing understanding that during such evaluations great care needs to be taken for building safety, so as not to retraumatize students from marginalized communities. Based on the results and a series of Zoom town hall meetings, we have implemented changes, such as more consistent integration of social justice across the curriculum; training and day-long retreats focused on increasing faculty competence; faculty participation in Academics for Black Survival and Wellness, an intensive training led by Dr. Della Mosely and Pearis Bellamy; accountability support groups in social justice work; and decolonizing syllabi and class content (e.g., including BIPOC voices and non–APA-style writing assignments). Faculty have also made significant modifications to course materials. For example, beginning students complete weekly modules that include readings and exercises from The Racial Healing Handbook (Singh, 2019), and students study Liberation Psychology during the first week of theories class so they can consider ways to decolonize more traditional models throughout the semester. These strategies have been helpful in preparing students for more difficult conversations surrounding anti-racism in more advanced courses throughout the program. Forming faculty accountability partners or small groups is helpful so that faculty can support each other as a part of their ongoing development in addressing internalized White supremacy and avoiding harm to students.
Student feedback also called attention to the need for self-care, which our program continues to explore. Consistent with previous research (Collins et al., 2015; L. A. Goodman et al., 2018; Hoover & Morrow, 2016; Singh et al., 2010), students reported that their multicultural and social justice learning was often accompanied by moments of overwhelm, hopelessness, and despair. Without tools to manage these emotions, some students may retreat into defensiveness and withdrawal (Seward, 2019), and some may experience activist burnout (Gorski, 2019). Sustainability is necessary for effective social change efforts (Toporek & Ahluwalia, 2021). Counseling programs can offer resources and guidance for students to practice self-care with counselor educators modeling self-care behavior. For example, the Psychology of Radical Healing Collective (Chen et al., 2019) offered strategies to practice radical self-care, including making space for one’s own healing, finding joy and a sense of belonging, and engaging in advocacy at the local community level. Mindfulness practices can be integrated into social justice education to help students and counselor educators manage difficult emotions, increase their ability to be present, and strengthen compassion and curiosity (Berila, 2016). In addition to individual self-care practices, counselor educators can advocate for community care by tending to the community’s needs and drawing on collective experience and wisdom (Gorski, 2019).
The findings point to the need for counselor educators to better address Whiteness and White supremacy, as well as to center the experiences of students from marginalized communities. Counselor educators may be able to mobilize and direct White students’ feelings of guilt into racial consciousness and action by helping them explore Whiteness, White privilege, and what it means to them while allowing and confronting feelings that arise (Grzanka et al., 2019). It may be helpful for educators to read and assign books on White fragility and ways to address it (DiAngelo, 2018; Helms, 2020; Saad, 2020), so that they can assist White students in managing these emotions. It is important that educators explicitly name and recognize White supremacy as it shows up in counseling theory and practice, and to include a shift from the primary focus on the individual to understanding and dismantling oppressive systems. Counselor educators must also attend to the ways in which they center the comfort of White students over the needs of BIPOC students, so that they do not perpetuate harm and trauma (Galán et al., 2021). Although students with privileged identities may learn powerful lessons about oppression from their classmates, it is important that such learning does not occur at the expense of students with marginalized identities. Offering spaces for White students, especially those who are new to conversations about race and racism, to process their feelings may be helpful to avoid harm to BIPOC students who have experienced racial trauma. Similarly, BIPOC students may benefit from spaces in which they can talk freely and support each other as they unpack their own experiences of microaggressions and trauma (Galán et al., 2021).
Based on the finding that support from faculty was important in facilitating student growth and learning, counselor educators may benefit from implementing strategies informed by relational pedagogy and relational–cultural theory (Dorn-Medeiros et al., 2020). Relational pedagogy centers the relationship between teachers and students and posits that all learning takes place in relationships. Relational–cultural theory emphasizes mutual empathy and empowerment and is rooted in feminist multicultural principles. Practices grounded in these approaches include professors’ use of self-disclosure to model openness, vulnerability, and self-reflection; and their work to reduce power imbalances and invite student feedback at multiple points in time through anonymous surveys and one-on-one meetings. Counselor educators can uplift students as the experts of their experience (Sharma & Hipolito-Delgado, 2021).
Limitations and Future Research
The results of this study must be considered in light of a number of limitations. The use of the online survey meant that we were not able to follow up with students for further discussion or clarification of their responses. Adding focus groups or interviews to this methodology would likely provide a more thorough picture. In spite of assurances to the contrary, some students may have been hesitant to be honest out of concern that their own professors would be reading their feedback. It is possible that different themes would have emerged if all students had participated. In addition, 12% of the advanced students had participated as beginning students and therefore were previously exposed to the survey materials. Although this could have impacted their later responses, we suspect that given the nearly 2-year time lapse this may not have been meaningful. Nevertheless, future research and program evaluation would be strengthened with longitudinal analyses. Lastly, the reliability for the ACSA was relatively low, so conclusions are tentative; however, the results support the qualitative data. Despite these limitations, this study offers a model for assessing students’ learning and experiences with the goal of program improvement. The process of counselor educators humbling themselves and inviting and integrating student feedback is an important step in decolonizing counselor education and better serving students and the clients and communities that they will serve.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
American Counseling Association. (2014). ACA code of ethics. https://www.counseling.org/docs/default-source/default-document-library/ethics/2014-aca-code-of-ethics.pdf?sfvrsn=55ab73d0_1
Arney, E. N., Lee, S. Y., Printz, D. M. B., Stewart, C. E., & Shuttleworth, S. P. (2019). Strategies for increased racial diversity and inclusion in graduate psychology programs. In M. T. Williams, D. C. Rosen, & J. W. Kanter (Eds.), Eliminating race-based mental health disparities: Promoting equity and culturally responsive care across settings (pp. 227–242). Context Press.
Arredondo, P., D’Andrea, M., & Lee, C. (2020). Unmasking White supremacy and racism in the counseling profession. Counseling Today. https://ctarchive.counseling.org/2020/09/unmasking-white-supremacy-and-racism-in-the-counseling-profession
Beer, A. M., Spanierman, L. B., Greene, J. C., & Todd, N. R. (2012). Counseling psychology trainees’ perceptions of training and commitments to social justice. Journal of Counseling Psychology, 59(1), 120–133. https://doi.org/10.1037/a0026325
Berila, B. (2016). Integrating mindfulness into anti-oppression pedagogy: Social justice in higher education. Routledge.
Bvunzawabaya, B. (2012). Social justice counseling: Establishing psychometric properties for the Advocacy Competencies Self-Assessment Survey (Doctoral dissertation, Auburn University). https://etd.auburn.edu/handle/10415/3369
Chen, G. A., Neville, H. A., Lewis, J. A., Adames, H. Y., Chavez-Dueñas, N. Y., Mosley, D. V., & French, B. H. (2019). Radical self-care in the face of mounting racial stress: Cultivating hope through acts of affirmation. Psychology Today. https://www.psychologytoday.com/us/blog/healing-through-social-justice/201911/radical-self-care-in-the-face-mounting-racial-stress
Collins, S., Arthur, N., Brown, C., & Kennedy, B. (2015). Student perspectives: Graduate education facilitation of multicultural counseling and social justice competency. Training and Education in Professional Psychology, 9(2), 153–160. https://doi.org/10.1037/tep0000070
Council for the Accreditation of Counseling and Related Educational Programs. (2023). 2024 CACREP standards.
https://www.cacrep.org/wp-content/uploads/2023/06/2024-Standards-Combined-Version-6.27.23.pdf
Creswell, J. W., Plano Clark, V. L., Gutmann, M. L., & Hanson, W. E. (2003). Advanced mixed methods research designs. In A. Tashakkori & C. Teddlie (Eds.), SAGE handbook of mixed methods in social and behavioral research (1st ed.; pp. 209–240). SAGE.
Cross, W. E., Jr., & Reinhardt, J. S. (2017). Whiteness and serendipity. The Counseling Psychologist, 45(5), 697–705. https://doi.org/10.1177/0011000017719551
DiAngelo, R. (2018). White fragility: Why it’s so hard for White people to talk about racism. Beacon Press.
Dorn-Medeiros, C. M., Christensen, J. K., Lértora, I. M., & Croffie, A. L. (2020). Relational strategies for teaching multicultural courses in counselor education. Journal of Multicultural Counseling and Development, 48(3), 149–160. https://doi.org/10.1002/jmcd.12174
Field, T. A., Ghoston, M. R., Grimes, T. O., Sturm, D. C., Kaur, M., Aninditya, A., & Toomey, M. (2019). Trainee counselor development of social justice counseling competencies. Journal for Social Action in Counseling and Psychology, 11(1), 33–50. https://doi.org/10.33043/JSACP.11.1.33-50
Galán, C. A., Bekele, B., Boness, C., Bowdring, M., Call, C., Hails, K., McPhee, J., Mendes, S. H., Moses, J., Northrup, J., Rupert, P., Savell, S., Sequeira, S., Tervo-Clemmens, B., Tung, I., Vanwoerden, S., Womack, S., & Yilmaz, B. (2021). Editorial: A call to action for an antiracist clinical science. Journal of Clinical Child and Adolescent Psychology, 50(1), 12–57. https://doi.org/10.1080/15374416.2020.1860066
Goodman, L. A., Wilson, J. M., Helms, J. E., Greenstein, N., & Medzhitova, J. (2018). Becoming an advocate: Processes and outcomes of a relationship-centered advocacy training model. The Counseling Psychologist, 46(2), 122–153. https://doi.org/10.1177/0011000018757168
Goodman, R. D., Williams, J. M., Chung, R. C.-Y., Talleyrand, R. M., Douglass, A. M., McMahon, H. G., & Bemak, F. (2015). Decolonizing traditional pedagogies and practices in counseling and psychology education: A move towards social justice and action. In R. D. Goodman & P. C. Gorski (Eds.), Decolonizing “multicultural” counseling through social justice (pp. 147–164). Springer.
Gorski, P. C. (2019). Fighting racism, battling burnout: Causes of activist burnout in US racial justice activists. Ethnic and Racial Studies, 42(5), 667–687. https://doi.org/10.1080/01419870.2018.1439981
Grzanka, P. R., Gonzalez, K. A., & Spanierman, L. B. (2019). White supremacy and counseling psychology: A critical–conceptual framework. The Counseling Psychologist, 47(4), 478–529. https://doi.org/10.1177/0011000019880843
Haskins, N. H., & Singh, A. (2015). Critical race theory and counselor education pedagogy: Creating equitable training. Counselor Education and Supervision, 54(4), 288–301. https://doi.org/10.1002/ceas.12027
Helms, J. E. (2020). A race is a nice thing to have: A guide to being a White person or understanding the White persons in your life (3rd ed.). Cognella.
Hill, C. E., Knox, S., Thompson, B. J., Williams, E. N., Hess, S. A., & Ladany, N. (2005). Consensual qualitative research: An update. Journal of Counseling Psychology, 52(2), 196–205. https://doi.org/10.1037/0022-0167.52.2.196
Holcomb-McCoy, C. C., & Myers, J. E. (1999). Multicultural competence and counselor training: A national survey. Journal of Counseling & Development, 77(3), 294–302. https://doi.org/10.1002/j.1556-6676.1999.tb02452.x
Hoover, S. M., & Morrow, S. L. (2016). A qualitative study of feminist multicultural trainees’ social justice development. Journal of Counseling & Development, 94(3), 306–318. https://doi.org/10.1002/jcad.12087
Keum, B. T., & Miller, M. J. (2020). Social justice interdependence among students in counseling psychology training programs: Group actor-partner interdependence model of social justice attitudes, training program norms, advocacy intentions, and peer relationships. Journal of Counseling Psychology, 67(2), 141–155. https://doi.org/10.1037/cou0000390
Kozan, S., & Blustein, D. L. (2018). Implementing social change: A qualitative analysis of counseling psychologists’ engagement in advocacy. The Counseling Psychologist, 46(2), 154–189. https://doi.org/10.1177/0011000018756882
Mull, R. C. (2020). Colleges are in for a racial reckoning. The Chronicle of Higher Education. https://www.chronicle.com/article/colleges-are-in-for-a-racial-reckoning
Okun, T. (2021). White supremacy culture – Still here. https://drive.google.com/file/d/1XR_7M_9qa64zZ00_JyFVTAjmjVU-uSz8/view
Ponterotto, J. G., Mathew, J. T., & Raughley, B. (2013). The value of mixed methods designs to social justice research in counseling and psychology. Journal for Social Action in Counseling and Psychology, 5(2), 42–68. https://doi.org/10.33043/JSACP.5.2.42-68
Ratts, M. J., & Ford, A. (2010). Advocacy Competencies Self-Assessment (ACSA) Survey©: A tool for measuring advocacy competence. In M. J. Ratts, R. L. Toporek, & J. A. Lewis (Eds.), ACA advocacy competencies: A social justice framework for counselors (pp. 21–26). American Counseling Association.
Ratts, M. J., Singh, A. A., Nassar-McMillan, S., Butler, S. K., & McCullough, J. R. (2016). Multicultural and social justice counseling competencies: Guidelines for the counseling profession. Journal of Multicultural Counseling and Development, 44(1), 28–48. https://doi.org/10.1002/jmcd.12035
Royse, D., Thyer, B. A., & Padgett, D. K. (2010). Program evaluation: An introduction (5th ed.). Cengage.
Saad, L. F. (2020). Me and White supremacy: Combat racism, change the world, and become a good ancestor. Sourcebooks.
Sanabria, S., & DeLorenzi, L. (2019). Social justice pre-practicum: Enhancing social justice identity through experiential learning. Journal for Social Action in Counseling and Psychology, 11(2), 35–53. https://doi.org/10.33043/JSACP.11.2.35-53
Seward, D. X. (2019). Multicultural training resistances: Critical incidents for students of color. Counselor Education and Supervision, 58(1), 33–48. https://doi.org/10.1002/ceas.12122
Sharma, J., & Hipolito-Delgado, C. P. (2021). Promoting anti-racism and critical consciousness through a critical counseling theories course. Teaching and Supervision in Counseling, 3(2), 15–25. https://doi.org/10.7290/tsc030203
Singh, A. A. (2019). The racial healing handbook: Practical activities to help you challenge privilege, confront systemic racism, and engage in collective healing. New Harbinger.
Singh, A. A., Appling, B., & Trepal, H. (2020). Using the multicultural and social justice counseling competencies to decolonize counseling practice: The important roles of theory, power, and action. Journal of Counseling & Development, 98(3), 261–271. https://doi.org/10.1002/jcad.12321
Singh, A. A., Hofsess, C. D., Boyer, E. M., Kwong, A., Lau, A. S. M., McLain, M., & Haggins, K. L. (2010). Social justice and counseling psychology: Listening to the voices of doctoral trainees. The Counseling Psychologist, 38(6), 766–795. https://doi.org/10.1177/0011000010362559
Spangler, P. T., Liu, J., & Hill, C. E. (2012). Consensual qualitative research for simple qualitative data: An introduction to CQR-M. In C. E. Hill (Ed.), Consensual qualitative research: A practical resource for investigating social science phenomena (pp. 269–283). American Psychological Association.
Toporek, R. L., & Ahluwalia, M. K. (2021). Taking action: Creating social change through strength, solidarity, strategy, and sustainability. Cognella Press.
Turner, D. (2018). “You shall not replace us!” White supremacy, psychotherapy and decolonisation. Journal of Critical Psychology, Counselling and Psychotherapy, 18(1), 1–12. https://cris.brighton.ac.uk/ws/portalfiles/portal/495044/JCPCP+18-1+-+Turner+article.pdf
Zetzer, H. A. (2021). Decolonizing the curriculum in health service psychology. Association of Psychology Training Clinics Bulletin: Practicum Education & Training, 20–22. https://aptc.org/images/File/newsletter/APTC_Bulletin_PET_2021_Spring%20FINAL.pdf
Sapna B. Chopra, PhD, is an associate professor at California State University, Fullerton. Rebekah Smart, PhD, is a professor at California State University, Fullerton. Yuying Tsong, PhD, is a professor and Associate Vice President for Student Academic Support at California State University, Fullerton. Olga L. Mejía, PhD, is a licensed psychologist and an associate professor at California State University, Fullerton. Eric W. Price, PhD, is an associate professor at California State University, Fullerton. Correspondence may be addressed to Sapna B. Chopra, Department of Human Services, California State University, Fullerton, P.O. Box 6868, Fullerton, CA 92834-6868, sapnachopra@fullerton.edu.
Sep 13, 2024 | Volume 14 - Issue 2
Taylor J. Irvine, Adriana C. Labarta
Eating disorders (EDs) are increasingly prevalent and pose significant public health challenges. Yet, deficits exist in counselor education programs regarding ED assessment, conceptualization, and treatment. Consequently, counselors report feeling incompetent and distressed when working with ED clients. We propose a conceptual framework, the 3 Cs of ED Education and Training, to enhance trainee development. The 3 Cs are: (a) cultivating trainee self-awareness through reflexivity and deliberate skill practice, (b) capturing contextual and sociocultural factors with culturally responsive approaches, and (c) collaborating with interdisciplinary ED professionals while strengthening counselor professional identity. Implications for counselor educators include incorporating activities aligned with this framework into curriculum and experiential training in order to facilitate trainee competence in ED assessment and treatment.
Keywords: eating disorders, 3 Cs of ED Education and Training, framework, counselor education, trainee development
Eating disorders (EDs) remain one of the most lethal mental health illnesses, contributing to roughly 3 million deaths globally each year (van Hoeken & Hoek, 2020) and impacting 29 million or 9% of Americans over their lifetime (Deloitte Consumer Report, 2020). In the United States alone, EDs directly result in 10,200 deaths annually, averaging one death every hour (Deloitte Access Economics, 2020). The steady rise of EDs across genders and countries is of increasing concern, with scholars noting in their systematic literature review that rates have doubled from 3.5% in 2000–2006 to 7.8% in 2013–2018 (Galmiche et al., 2019). EDs also exact a significant economic toll in the United States. In the 2018–2019 fiscal year, Streatfeild et al. (2021) found that EDs generated financial costs of nearly $65 billion, averaging about $11,000 per affected individual. Moreover, their study estimated an additional $326.5 billion in non-financial costs due to reduced well-being among those with EDs. Given their associated comorbidities with other mental health illnesses (Ulfvebrand et al., 2015), enduring somatic issues (Galmiche et al., 2019), and facilitation of psychological distress (Kärkkäinen et al., 2018), EDs pose significant public health and economic threats that necessitate further consideration. However, the literature lacks meaningful attention to ED prevention and treatment (van Hoeken & Hoek, 2020), an oversight that needs to be redressed within counselor education (CE) graduate training programs. A failure to examine this clinical issue threatens the maintenance of quality assurance and ethical standards within the profession, enabling short- and long-term client harm.
Challenges and Gaps in ED Education and Training
Given the steady rise in the prevalence of EDs and their associated consequences, counseling trainees must be equipped with comprehensive training in order to effectively conceptualize and treat these complex conditions. However, across the decades, research has illuminated ED education and training deficits, particularly in graduate programs (Biang et al., 2024; Labarta et al., 2023; Levitt, 2006; Thompson-Brenner et al., 2012). For instance, Labarta et al.’s (2023) recent study examined clinician attitudes toward treating EDs, revealing challenges related to the lack of specialized graduate training. Among surveyed respondents, only 25.7% reported that their programs offered a specialized course on EDs, while approximately half of the sample (41.3%) divulged that their program dedicated only 1–5 hours of ED-related instruction throughout the curricula. Furthermore, one participant indicated that ED education is “rarely more than one lecture at the master’s level” (Labarta et al., 2023, p. 21). This is particularly concerning as research shows that trainees are not only very likely to encounter a client battling an ED at some point in their professional career (Levitt, 2006) but are also going to be less prepared and effective in treating such clients without specialized ED training in graduate programs (Biang et al., 2024; Labarta et al., 2023).
As a result of this lack of ED education, scholars have noted negative implications for helping professions, contributing to clinician incompetence, increased burnout, and diminished self-efficacy when working with ED clients (Labarta et al., 2023; Levitt, 2006; Thompson-Brenner et al., 2012). Clinician competence is a necessary vehicle to not only promote individual accountability but to also ensure the integrity of the broader counseling profession. However, holistic competency development is threatened without adequate, targeted ED training, increasing the likelihood that counselors-in-training (CITs) will encounter recurring treatment failures when working with clients struggling with an ED (Williams & Haverkamp, 2010). Williams and Haverkamp (2010) echoed this sentiment, stating that the field risks the occurrence of “iatrogenesis . . . particularly when the practitioner has a poor understanding of EDs, the negative reactions that eating disordered clients can evoke in the clinician are not managed, and/or there are specific types of process and relationship errors made in therapy” (p. 92). For example, although a school counselor may not serve as the primary treatment provider for an adolescent with bulimia nervosa, their understanding of warning signs and symptoms, supportive collaboration with students and families, and knowledge of specialized community referrals are invaluable to the counseling process (Carney & Scott, 2012). As such, counselor educators must assist CITs with developing essential competencies for treating EDs during graduate training programs, ultimately working toward bridging this gap and improving the quality of care.
Addressing the deficit of multicultural research in the field of EDs is of paramount importance, as it directly impacts the practice and education of counselors. Accrediting and professional bodies expect counselor educators to impart multicultural knowledge and skills to CITs, including a focus on diverse cultural and social identities (American Counseling Association [ACA], 2014; Council for the Accreditation of Counseling and Related Educational Programs [CACREP], 2023). Furthermore, Levitt (2006) emphasized that the significant consequences and growing prevalence of EDs across diverse cultural groups necessitate that clinicians “gain exposure to the etiology, manifestation, and treatment of eating disorders within multiple contexts” (p. 95). This assertion underscores the critical need for a more inclusive and culturally competent approach to assessing, treating, and educating about EDs, emphasizing the urgency of addressing the existing gaps in research. Ultimately, the absence of targeted ED research and training, notably conceptualization and assessment strategies, poses ethical concerns for safeguarding clients’ welfare, rendering trainees ill-equipped to address milder presentations of these disorders, let alone complex cases with more severe symptoms, such as heightened suicidality, enduring medical complications, and acute psychological distress (Kärkkäinen et al., 2018).
Research concerning client experiences is also imperative when assessing education and training needs for effective ED treatment. Babb et al. (2022) conducted a meta-synthesis of qualitative research on ED clients’ experiences in ED treatment, illuminating important themes on clinicians’ roles in supporting clients. Several clients reported that some staff perpetuated stereotypes about EDs (e.g., viewing the client as an illness versus a person) and tried to fit clients into specific theoretical frameworks. Clients attributed this lack of awareness and sensitivity to the providers’ lack of specialized training in EDs. Conversely, clients in this study felt empowered when providers were empathic and provided individualized approaches to treatment. These participants noted that “being seen as an individual” facilitated motivation for treatment, with the therapeutic alliance as an essential factor in this process (Babb et al., 2022, p. 1289). These client perspectives provide valuable insights that should inform the development of CE training programs to better prepare CITs for working with individuals with EDs.
Training Recommendations for Counselor Education Programs
Collectively, the findings cited above underscore the importance of comprehensive ED training for counselors to be able to effectively and compassionately serve diverse clients with EDs. However, accessibility to such education and training remains a challenge to both the graduate students and practitioners (Biang et al., 2024; Labarta et al., 2023). Furthermore, despite the efficiency of manualized approaches, Babb et al.’s (2022) study emphasized the need for both flexibility and avoiding a one-size-fits-all approach to ED treatment, particularly given the diversity of clients with EDs, including those from traditionally underrepresented backgrounds (Schaumberg et al., 2017). Clients’ lived experiences corroborate these gaps, reporting instances of stereotyping, rigid adherence to theoretical frameworks, and a lack of empathy stemming from inadequate specialized training (Babb et al., 2022). These findings highlight the pressing need for training strategies that ensure competence and uphold ethical standards within the treatment of EDs, including ongoing education for new practitioners entering the field.
The following section offers competency-based recommendations for CE programs to incorporate into their curricula and experiential training. We propose a conceptual model that we call the 3 Cs of ED Education and Training. The 3 Cs are: (a) cultivating trainee self-awareness, (b) capturing contextual and sociocultural factors, and (c) collaborating with interdisciplinary professionals (see Figure 1). We also provide an overview of recommended activities and associated reflective prompts that can be used in a special topics course on EDs (see Appendix A), as well as suggested adaptations for integration across counseling curricula. By integrating these teaching strategies, CE programs can enhance competency-based education for EDs (Williams & Haverkamp, 2010), which may empower CITs to provide compassionate, empirically supported services to this vulnerable population.
Figure 1
The 3 Cs of ED Education and Training
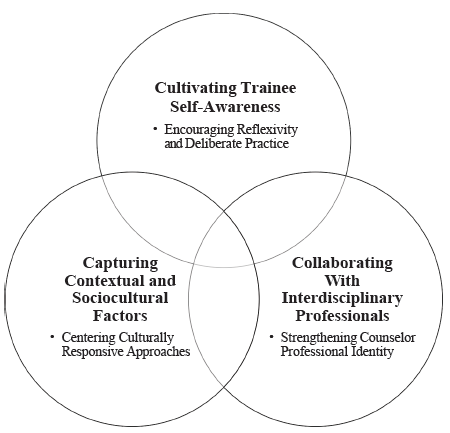
Cultivating Trainee Self-Awareness
Cultivating trainee self-awareness is essential to ethical and multiculturally competent ED treatment. As espoused in our ethical codes (ACA, 2014), counselors are expected to examine their own beliefs, attitudes, and emotional responses when working with clients. Without such conscious examination, clinicians risk projecting their personal biases onto their clients or responding in ways that might inadvertently cause harm. For instance, the pervasive weight stigma embedded in our society can unconsciously influence counselors and may result in microaggressions, victim blaming, or the dismissal of symptoms, particularly when working with clients in larger bodies (Veillette et al., 2018). Counselors may also experience countertransference reactions triggered by ED behaviors or other challenging treatment components, such as high relapse rates, resistance to treatment, or insurance coverage issues (Labarta et al., 2023; Warren et al., 2013), negatively influencing the therapeutic relationship (Graham et al., 2020). Reflexive exercises, paired with targeted deliberate skill practice, are valuable mechanisms for facilitating conscious self-examination and building relevant knowledge and skills for effective ED treatment.
Encouraging Reflexivity and Deliberate Practice
Reflexivity, defined as “a practice of observing and locating one’s self as a knower within certain cultural and socio-historical contexts,” allows CITs to engage with courses on cognitive, affective, and experiential levels (Sinacore et al., 1999, p. 267). The integration of reflexive exercises and critical discussions into ED curricula is essential for cultivating self-awareness and, in effect, mitigating potential client harm. Such practices create opportunities for trainees to identify and address any unconscious biases or beliefs, which, if unaddressed, can undermine the quality of care provided. By establishing a habit of mindful self-inquiry, educators can take the first critical step in preparing ethically conscientious counselors attuned to ED clients’ diverse needs (Labarta et al., 2023).
This intentional practice of reflexivity should be paired with deliberate practice strategies focused specifically on promoting skill development for treating EDs. Deliberate practice is a systematic and intentional training method that targets skill development in order to attain expert performance in a given area or domain (Ericsson, 2006; Irvine et al., 2021). Research shows that integrating deliberate practice strategies early in CE training promotes competency development (Chow et al., 2015). Ericsson (2006) developed five crucial tasks of deliberate practice: self-assessment, skill repetition, formative feedback, stretch goals, and progress monitoring. The first task is a necessary step in increasing trainee self-awareness, which is particularly crucial when working with vulnerable populations, such as those struggling with EDs. Deliberate practice empowers trainees to refine their skills and continuously evolve as competent, empathic, and effective counselors. Thus, deliberate self-reflection on personal assumptions is key, as examining one’s relationship with food and body is imperative to prevent issues like value imposition and orient the focus of treatment to the client’s healing process.
Integrating reflexivity and deliberate skill practice early in CE training is vital to promoting lasting competency. CITs often overestimate their competence at the end of their training, necessitating that CE programs systematically monitor the congruence between CITs’ self-assessments and counselor educators’ assessments of CITs’ competency and skill development (Gonsalvez et al., 2023). Routine reflexive exercises can illuminate areas for growth, while deliberate practice strategies provide structured mechanisms for targeted skill refinement. As trainees embark on their professional journeys, ongoing and intentional efforts to self-reflect and evolve through skill refinement will empower them to provide safe, ethical, and effective ED treatment.
Capturing Contextual and Sociocultural Factors
It has been well-documented that EDs impact individuals across social and cultural identities despite the misconception that only thin, White, affluent, cisgender women are affected (Schaumberg et al., 2017). Indeed, scholars have pointed to the need for intersectional, social justice–informed research that addresses the unique ways that context and culture influence EDs and body image concerns (Burke et al., 2020; Halbeisen et al., 2022). The prevalence of EDs and pervasive body image issues is alarming in today’s sociocultural landscape. For instance, the recent increase in gender-affirming care bans and anti-LGBTQ+ legislation poses profound and detrimental effects on individuals battling an ED (Arcelus et al., 2017), as these restrictive policies exacerbate the mental and emotional distress already experienced by LGBTQ+ individuals, further isolating them and undermining their access to critical health care services (Canady, 2023). As a result, members of this community are more apt to experience intensified body dysphoria, heightening the risk of developing or worsening an ED in an attempt to conform to societal norms (Arcelus et al., 2017).
In the wake of the COVID-19 pandemic, the world has experienced a collective trauma that triggered a series of physical and mental health consequences that will linger for years to come, including rising rates of disordered eating and body-related concerns. Termorshuizen et al. (2020) surveyed 1,021 individuals across the United States and the Netherlands, revealing that ED diagnoses increased at a rate of roughly 60%, with respondents noting increased binge episodes (30%) and restriction behaviors (62%) during this time. Scholars have also shown the deleterious effects of the pandemic on body image perception. For instance, in one study of 7,878 respondents, 61% of surveyed adults and 66% of surveyed children (17 and under) disclosed frequent negative feelings regarding their body image, with 53% of adults and 58% of children reporting that the pandemic has significantly exacerbated these feelings (House of Commons, 2021). Unfortunately, weight stigma was also pervasive in the media, with concerns regarding quarantine weight gain (e.g., “Quarantine-15”) contributing to eating and body image challenges (Schneider et al., 2023). Amidst the multifaceted challenges presented by recent sociopolitical events and the intersecting struggles faced by diverse individuals with EDs, it is essential that counselors implement culturally responsive approaches to treatment and advocacy efforts.
Centering Culturally Responsive Approaches
Given the diversity of clients who struggle with eating and body image concerns (Schaumberg et al., 2017), CE programs must integrate culturally sensitive theories into the curriculum to ensure that CITs possess the necessary competencies to explore relevant cultural factors and effectively treat diverse clients with EDs (Williams & Haverkamp, 2010). Two theories that fostered the development of the Multicultural and Social Justice Counseling Competencies (MSJCC; Ratts et al., 2016) are intersectionality theory and relational–cultural theory (Singh et al., 2020). Intersectionality is a framework for comprehensively understanding the interaction of systemic inequalities and oppression that significantly affect marginalized community members (Burke et al., 2020; Crenshaw, 1991). This theoretical paradigm deepens our understanding of factors such as age, race, ethnicity, sexual orientation, ability status, body size, and gender identity and how these factors influence an individual’s lived experience. Intersectionality is vital for promoting social justice and culturally responsive treatment while also serving as a tool to dismantle oppression and colonizing practices within the profession (Chan et al., 2018; Singh et al., 2020). Intersectionality-informed practice may assist researchers and counselors with considering risk and protective factors for EDs; however, the lack of attention to the intersecting roles and identities of ED clients (e.g., a Catholic, bisexual, Latina) remains a concern, which is crucial for informing culturally competent counseling and training practices (Burke et al., 2020).
Relational–cultural therapy (RCT; Jordan, 2009) is another promising theory that may decolonize dominant counseling approaches (Singh et al., 2020). Due to its emphasis on relational connection, social justice, and empowerment, RCT has been applied to the treatment of EDs (Labarta & Bendit, 2024; Trepal et al., 2015). Infusing RCT into practice may help counselors understand sociocultural influences that maintain ED (e.g., diet culture, weight stigma, acculturation) and perpetuate feelings of disconnection for individuals who do not conform to prevailing body or appearance standards. RCT also aligns well with counseling’s wellness orientation due to its relational and strengths-based focus, emphasizing resilience over pathology in the treatment of ED (Labarta & Bendit, 2024). Counselor educators can expand beyond traditional ED treatment approaches by integrating culturally responsive theories like intersectionality and RCT into course curricula, thus highlighting the intrapersonal, interpersonal, and systemic components that impact clients with EDs.
Collaborating With Interdisciplinary Professionals
The counseling profession has recognized the importance of interdisciplinary practice, encouraging counselors to participate in “decisions that affect the well-being of clients by drawing on the perspectives, values, and experiences of the counseling profession and those of colleagues from other disciplines” (ACA, 2014, Code D.1.c, p. 10). The CACREP Standards (2023) also emphasize the need for counseling students to learn about collaboration, consultation, and community outreach as part of interprofessional teams (Section 3.A.3). Indeed, interdisciplinary collaboration provides an opportunity for individual and systems-level advocacy (Myers et al., 2002). The challenge remains in how counselors can balance establishing a distinct professional identity while simultaneously fostering a sense of community among various helping professions (Klein & Beeson, 2022). Researchers have underscored common experiences of counselors within interdisciplinary teams, including challenges with building legitimacy and credibility, especially among more well-established helping professions such as psychiatry or psychology (Klein & Beeson, 2022; Ng et al., 2023). Given that multidisciplinary collaboration is also crucial to ED treatment (Crone et al., 2023; Williams & Haverkamp, 2010), counselor educators must prepare CITs to effectively work within interdisciplinary treatment teams while utilizing their counseling values and training to best serve their clients and advocate for the inclusion of counselors across ED treatment settings (Labarta et al., 2023).
Strengthening Counselor Professional Identity
Given that EDs are biopsychosocial in nature, effective treatment commonly involves collaboration among various health professions (e.g., medicine, psychiatry, counseling, psychology, dietetics) to ensure holistic, comprehensive client care (Crone et al., 2023). Counselors’ developmental, preventive, and wellness-based perspectives can help provide a strengths-based approach to interdisciplinary collaborations (Labarta et al., 2023). For example, a psychiatrist at a residential facility may focus on assessing a client’s pathology, comorbidity, and changes in symptoms throughout treatment. Although counselors can also focus on assessing client symptoms, their training allows them to provide insight into protective factors that foster client resilience in their recovery process (e.g., social support and cognitive flexibility). Both professionals bring unique expertise, knowledge, and skill sets that provide a distinct conceptualization of the client’s concerns with food or with their body. However, the ultimate goal of the treatment team is to ensure ethical and competent care for the client.
Outside of intensive ED treatment, counselors in school settings and community agencies can offer prevention-based approaches to mitigate risk factors leading to the development of EDs. Prevention-based efforts, such as community programs and workshops, are essential to the field of ED, given the alarmingly low rates of help-seeking in adults with lifetime EDs (34.5% for anorexia nervosa, 62.6% for bulimia nervosa, and 49.0% for binge eating disorder), which are even more pronounced among marginalized communities (Coffino et al., 2019). As such, counselors and other helping professionals can collaborate on ways to increase accessibility to mental health services for underserved groups with increased risk of eating or body image concerns (e.g., LGBTQ+; Nagata et al., 2020). Regardless of the settings within which CITs will work, students can benefit from developing teamwork, leadership, and advocacy skills, as well as a systemic conceptualization of client care (Ng et al., 2023). Ultimately, counselor educators can encourage the exploration of shared goals across helping professions and the utilization of counseling values and training to enhance interdisciplinary work for diverse clients and communities recovering from EDs (Klein & Beeson, 2022; Labarta et al., 2023; Ng et al., 2023).
Implications for Counselor Educators
The 3 Cs for ED Education and Training pose several implications for counselor educators and counseling programs. Although intended for ED treatment, this framework captures essential competencies across counseling specialties, such as counselor self-awareness, cultural and diversity issues, and interdisciplinary practice (CACREP, 2023). As such, integrating these foci into the counseling curriculum can help reinforce competencies regardless of the settings within which students will work. Counselor educators teaching about EDs should also consider ways to incorporate other ED counseling competencies, such as relevant ethical issues, assessment and screening, and evidence-based treatments into coursework (Williams & Haverkamp, 2010). These topics can be integrated into the 3 Cs for ED Education and Training in several ways. For instance, ethical issues and scenarios, such as determining when a client may need a higher level of care, can be presented to students as a standard component of collaborating with interdisciplinary professionals. Counselor educators can also review common ED assessments and encourage students to critically evaluate gaps in the diagnostic process that impact underrepresented populations (e.g., men with EDs), capturing contextual and sociocultural factors and enhancing culturally responsive care (see Appendix B for more examples.)
We also recognize the potential challenges of implementing the 3 Cs of ED Education and Training, as a stand-alone, special topics course on EDs may not be possible for all counseling programs. However, counselor educators can adapt and incorporate the suggested activities in Appendix A into various CACREP core courses to enhance ED education across the curriculum. CE programs can also utilize their Chi Sigma Iota chapters to host events on EDs, such as an interdisciplinary panel discussion followed by a group discussion on professional counseling identity and advocacy (Labarta et al., 2023). Opening these events to the local community could encourage continuing education, collaboration, and advocacy.
Directions for Future Research
Given that the 3 Cs of ED Education and Training is a conceptual framework, there are several directions for future research. Counselor educators and researchers may consider developing a stand-alone course to test the effects of this framework on CITs’ competence in treating EDs. To our knowledge, limited ED competency measures exist, especially for counselors. As such, researchers could explore developing an instrument that measures ED competency areas that include the 3 Cs of ED Education and Training. Such a tool would be helpful for research, clinical, and teaching purposes. An ED competency tool may also enhance CITs’ and counselors’ deliberate practice efforts, promoting quality care for clients across ED treatment settings. Additionally, one theoretical framework educators can modify to help enhance trainees’ clinical competencies in treating EDs is Irvine and colleagues’ (2021) Deliberate Practice Coaching Framework (DPCF), given its structured guidance for skill refinement through individualized coaching and feedback. The development and future testing of an adapted DPCF for EDs may further enhance reflexive and deliberate practice efforts for CITs and counselors working with this population.
Conclusion
In this article, we have proposed our 3 Cs of ED Education and Training to address current gaps in ED education and enhance trainee preparedness across CE programs. Informed by existing literature, this framework incorporates essential elements of comprehensive ED treatment, including counselor self-awareness, cultural and contextual factors, and interdisciplinary practice. The flexibility of this framework allows educators to adapt current curricula to strengthen ED training in CE programs and to meet the needs of their students. Further research that tests a stand-alone course incorporating this framework is needed. The 3 Cs of ED Education and Training offer a path forward in remedying the salient gaps in ED education, ultimately advocating for more compassionate, ethical, and inclusive care across counseling settings.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
American Counseling Association. (2014). ACA code of ethics. https://www.counseling.org/docs/default-source/default-document-library/ethics/2014-aca-code-of-ethics.pdf?sfvrsn=55ab73d0_1
Arcelus, J., Fernández-Aranda, F., & Bouman, W. P. (2017). Eating disorders and disordered eating in the LGBTQ population. In L. K. Anderson, S. B. Murray, & W. H. Kaye (Eds.), Clinical handbook of complex and atypical eating disorders (pp. 327–343). Oxford University Press.
https://doi.org/10.1093/med-psych/9780190630409.003.0019
Babb, C., Jones, C. R. G., & Fox, J. R. E. (2022). Investigating service users’ perspectives of eating disorder services: A meta-synthesis. Clinical Psychology and Psychotherapy, 29(4), 1276–1296. https://doi.org/10.1002/cpp.2723
Biang, A., Merlin-Knoblich, C., & Lim, J. H. (2024). An exploration of counselors of color working in the eating disorder field. Journal of Counseling & Development, 102(4), 482–494. https://doi.org/10.1002/jcad.12532
Burke, N. L., Schaefer, L. M., Hazzard, V. M., & Rodgers, R. F. (2020). Where identities converge: The importance of intersectionality in eating disorders research. International Journal of Eating Disorders, 53(10), 1605–1609. https://doi.org/10.1002/eat.23371
Canady, V. A. (2023). Mounting anti-LGBTQ+ bills impact mental health of youths. Mental Health Weekly, 33(15), 1–6. https://doi.org/10.1002/mhw.33603
Carney, J. M., & Scott, H. L. (2012). Eating issues in schools: Detection, management, and consultation with allied professionals. Journal of Counseling & Development, 90(3), 290–297. https://doi.org/10.1002/j.1556-6676.2012.00037.x
Chan, C. D., Cor, D. N., & Band, M. P. (2018). Privilege and oppression in counselor education: An intersectionality framework. Journal of Multicultural Counseling and Development, 46(1), 58–73. https://doi.org/10.1002/jmcd.12092
Chow, D. L., Miller, S. D., Seidel, J. A., Kane, R. T., Thornton, J. A., & Andrews, W. P. (2015). The role of deliberate practice in the development of highly effective psychotherapists. Psychotherapy, 52(3), 337–345. https://doi.org/10.1037/pst0000015
Coffino, J. A., Udo, T., & Grilo, C. M. (2019). Rates of help-seeking in US adults with lifetime DSM-5 eating disorders: Prevalence across diagnoses and differences by sex and ethnicity/race. Mayo Clinic Proceedings, 94(8), 1415–1426. https://doi.org/10.1016/j.mayocp.2019.02.030
Council for the Accreditation of Counseling and Related Educational Programs. (2023). 2024 CACREP standards. https://www.cacrep.org/for-programs/2024-cacrep-standards
Crandall, C. S. (1994). Prejudice against fat people: Ideology and self-interest. Journal of Personality and Social Psychology, 66(5), 882–894. https://doi.org/10.1037/0022-3514.66.5.882
Crenshaw, K. (1991). Mapping the margins: Intersectionality, identity politics, and violence against women of color. Stanford Law Review, 43(6), 1241–1299. https://doi.org/10.2307/1229039
Crone, C., Fochtmann, L. J., Attia, E., Boland, R., Escobar, J., Fornari, V., Golden, N., Guarda, A., Jackson-Triche, M., Manzo, L., Mascolo, M., Pierce, K., Riddle, M., Seritan, A., Uniacke, B., Zucker, N., Yager, J., Craig, T. J., Hong, S.-H., & Medicus, J. (2023). The American Psychiatric Association practice guideline for the treatment of patients with eating disorders. The American Journal of Psychiatry, 180(2), 167–171. https://doi.org/10.1176/appi.ajp.23180001
Deloitte Access Economics. (2020, June). Social and economic cost of eating disorders in the United States [Infographic]. https://www.hsph.harvard.edu/striped/report-economic-costs-of-eating-disorders
Ericsson, K. A. (2006). The influence of experience and deliberate practice on the development of superior expert performance. In K. A. Ericsson, N. Charness, P. J. Feltovich, & R. R. Hoffman (Eds.), The Cambridge handbook of expertise and expert performance (1st ed., pp. 683–704). Cambridge University Press.
Galmiche, M., Déchelotte, P., Lambert, G., & Tavolacci, M. P. (2019). Prevalence of eating disorders over the 2000–2018 period: A systematic literature review. The American Journal of Clinical Nutrition, 109(5), 1402–1413. https://doi.org/10.1093/ajcn/nqy342
Gonsalvez, C. J., Riebel, T., Nolan, L. J., Pohlman, S., & Bartik, W. (2023). Supervisor versus self-assessment of trainee competence: Differences across developmental stages and competency domains. Journal of Clinical Psychology, 79(12), 2959–2973. https://doi.org/10.1002/jclp.23590
Graham, M. R., Tierney, S., Chisholm, A., & Fox, J. R. E. (2020). The lived experience of working with people with eating disorders: A meta-ethnography. International Journal of Eating Disorders, 53(3), 422–441. https://doi.org/10.1002/eat.23215
Halbeisen, G., Brandt, G., & Paslakis, G. (2022). A plea for diversity in eating disorders research. Frontiers in Psychiatry, 13, 820043. https://doi.org/10.3389/fpsyt.2022.820043
House of Commons Women and Equalities Committee. (2021). Changing the perfect picture: An inquiry into body image. https://committees.parliament.uk/publications/5357/documents/53751/default
Irvine, T., Fullilove, C., Osman, A., Farmanara, L., & Emelianchik-Key, K. (2021). Enhancing clinical competencies in counselor education: The Deliberate Practice and Coaching Framework. Journal of Counselor Preparation and Supervision, 14(4). https://digitalcommons.sacredheart.edu/jcps/vol14/iss4/5
Jordan, J. V. (2009). Relational–cultural therapy. American Psychological Association.
Kärkkäinen, U., Mustelin, L., Raevuori, A., Kaprio, J., & Keski-Rahkonen, A. (2018). Do disordered eating behaviours have long-term health-related consequences? European Eating Disorders Review, 26(1), 22–28. https://doi.org/10.1002/erv.2568
Kerl-McClain, S. B., Dorn-Medeiros, C. M., & McMurray, K. (2022). Addressing anti-fat bias: A crash course for counselors and counselors-in-training. Journal of Counselor Preparation and Supervision, 15(4). https://digitalcommons.sacredheart.edu/jcps/vol15/iss4/3
Klein, J. L., & Beeson, E. T. (2022). An exploration of clinical mental health counselors’ attitudes toward professional identity and interprofessionalism. Journal of Mental Health Counseling, 44(1), 68–81. https://doi.org/10.17744/mehc.44.1.06
Labarta, A. C., & Bendit, A. (2024). Culturally responsive and compassionate eating disorder treatment: Serving marginalized communities with a relational-cultural and self-compassion approach. Journal of Creativity in Mental Health, 19(2), 251–261. https://doi.org/10.1080/15401383.2023.2174629
Labarta, A. C., Irvine, T., & Peluso, P. R. (2023). Exploring clinician attitudes towards treating eating disorders: Bridging counselor training gaps. Journal of Counselor Preparation and Supervision, 17(1). https://digitalcommons.sacredheart.edu/jcps/vol17/iss1/2
Levitt, D. H. (2006). Eating disorders training and counselor preparation: A survey of graduate programs. The Journal of Humanistic Counseling, Education and Development, 45(1), 95–107. https://doi.org/10.1002/j.2161-1939.2006.tb00008.x
Myers, J. E., Sweeney, T. J., & White, V. E. (2002). Advocacy for counseling and counselors: A professional imperative. Journal of Counseling & Development, 80(4), 394–402. https://doi.org/10.1002/j.1556-6678.2002.tb00205.x
Nagata, J. M., Ganson, K. T., & Austin, S. B. (2020). Emerging trends in eating disorders among sexual and gender minorities. Current Opinion in Psychiatry, 33(6), 562–567. https://doi.org/10.1097/YCO.0000000000000645
Ng, K.-M., Harrichand, J. J. S., Litherland, G., Ewe, E., Kayij-Wint, K. D., Maurya, R., & Schulthes, G. (2023). Interdisciplinary collaboration challenges faced by counselors in places where professional counseling is nascent. International Journal for the Advancement of Counselling, 45(1), 155–169.
https://doi.org/10.1007/s10447-022-09492-y
Ratts, M. J., Singh, A. A., Nassar-McMillan, S., Butler, S. K., & McCullough, J. R. (2016). Multicultural and social justice counseling competencies: Guidelines for the counseling profession. Journal of Multicultural Counseling and Development, 44(1), 28–48. https://doi.org/10.1002/jmcd.12035
Schaumberg, K., Welch, E., Breithaupt, L., Hübel, C., Baker, J. H., Munn-Chernoff, M. A., Yilmaz, Z., Ehrlich, S., Mustelin, L., Ghaderi, A., Hardaway, A. J., Bulik-Sullivan, E. C., Hedman, A. M., Jangmo, A., Nilsson, I. A. K., Wiklund, C., Yao, S., Seidel, M., & Bulik, C. M. (2017). The science behind the Academy for Eating Disorders’ nine truths about eating disorders. European Eating Disorders Review, 25(6), 432–450.
https://doi.org/10.1002/erv.2553
Schneider, J., Pegram, G., Gibson, B., Talamonti, D., Tinoco, A., Craddock, N., Matheson, E., & Forshaw, M. (2023). A mixed-studies systematic review of the experiences of body image, disordered eating, and eating disorders during the COVID-19 pandemic. International Journal of Eating Disorders, 56(1), 26–67. https://doi.org/10.1002/eat.23706
Sinacore, A. L., Blaisure, K. R., Justin, M., Healy, P., & Brawer, S. (1999). Promoting reflexivity in the classroom. Teaching of Psychology, 26(4), 267–270. https://doi.org/10.1207/S15328023TOP260405
Singh, A. A., Appling, B., & Trepal, H. (2020). Using the Multicultural and Social Justice Counseling Competencies to decolonize counseling practice: The important roles of theory, power, and action. Journal of Counseling & Development, 98(3), 261–271. https://doi.org/10.1002/jcad.12321
Streatfeild, J., Hickson, J., Austin, S. B., Hutcheson, R., Kandel, J. S., Lampert, J. G., Myers, E. M., Richmond, T. K., Samnaliev, M., Velasquez, K., Weissman, R. S., & Pezzullo, L. (2021). Social and economic cost of eating disorders in the United States: Evidence to inform policy action. International Journal of Eating Disorders, 54(5), 851–868. https://doi.org/10.1002/eat.23486
Termorshuizen, J. D., Watson, H. J., Thornton, L. M., Borg, S., Flatt, R. E., MacDermod, C. M., Harper, L. E., van Furth, E. F., Peat, C. M., & Bulik, C. M. (2020). Early impact of COVID-19 on individuals with eating disorders: A survey of ~1000 individuals in the United States and the Netherlands. International Journal of Eating Disorders, 53(11), 1780–1790. https://doi.org/10.1002/eat.23353
Thompson-Brenner, H., Satir, D. A., Franko, D. L., & Herzog, D. B. (2012). Clinician reactions to patients with eating disorders: A review of the literature. Psychiatric Services, 63(1), 73–78. https://doi.org/10.1176/appi.ps.201100050
Trepal, H., Boie, I., Kress, V., & Hammer, T. (2015). A relational-cultural approach to working with clients with eating disorders. In L. H. Choate (Ed.), Eating disorders and obesity: A counselor’s guide to prevention and treatment (pp. 261–276). https://doi.org/10.1002/9781119221708.ch18
Ulfvebrand, S., Birgegård, A., Norring, C., Högdahl, L., & von Hausswolff-Juhlin, Y. (2015). Psychiatric comorbidity in women and men with eating disorders results from a large clinical database. Psychiatry Research, 230(2), 294–299. https://doi.org/10.1016/j.psychres.2015.09.008
van Hoeken, D., & Hoek, H. W. (2020). Review of the burden of eating disorders: Mortality, disability, costs, quality of life, and family burden. Current Opinion in Psychiatry, 33(6), 521–527. https://doi.org/10.1097/YCO.0000000000000641
Veillette, L. A. S., Serrano, J. M., & Brochu, P. M. (2018). What’s weight got to do with it? Mental health trainees’ perceptions of a client with anorexia nervosa symptoms. Frontiers in Psychology, 9, 2574. https://doi.org/10.3389/fpsyg.2018.02574
Warren, C. S., Schafer, K. J., Crowley, M. E. J., & Olivardia, R. (2013). Demographic and work-related correlates of job burnout in professional eating disorder treatment providers. Psychotherapy, 50(4), 553–564. https://doi.org/10.1037/a0028783
Williams, M., & Haverkamp, B. E. (2010). Identifying critical competencies for psychotherapeutic practice with eating disordered clients: A Delphi study. Eating Disorders, 18(2), 91–109. https://doi.org/10.1080/10640260903585524
Appendix A
The 3 Cs of ED Education and Training: Suggested Activities and Reflective Prompts
| 3 Cs of ED Education & Training |
Suggested
Activities |
Activity Sample
Reflective Prompts |
Adaptations for Integration Across Counseling Curricula |
|
Cultivating Trainee
Self-Awareness |
Reflexive Journaling:
Have CITs maintain a journal, reflecting on their experiences (e.g., biases, assumptions, insights, challenges) throughout the course.
Instructors can provide suggested weekly prompts based on the content or topic area discussed.
Deliberate Practice:
During the first week, CITs will read Williams and Haverkamp’s (2010) article on ED counseling competencies.
CITs then write a reflection paper identifying 2–3 targeted, actionable areas for development and growth.
Revisit these competencies at the end of the course to assess CIT growth and ongoing development areas. |
Reflexive Journaling Prompts:
Reflect on your beliefs, values, and attitudes about counseling ED clients. What would you like to learn? What challenges do you anticipate?
How might cultural factors impact how counselors work with ED clients? Consider how your cultural and social identities shape your relationship with food and body image.
Complete the Anti-fat Attitudes Questionnaire (Crandall, 1994) and interpret your score. What insights did you gain? Why might self-assessment in this domain be an important tool for counselors? (Kerl-McClain et al., 2022)
Deliberate Practice Prompts:
Using a Likert scale of 1 (not confident) to 5 (very confident), how confident do you feel to treat clients with EDs?
Using a Likert scale of 1 (not prepared) to 5 (very prepared), how prepared do you feel to treat clients with EDs?
Identify 2–3 areas of personal or professional development and growth.
Identify 2–3 actionable steps for this semester and beyond.
|
Psychopathology and Diagnosis Courses:
Before teaching ED diagnoses, facilitate a brief activity to promote reflexive practice (see suggested prompts).
Follow up with a class discussion on CITs’ reflections, reactions, insights, and the possible impact of biases or assumptions on the diagnosis and treatment process for ED clients.
Practicum and Internship Courses:
CITs working in ED treatment settings can use the deliberate practice prompts to continually assess strengths and growth areas.
Encourage CITs to complete the self-assessment on ED knowledge and skills. Based on the identified gaps, campus instructors can invite guest lecturers to discuss topics of interest. |
| 3 Cs of ED Education & Training |
Suggested
Activities |
Activity Sample
Reflective Prompts |
Adaptations for Integration Across Counseling Curricula |
|
Capturing Contextual
and
Sociocultural Factors |
Media Critique:
Have CITs select and analyze a form of media (e.g., movies, TV series, social media).
CITs can then consider the messages conveyed about EDs and body image.
Class Discussion:
Engage in a class discussion on CITs’ observations, noted themes, and implications for counseling practice.
Educators may also initiate a discussion on media literacy and how to broach similar discussions with clients and colleagues.
|
Individual Reflection Prompts:
How were EDs and/or body image concerns portrayed explicitly and implicitly?
How do sociocultural factors (e.g., race, ethnicity, gender, etc.) influence media portrayals and messages about EDs/body image?
How might these portrayals or messages influence one’s beliefs about EDs?
Class Discussion Prompts:
What were the overarching themes or messages across the various media?
How can culturally responsive theories (e.g., RCT, intersectionality) inform how we conceptualize the impact of media on EDs and body image concerns?
How can counselors work with clients impacted by harmful media ideals?
How can counselors advocate for more culturally inclusive and responsible ED portrayals in media? |
Social and Cultural Diversity Course:
Facilitate a discussion on CITs’ observations of ED media portrayals, considering the impact of limited representation on mental health access.
Provide a case study of a client with intersecting minoritized identities and encourage CITs to identify culturally responsive treatment approaches and theories that can benefit the client’s recovery. |
| 3 Cs of ED Education & Training |
Suggested
Activities |
Activity Sample
Reflective Prompts |
Adaptations for Integration Across Counseling Curricula |
|
Collaborating with Interdisciplinary Professionals |
ED Expert Panel:
Invite professionals across disciplines specializing in treating EDs (e.g., M.D., psychiatrist, psychologist, dietician).
Engage the panelists in a discussion on their respective training, roles, responsibilities, and experiences working in interdisciplinary treatment teams.
Reserve Q&A time for CITs to share any thoughts, questions, and insights (Labarta et al., 2023).
Professional Identity Reflection Paper:
After the ED expert panel discussion, have CITs write a reflection paper on what they learned from the panelists.
CITs can reflect on how counselors contribute to interdisciplinary teams using their developmental, prevention-focused, and wellness-based training.
Facilitate a broader discussion with CITs during the subsequent class meeting. |
Expert Panel Discussion Prompts:
Briefly discuss your ED treatment experiences and describe your main roles and responsibilities.
Discuss the benefits and challenges of working in interdisciplinary treatment teams.
What would you say are the most prevalent issues faced by ED professionals today?
What words of wisdom can you share with CITs considering working with ED clients?
Professional Identity
Paper Prompts:
· What challenges and opportunities do you foresee as a counselor working in an interdisciplinary treatment team?
· How can counseling values inform an interdisciplinary perspective on ED treatment?
· What personal strengths could you contribute as an interdisciplinary treatment team member?
· Reflect on the MJSCC (Ratts et al., 2016), discussing how they can inform a counselor’s work with diverse clients struggling with eating and/or body image concerns. |
Introduction to Mental Health Counseling Course:
If coordinating an ED expert panel is not feasible, consider inviting other professionals across specialty areas (e.g., EDs, addictions, integrated behavioral health) to share their experiences
CITs can complete a reflection paper on their insights and reactions to the guest panelists using the professional identity paper prompts as a guide.
|
Appendix B
Educator Checklist for Integrating the 3 Cs of Eating Disorder (ED) Education and Training Into Counselor Education Curricula
|
| Cultivating Trainee Self-Awareness |
|
Increase trainee awareness by incorporating ED warning signs, risk factors, and conceptualization strategies into assessment and treatment approaches. |
|
Routinely assess student competency on ED-related knowledge and skills, evaluating for any incongruence between the students’ and educators’ scores. Additionally, assess multicultural counseling competencies related to EDs during student evaluations. Provide feedback for growth. |
|
Encourage student attendance at ED-focused workshops, webinars, and conferences to enhance deliberate practice efforts, promoting professional growth and development. |
|
Promote student exploration of their own cultural identities, values, and biases related to appearance, health, and eating behaviors. |
| Capturing Contextual and Sociocultural Factors |
|
Incorporate diverse ED case examples and vignettes that reflect a range of intersecting cultural identities and experiences. |
|
Provide training on culturally responsive ED treatment approaches like RCT and intersectionality. Be sure to cover strategies for adapting evidence-based ED treatment approaches to be culturally relevant for diverse clients. |
|
Emphasize the importance of cultivating cultural humility and client empowerment, particularly when working with ED clients from diverse or marginalized backgrounds. |
| Collaborating With Interdisciplinary Professionals |
|
Critically examine course syllabi to identify where ED content and scholarship could be incorporated or expanded (e.g., textbooks, media, articles). Include resources from interdisciplinary helping professionals. |
|
Compile a list of interdisciplinary community referrals and resources to support students working with ED clients. |
|
Provide opportunities (e.g., guest lecture, course assignment) for students to learn from ED experts in various helping disciplines. Encourage students to reflect on ways to utilize their counseling values and training within interdisciplinary treatment collaborations. |
Note. This checklist is a framework for integrating ED education into CE graduate training. Consider modifying components to align with your specific curriculum, resources, and student population. The goal is to integrate ED education in a way that provides students with foundational knowledge, skills, and practical experience to effectively support clients struggling with EDs and body image issues in their future counseling practice.
Taylor J. Irvine, PhD, NCC, ACS, LMHC, is an assistant professor at Nova Southeastern University. Adriana C. Labarta, PhD, NCC, ACS, LMHC, is an assistant professor at Florida Atlantic University. Correspondence may be addressed to Taylor J. Irvine, Department of Counseling, Nova Southeastern University, 3300 S. University Dr., Maltz Bldg., Rm. 2041, Fort Lauderdale, FL 33328-2004, ti48@nova.edu.

