Jun 3, 2026 | Volume 16 - Issue 2
Dana Ripley, Justin R. Jordan, Jyotsana Sharma, Taylor Allesch
Research has consistently shown a link between substance use disorders and trauma; however, there is a need to explore the experience of dual recovery from these struggles. The purpose of this qualitative research study was to examine the lived experiences of individuals in recovery from both trauma and problematic substance use. This study involved semi-structured interviews with 10 individuals who identified as being in recovery from both trauma and substance use. A hermeneutic phenomenological approach was used to gain an in-depth understanding of the recovery experience. Emergent themes included the importance of social support, self-discovery, and that recovery is an ongoing process rather than a time-limited goal. Implications for understanding dual recovery and for counseling clients with dual trauma and substance use recovery experiences are explored.
Keywords: substance use, trauma, dual recovery, lived experiences, counseling
Research has established a link between addiction and trauma (Gidzgier et al., 2023; Jacobsen et al., 2001; Kilpatrick et al., 2013). Approximately 97.4% of individuals diagnosed with a substance use disorder (SUD) have been found to have experienced a traumatic event (Gielen et al., 2012). Farrugia et al. (2011) also found the prevalence of childhood trauma to be significantly higher among individuals with an SUD diagnosis compared to the general population. Problems with substance use are categorized as an SUD based on impairment of functioning and significant distress (American Psychiatric Association [APA], 2022), while trauma is defined by an acute event threatening one’s physical safety or complex, chronic experiences threatening one’s mental and emotional well-being over time (May & Wisco, 2016; Wamser-Nanney & Vandenberg, 2013). LeTendre and Reed (2017) found that increased exposure to adverse childhood experiences, such as exposure to domestic violence or having a parent with a serious mental health struggle, accounts for a 34% increase in the likelihood of developing an SUD in adulthood. A recent study focused on comparing indirect and direct exposure to traumatic events found an increased risk for substance use and behavioral addictions with both types of exposure (Levin et al., 2021). Direct exposure in this study included combat and sexual assault trauma. Childhood trauma is linked to substance use, with more extensive trauma histories predicting earlier initiation and greater severity of substance use (Farrugia et al., 2011).
Based on the research demonstrating a correlation between trauma and substance use, dual recovery experiences warrant exploration. In clinical treatment settings, clients will present with a need to address these co-occurring struggles. To date, research has focused primarily on the correlated pathology rather than the co-occurring healing and recovery process. To address this gap, this study aims to explore the lived experiences of individuals who self-report dual recovery experiences.
Understanding the Link Between Trauma and Addiction
Evidence suggests that individuals who have these co-occurring struggles have poorer treatment outcomes than clients with only one of these presenting issues (Brewerton & Brady, 2014). Although several explanations for the relationship between trauma and substance use exist, self-medication theory predominates (Hawn et al., 2020). Self-medication theory posits that substances are used to cope with and mitigate trauma-related symptoms. Despite offering a respite from unwanted hypervigilance, anxiety, or thoughts related to trauma, substances do not eliminate symptoms or resolve the underlying reactions. Self-medication suggests that a cycle of experiencing symptom distress and using substances to cope becomes problematic. Once the substances’ effects subside, the cycle may begin again, often with exacerbated emotional distress and additional concerns about one’s inability to control consumption.
Counter to self-medication, some theorists believe there is a relationship between post-traumatic stress disorder (PTSD) and the predisposition to substance use (Khoury et al., 2010; Van den Brink, 2015). Although not all individuals who identify as in recovery from trauma meet criteria for PTSD, research has often focused on creating sampling parameters to explore epidemiology and treatment protocols (Zrineh et al., 2026). Brewerton and Brady (2014) agreed that epigenetics and genetic predisposition may contribute to substance use vulnerability for people who have experienced significant traumas. Additionally, early trauma caused individuals in the study to feel abnormal and misunderstood, potentially leading them toward social groups involved in substance use (Brewerton & Brady, 2014).
Treatment Considerations
Traditionally, many treatment approaches have sought to disrupt this cycle via a sequential model of treatment, with substance use problems addressed first. This approach assumes that meaningful mental health treatment cannot be effective while a person is still impaired by regular substance use (Schumm & Gore, 2016). Newer evidence suggests that concurrently treating trauma and addiction shows promise in producing successful outcomes like reduced substance use and relapse, and improved quality of life (Flanagan et al., 2016). Concurrent treatment of trauma and substance use has become more widely accepted (Flanagan et al., 2016; Priester et al., 2016; Schumm & Gore, 2016). It remains unclear if this research has influenced treatment practices, especially in addiction programs not affiliated with research institutions (e.g., hospitals and universities). Scholars have recommended universal trauma screening for clients entering care for substance use (Van den Brink, 2015), and concurrent treatment is now seen as efficacious and safe (Flanagan et al., 2016). The National Institute on Drug Abuse (2014) recommends simultaneous treatment for these issues, acknowledging a correlation between substance use and underlying mental health struggles, including trauma.
Evidence that this concurrent approach leads to successful treatment for those who have experienced co-occurring substance use and trauma is accumulating. Studies have found that participants prefer an integrated approach to treatment, such as receiving treatment for both SUD and PTSD in the same treatment program (Brown et al., 1998; Gielen et al., 2016; Roberts et al., 2023). This, however, is not a common experience for individuals with co-occurring diagnoses (Gielen et al., 2016), as most substance use treatment programs do not include trauma-focused interventions (Giordano et al., 2016). The European Society for Traumatic Stress Studies utilized a systematic review of research and expert opinions to develop a list of nine assessment strategies and 21 treatment recommendations for co-occurring trauma and substance use (Roberts et al., 2023). These recommendations include: concurrent treatment, helping clients navigate logistical barriers to treatment (e.g., transportation), case management services, building a strong therapeutic relationship, and psychoeducation about the relationship between trauma and substance use. The current study aims to examine the lived experiences of people identifying as in recovery from both trauma and substance use, with the intent to clarify the phenomena of dual recovery.
Purpose of the Study
Understanding the process of dual recovery for individuals who experience traumatic events and have struggled with substance use is vital for providing appropriate care. The current study aimed to examine the lived experiences of people identifying as in recovery from both trauma and substance use issues, with a focus on their recovery journey over time. The purpose was to build on prior research that focused on trauma and substance use by exploring intersecting recovery processes, rather than etiology, and investigating the phenomenon of recovery by exploring lived experiences. A qualitative study design and methodology was utilized and guided by the overarching research question: What is the experience of recovery for someone who struggles with trauma and substance use?
It is important to acknowledge that a variety of recovery definitions exist. There is disagreement among experts regarding the precise language to describe recovery, and individuals choose to identify for themselves when they are in recovery without precise criteria (Piat et al., 2009). According to Neale and colleagues (2015), individuals in active recovery find previously established definitions to be limiting and focused on a deficit-based mindset and framework. Conceptualizations that are strength-based consider social and context influences and acknowledge that individual differences are preferred. Recent studies have moved away from offering their participants a definition of recovery; instead lived experiences and individual definitions of recovery conceived by the participants themselves are now common in addiction research (Zemore et al., 2023). The current study did not provide a definition of recovery to participants but focused on eliciting participants’ conceptualizations of what defines recovery to the individual.
Methods
In looking at the experience of recovery for someone who struggles with trauma and substance use, we intentionally sought a research methodology that would account for the depth and complexity of these life experiences. Given this focus, hermeneutic phenomenology was chosen as our research approach. Phenomenology aims to understand a phenomenon through the lens of those with direct experience (van Manen, 2016). Phenomenology prioritizes meaning making and attempts to get at the depth of experiences, as opposed to examining generalizable patterns across a broad range of perspectives (Hays & Singh, 2012). Through first-person accounts, phenomenology pulls together key descriptions to form a picture of an experience or phenomenon. Hermeneutic phenomenology was specifically chosen because it places participants as co-researchers (Hays & Singh, 2012). This means that participants are viewed as experts in the field of study, thus lessening the power differential between researcher and participant (Hays & Singh, 2012). Given the marginalization and stigma of those who experience substance use issues and trauma, it was important to utilize a method that recognizes power dynamics and attempts to diminish those between the researcher and the participants. This included asking participants to self-define their recovery status and what qualifies as being in recovery.
Reflexivity
Transparency regarding researcher perspective and positionality is essential in qualitative inquiry (Levitt et al., 2018). We are invested in advancing the understanding of recovery processes, especially among counselors who work with individuals with co-occurring trauma and substance use histories. Through this research, we hope to help counselors use this information to better support those they serve, as well as enhance the awareness of educators and supervisors. Dana Ripley, Justin R. Jordan, and Jyotsana Sharma have been colleagues through their doctoral program, are licensed counselors, and hold doctoral degrees in counselor education and supervision. Ripley, Jordan, and Sharma are currently tenure-track professors in counselor education programs, with Ripley and Jordan consistently teaching addiction counseling courses to master’s-level students. Taylor Allesch is pursuing licensure as a professional counselor and is a former student of Ripley. Ripley has a background in substance use and addictions counseling, which is also her primary teaching and research interest. She teaches at a public university in the Midwest United States. Jordan is a professor at a mid-sized public university in the southern United States. He has more than a decade of experience counseling individuals with trauma and substance use struggles in a public mental health agency and in private practice. Sharma is a professor at a large, research-focused university in the southern United States and has experience working with clients with trauma and other stress-related disorders. Allesch was a master’s student in clinical mental health counseling who completed her degree during the data collection and analysis phases of our study. She has experience addressing trauma in private practice settings, predominantly with couples and individuals.
Beginning with the initial planning for this study, we discussed how academic, research, personal, and treatment-providing experiences with addiction and trauma would affect development of the research protocol. None of the team members identify as being in recovery from substance use, although multiple members have experienced traumas of varying severity and chronicity. We collectively lean toward wellness-based interventions and respecting personal autonomy in navigating healing from substance use or trauma. Throughout the study, we held reflective discussions about how our experiences influenced the development of interview questions and interpretations of the coding process and distillation of themes, and we kept reflexive journals, which were audited by Sharma, and conveyed results in writing. This included exploring: the influence of client issues and treatment systems we had worked in; personal experiences with substances, trauma, and the impacts on those we care about; and research and literature that had impacted our perspectives on recovery journeys. We were deliberate and consistent in acknowledging personal perspectives and biases while attempting to allow the voices of study participants to be captured accurately and fully.
Participants
After securing IRB approval from our three affiliated institutions, participants were recruited through contacting peer recovery specialist organizations via email. Peer recovery specialists are trained as helping professionals who identify as being in recovery from substance use/addiction, or having mental health struggles, including trauma, or both, which is why we targeted this population for recruitment. Purposeful sampling was used to identify appropriate candidates who were recruited directly through organizational websites and through connections to local communities in Kentucky, Ohio, and Virginia. Snowball sampling was also used, as participants recommended other peers who might be interested in the study. Participants were not required to be trained as peer recovery specialists, but all participants were recruited through these networks. Emails to peer recovery specialists and associated organizations were sent with a link to an online screening survey utilizing Qualtrics software, which clarified which prospective participants met inclusion criteria.
The three inclusion criteria for this study were that participants must: be 18 or older, self-identify as being in recovery from substance use issues, and self-identify as being in trauma recovery. Because definitions of recovery vary, participants were not asked about the length of time since their last use of specific substances or the timeline of their trauma symptoms. Participants were asked to describe their recovery process from each struggle as part of the interview protocol; they were also asked how they define recovery. Although personal definitions vary, participants referenced government definitions, freedom from use or symptoms, normalcy in their lives, sustaining quality relationships, and having balance in their lives. Some participants referenced sustained abstinence from substances and reduction in trauma symptoms, while others spoke to the absence of chaotic behavior patterns and a sense of mental peace and calm. Potential participants who met eligibility criteria were contacted via email to schedule an interview. Each participant was sent a copy of informed consent documentation and gave verbal agreement to participate at the start of the interview.
Our final sample included 10 participants. Bartholomew et al. (2021) suggested that there is no specific range for sample sizes in phenomenological research, but 10 participants is within a normative range; larger samples often lose some of the essential qualities of this methodology. Other researchers have suggested three to 10 participants for phenomenological studies (Dukes, 1984).
In our study, participants’ ages ranged from 23 to 61, with a mean age of 42.2. Participants were asked open-ended questions regarding how they identified their gender, race/ethnicity, and sexual orientation. Two participants identified as male, with the rest identifying as female. Three participants identified as Black or African American, one as Hispanic, two as mixed race, and four as White. One participant identified as bisexual, one as lesbian, and the rest identified as heterosexual or straight. Table 1 summarizes pseudonyms and pertinent demographic information.
Table 1
Participant Demographics and Pseudonyms
| Participant |
Age |
Gender |
Race or Ethnicity |
Sexual Orientation |
Pseudonym |
| Participant 1 |
61 |
M |
White |
Heterosexual |
Jackson |
| Participant 2 |
46 |
F |
Hispanic |
Bisexual |
Dedra |
| Participant 3 |
49 |
F |
Black |
Heterosexual |
Erica |
| Participant 4 |
40 |
M |
African American |
Heterosexual |
Levon |
| Participant 5 |
31 |
F |
White |
Heterosexual |
Olivia |
| Participant 6 |
37 |
F |
White/Colombian |
Heterosexual |
Kara |
| Participant 7 |
41 |
F |
White/Puerto Rican |
Heterosexual |
Alecia |
| Participant 8 |
41 |
F |
White |
Heterosexual |
Rhonda |
| Participant 9 |
53 |
F |
Black |
Heterosexual |
Corva |
| Participant 10 |
23 |
F |
White |
Lesbian |
Rosemary |
Participant Background
The participants were thoughtful in sharing their unique experiences in recovery. Jackson is a 61-year-old heterosexual White man who spoke about an abusive father and his drug use causing him to miss time with his kids. He talked about self-forgiveness as a key part of his recovery. Dedra is a 46-year-old bisexual Hispanic woman who discussed being hit by a truck while intoxicated and the complications of receiving inpatient nursing care while being prescribed Suboxone for opioid addiction. Erica, a 49-year-old heterosexual Black woman, currently works in a harm reduction program and talked a lot about people who died in active use and how Narcotics Anonymous (NA) was key in her early recovery. Levon is a 40-year-old heterosexual African American man who spent 18 years in prison on charges related to alcohol and prescription pill use. He described trauma recovery as very difficult, as he did not realize how his lived experiences had led to impaired functioning, even after achieving sobriety. Olivia, a 31-year-old heterosexual White woman, is currently pursuing a degree in social work and is employed as a peer specialist. She feels the cognitive behavioral therapy she received for trauma and 12-step fellowship for addiction were essential for the healthy relationships she has in her life now.
Kara is a 37-year-old heterosexual biracial (Columbian/White) woman who turned to alcohol and other drugs after the death of her brother. She says pregnancy and parenthood helped push her toward recovery and she is an advocate for improving Methadone access. Alecia is a 41-year-old heterosexual biracial (Puerto Rican/White) woman, who credits a supportive probation officer for helping her work toward recovery after 20 years of active addiction. She is a supporter of multiple interventions for recovery, including harm reduction, prevention, and diversion programs. Rhonda, also 41, is a heterosexual White woman. She supports many pathways to recovery, but for her, becoming involved in her church was the key to making progress. Corva is a 53-year-old heterosexual Black woman who talked about how her chaotic childhood led her to cope with alcohol, as well as having an unhealthy relationship with food and sex. Finally, Rosemary is a 23-year-old lesbian White woman. She was a college student who participated in a collegiate recovery program and has found substance recovery through harm reduction rather than abstinence.
Data Collection
Participants gave verbal consent at the beginning of each interview. Data collection included semi-structured interviews (see Appendix for the interview protocol). Interviews were scheduled for 1 hour, and participants were advised that they may receive contact for a brief follow-up if clarification was needed (no participants were contacted for follow-up). Questions focused on the participants’ lived experiences of recovery from trauma and substance use. Zoom videoconferencing software was used to meet with the participants, and all interviews were video-recorded. The recordings were transcribed by Ripley, Jordan, and Allesch.
Data Analysis
Each transcript was read and coded by two members of the research team. Ripley, Jordan, and Allesch completed the coding. In reviewing the transcripts, each member used the selective or highlighting approach (van Manen, 2016). This approach requires several readings of the text, paying attention to statements that “seem particularly essential or revealing about the phenomenon or experience being described” (van Manen, 2016, p. 93). We highlighted these statements in the text, then copied and organized the data in an Excel spreadsheet with repetitive data being identified and deleted. Statements were synthesized into a phrase that encompassed the statement’s meaning. Using cross-case analysis (Patton, 2015), the statements were grouped based on focus and perceived meaning (coding), leading to initial coded themes. In hermeneutic phenomenology, themes are used to describe a common aspect of the experience (van Manen, 2016). Collaborative analysis, or hermeneutic conversations, were then conducted by the three coders (van Manen, 2016). This entailed coding team meetings in which members discussed patterns and content, and preliminary ideas for themes emerging from the transcripts. Each coding review meeting included Ripley, Jordan, and Allesch.
Collaborative analysis assures “themes are examined, articulated, re-interpreted, omitted, added, or reformulated” as needed (van Manen, 2016, p. 100). Ripley, Jordan, and Allesch met several times over 4 months for collaborative analysis to calibrate and reach consensus regarding emergent themes. They examined lines of text that seemed to capture the essence of the recovery phenomenon and experience. We generated ideas for thematic groupings and descriptions; some themes were dropped because of inconsistency or lack of consensus, including a theme focused on “giving back” in recovery, which did not have the same amount of participant endorsement as the other themes. These dialogues included examining potential biases in interpreting transcripts, exploring overlaps and distinctions between themes, and ensuring each theme was evaluated and agreed upon amongst us. Once consensus was reached, themes were audited by Sharma. Sharma checked each coded statement to ensure its match to the assigned theme and then reported potential mismatches or poorly fitting codes to Ripley, Jordan, and Allesch. Further meetings and dialogues were held to work through different interpretations until consensus was met for all themes and coded statements (sometimes, a vote was held, requiring a majority to move forward). Themes were considered sufficiently refined when we all agreed that the essence of the interviews had been captured and no additional themes were needed to understand the participants’ experiences.
Trustworthiness
Our research team engaged in several strategies to enhance the trustworthiness of our findings. Researcher bias was addressed using reflexive journals (Hays & Singh, 2012). Reflexive journals were kept by Ripley, Jordan, and Allesch. After each interview, the interviewer would write a reflexive journal documenting thoughts, assumptions, feelings, and reactions to the interview. The reflexive journals were read and examined for influence on code/theme generation by Sharma while auditing the themes. Sharma spoke about the journals and inquired about biases during meetings. Based on this feedback, the coding team was able to talk through and mitigate biases that affected data analysis, including transference related to personal and professional experiences.
Trustworthiness was also ensured using triangulation with multiple analysts (Patton, 2015). Ripley, Jordan, and Allesch conducted interviews and coded the transcripts, thus helping to “reduce the potential bias that comes from a single person doing all the data collection” and analysis (Patton, 2015, p. 665). Additionally, Sharma did not participate in conducting interviews or the initial coding process. Sharma audited the coding and themes without prior exposure to the data, with the intent of remaining objective.
Findings
Interviews with 10 participants were analyzed via a hermeneutic phenomenological approach. Six themes emerged from the interviews and subsequent coding process: recovery is hard, recovery includes structured support services, recovery is an ongoing process, recovery is relational, recovery is self-discovery, and substance use and trauma recovery are interconnected. These themes encompass defining characteristics of the dual recovery journey for the 10 participants in our study.
Recovery Is Hard
Participants discussed how working toward and living in recovery comes with many challenges, especially related to stigmas and navigating systemic barriers in receiving help. Looking for support early in their substance use recovery process, Dedra highlighted, “Even if I’m an addict, I still deserve the proper treatment and proper care and proper empathy, and I didn’t get that.” She elaborated that, “I had to fight for myself; nobody else was doing it so I just had to fight hard.” Rhonda talked about multidimensional challenges that led to being overwhelmed in early substance use recovery, stating, “The hardest thing for me to get over in that first year is changing absolutely everything.”
Another common difficulty that participants expressed was finding a place to “fit in.” After experiencing traumas related to homelessness during pregnancy while simultaneously managing a chronic blood illness, Kara described, “I think some of the hardest parts for me were just sort of like learning how to reintegrate in society, and I think that continues to be hard for me, like ‘where do I fit in here?’” Kara felt that finding a sense of belonging was essential for healing, given the disconnection from supports she experienced before pursuing recovery. In pursuing formal treatment for co-occurring struggles, Kara indicated that she encountered “all these wait lists,” and shared, “if you want to go to a program . . . you can’t get in right away.” Olivia also described substance use and trauma having “such a stigma on it already anyway, receiving any kind of mental health service . . . it just seemed so unobtainable.” Dedra discussed judgment within the substance use recovery community because of being prescribed Suboxone, a medication used to treat opioid use disorder: “I experienced a lot of stigma because I was an opiate user and they had to put me on Suboxone. I just had all this weird treatment toward me that was so uncomfortable, so embarrassing, and really degrading.” Participants had a lot to overcome in order to receive support in pursuing recovery and sustaining their efforts amidst treatment barriers and social stigma. Some participants reported that they had to learn how to advocate for themselves because of the lack of support and barriers they encountered trying to seek support.
Recovery Includes Structured Support Services
Most participants emphasized the necessity of structured support such as mental health and substance use treatment programs, mutual self-help groups (AA and NA), and other systems (e.g., church) as essential to their recovery journeys. The theme of recovery includes structured support services encompasses the importance of treatment programs, groups, and organizations that provide help to participants. Participants talked about the importance of these support systems to help people work toward change early on in pursuing recovery. Olivia benefited from both mutual self-help and professional therapy, sharing:
I personally worked a 12-step program [for substance recovery], and so, in that, [my counseling] was really based more on my trauma than it was actual substance use and I, I went to counseling and just a lot of things like that. . . . cognitive behavioral therapy is really what helped me work through those childhood traumas that I had, and the trauma that I added on to it as an adult, and it was difficult.
She elaborated about positive experiences working on trauma in formal treatment: “When I went into that treatment setting, the people there were already so well equipped to handle the kind of things that I needed to talk about, that I wanted to talk about.” Speaking more broadly, Olivia shared the importance of having multiple systems for support in dual recovery, saying, “I also think it’s really important to be able to connect people to a lot of different services, kind of like the wraparound services.” Jackson also benefited from both mutual self-help groups and formal treatment, stating: “When I got out [of incarceration], I did kind of dive into AA, which was integral, in my early recovery, and, you know, continued to see my therapist [for trauma counseling].”
Kara found out that she was pregnant while she was incarcerated and did an intensive 3-year program for women who were prescribed Methadone and pregnant. She reported this as an important step for her recovery. That group meant a lot to her. When asked about her trauma recovery process, Alecia talked about a peer specialist being a role model when she entered treatment, saying, “I can do this. If she can do it, I can do it,” as well as participating in SMART [Self-Management and Recovery Training] Recovery meetings. She expressed that this specialist helped her feel understood as someone who had been incarcerated and using substances to subdue childhood trauma symptoms. Overall, this theme showed that participants felt that they could not achieve sustained recovery on their own and benefited from programs, services, and mutual help spaces in healing from trauma and addiction.
Recovery Is an Ongoing Process
Another theme that emerged from the interviews was that recovery is an ongoing and continuous process. Participants described their recovery from trauma and substance use as continuing to unfold, rather than a destination where they had already arrived. This process was discussed as an individual journey because, as they recovered, each person had to make choices about what resources to utilize and what changes fit their lives. Several participants explicitly identified that their co-occurring recovery is a continuous process. In characterizing her journey in dual recovery as being unique, Rosemary stated: “It took time for me to learn that recovery is a spectrum, and there’s not one right way to do this.” Alecia agreed with this theme and made similar statements, including: “I know this is a process that I’ll go through for the rest of my life.” In speaking primarily to substance recovery, Rhonda had similar sentiments, sharing her belief that “everybody’s not the same, and there’s so many different paths out there now. It’s just finding the right path in the right way for you.” She added, “Yes, I went to treatment, but I don’t use that as my recovery. My recovery was honestly therapy and going to church.”
This theme encompasses descriptions of making broad lifestyle changes and continuing to grow as a human, while still acknowledging the influence of substance use and trauma in one’s life journey.
Recovery Is Relational
All participants spoke to relationships as they related to their recovery journeys. This theme is given more attention here, as it was the most frequently coded and consistent theme. Recovery is relational focuses on the importance of bonding and human connection in the recovery process. This theme is distinct from the theme of recovery includes structured support services, which focuses on therapy/counseling, education, or tangible resources, such as medications or financial assistance, rather than the general importance of interpersonal relationships.
Specifically, participants highlighted how relationships facilitated recovery, which included connections to individuals in the mutual self-help community, professionals, and treatment providers, but also support from their families, friends, and community. These connections helped participants cultivate hope and accountability as they progressed in healing from substance use and trauma. The sense of being understood and accepted through the challenges of recovery was impactful and motivating.
Jackson described the importance of his relationship with his 12-step sponsor, a high school teacher that “really got me.” His sponsor worked the steps with Jackson, trying to understand Jackson’s unique perspectives on the steps and recovery. He described his sponsor as patient and intelligent. The sponsor was able to repackage the AA message in a way that fit for Jackson, who said that “if I hadn’t had somebody like that, I wouldn’t have stopped.” Kara and Erica similarly shared the importance of relationships in the 12-step community, including not feeling alone in pursuing recovery.
Sources of support varied widely in our study. Olivia described the important relationship she had with her children’s foster parent. Not only did the foster parent take care of her children, but she became an integral part of Olivia’s life; she described her as “my absolute biggest supporter.” This foster parent helped her build back community and showed her that it is possible to live the kind of life she had always wanted.
Other participants also emphasized the benefits of community and support broadly. Olivia shared that she had to learn new ways of living and building relationships within her community. Her local community has been essential to her success in recovery. She detailed how this support facilitated recovery from trauma and substance use:
I spent almost an entire year just digging through those things and opening up and sharing about them, and that’s also where I built that first sense of community of speaking on those traumas with like-minded people who had been through similar situations.
Alecia spoke about the significant support she received from her probation officer. She stated that having a probation officer who really understood her and wanted to see her succeed was “a game changer.” The probation officer’s investment in her was a turning point for Alecia. Corva felt that recovering from both issues has given her relationships authentic connection: “Being around people who really know us and know us at our depth and, you know, and that’s what life is truly about. So, for me, that’s what recovery is about. And it’s given me a family.”
Participants were consistent in pointing to relationships boosting their success in recovery, which included building back bonds with people they had lost touch with or been cut off from during active use, as well as building a new network of support. The theme of recovery is relational had the highest number of identified codes from participants supporting the theme.
Recovery Is Self-Discovery
Participants identified the development of self-awareness and connecting with themselves as part of their recovery. This theme of recovery is self-discovery included emphasizing new personal growth since confronting trauma and addressing substance use struggles, including reconnecting with prior values and aspects of their identity. Additionally, participants described self-awareness as a key component of their life in recovery, including being honest with themselves and processing emotions that they may have avoided previously. Epitomizing this theme, Jackson stated:
So much of my recovery is about finding my place in the world—that sense of comfort and connection and stuff. A lot of my trauma that I experienced entails me forgiving other people. This, you know, is forgiving myself for the mistakes I’ve made, which I still struggle with, but also is letting go of resentments.
When asked about critical points in his recovery, Levon also spoke about personal development, saying that he started to see how to present a stronger version of himself, knowing internally that he was courageous and could fight through obstacles. Olivia added that she had created walls that served the purpose of protecting her but had to “chip away” at those protections for her true self to emerge in recovery.
In terms of confronting emotions and suppressed thoughts, Dedra shared that trauma recovery required “this ability, which only came to me late in life, to just be objective with my own self, and to be honest and objective about what [trauma is] doing, and who I am, and what’s happening to me.” In connecting this to substance use recovery, both Dedra and Rosemary agreed that self-awareness and honesty are key to recovery and that secrets can continue the cycle. Multiple participants alluded to increased self-awareness, understanding, and reconnection with their true self as being an important part of the recovery process.
Substance Use and Trauma Recovery Are Interconnected
The theme of substance use and trauma recovery are interconnected was described in multiple ways by participants, often referencing trauma being an underlying aspect of substance use struggles. Participants spoke about realizing the connectedness of trauma, mental health issues, and substance use in recovery. Erica acknowledged the close connection between substance use and trauma recovery, saying that “they just kind of overlap and intersect, and it’s kind of hard to differentiate where one ends and one begins.” Dedra spoke about trauma being the underlying issue, explaining, “Trauma is the root for me, and you know, with other people it might be that, you know, once they quit drinking, things get better, but I’ve always had to struggle with trauma.” Levon also described that he was unaware of how affected by trauma he was, recounting: “Trauma drove the substance use in that sense . . . because the trauma had certain effects on me that I didn’t [recognize].”
Additionally, participants noted that addressing trauma, including associated mental health concerns, along with substance use, was an essential part of recovery. Jackson spoke about the importance of getting help with mental health diagnoses, which he didn’t start until 10 years after engaging in substance use recovery. He had experienced multiple hospitalizations related to suicide attempts, which eventually spurred him to address his mental health:
But it was at that point I kind of really took my mental health issues as seriously as I took my substance use issues because it was easy to see that my substance use issues were killing me, were going to kill me. It’s harder to see that with mental health issues.
Alecia used similar language, describing that “addiction is just one of the symptoms of trauma, and . . . you can’t get to the root with the symptoms still there.” The direct relationship between trauma healing and substance use recovery was consistent in the interviews. Participants were directly asked if these recovery processes were related, and all participants replied affirmatively and elaborated on the reasons for this connection. Although many responses highlighted the trauma as an underlying cause of substance use, the responses showed that in conceptualizing the recovery process, healing from each was interconnected.
Discussion
Six themes emerged from the phenomenological analysis of these 10 interviews focused on the experience of trauma and substance use recovery: recovery is hard, recovery includes structured support services, recovery is an ongoing process, recovery is relational, recovery is self-discovery, and substance use and trauma recovery are interconnected. Taken as a whole, these themes demonstrate that the lived experience of dual recovery from substance use and trauma is an individual, holistic journey supported by personal and formal relationships. There is an inherent connection between trauma and substance use recovery for these participants. This type of dual recovery includes hardships on the path to healing for both trauma and substance use. Among our participants, there were multiple pathways to recovery, and yet there were parallels in how they described essential elements of long-term recovery. Recovery is a forward-focused endeavor rather than a cure for pathology (Witkiewitz et al., 2020), which is a useful perspective for laypersons and professionals who offer guidance to people working to overcome trauma symptoms and substance use addictions.
This study deepens the understanding of dual recovery from these correlated struggles, which counselors commonly address. Acknowledging the ongoing nature of recovery reduces the focus on acute symptom management and shifts the focus toward lifestyle factors such as relationships. These themes support an individualized self-exploration process for discovering a new sense of self within substance use and trauma recovery. All participants indicated that these two recovery processes were correlated. This finding supports a simultaneous approach to healing substance use and trauma, as opposed to a historical emphasis on sequential treatment.
These findings call for a focus on development and wellness congruent with counselor professional identity (Woo et al., 2014), in contrast to a medical model framework. Conceptualizing recovery as an ongoing purpose, rather than a destination, supports the benefits of counselors embracing holistic wellness and developmental perspectives. Participants described a long-term process enabled by relationships and structured support, calling on counselors to be responsive to recovering clients’ ongoing healing journeys. This aligns well with how counselors join clients in pursuing meaningful, multidimensional changes in their lives (Woo et al., 2014) rather than focusing solely on symptom reduction. Trauma and substance use are correlated, but each individual navigates unique challenges in pursuing a better life in recovery. This healing is not just alleviating symptoms but rather finding new identities and maintaining wellness daily. These findings demonstrate that counselors benefit from recognizing that there is no one-size-fits-all approach to dual recovery. Long-term support is needed in recovery and that care should target both trauma and substance use in order to be successful. The participants acknowledged that addressing the trauma at the root of their struggles would benefit both their mental wellness and ability to avoid harmful substance use. Our participants have given us evidence in their own voices to help clarify what the phenomenon of co-occurring recovery looks like.
Refining the understanding of recovery as a process advances the pursuit of better supports for survivors persevering through trauma and substance use that has negatively impacted their lives. Recognizing that trauma and substance use recoveries are intertwined calls for services designed to support the long-term healing process. This recognition also discredits siloed treatments that do not address co-occurring needs. The importance of relationships and support networks was clear, as was the individualized nature of the recovery process over time. Counselors are trained and equipped to meet clients where they are by matching interventions to individual needs. This means cultivating recovery based on clients’ unique strengths rather than using cookie-cutter prescriptive approaches to support sustained recovery.
Implications for Counselors
Counseling, being defined as a relationship that facilitates growth and healing (Kaplan et al., 2014), is a fitting intervention for people pursuing recovery. Emphasizing holistic wellness, supporting development through the lifespan, and honoring the specific needs of the client are all aspects of professional counselors’ duty (American Counseling Association [ACA], 2014). Counselors are uniquely equipped to provide holistic and development-focused support for individuals in dual recovery, given that these approaches are congruent with counselor professional identity (Woo et al., 2014).
Historically, addiction treatment has relied on a prescriptive, sequential approach to substance use recovery, usually involving the pursuit of sobriety before addressing mental health concerns. Recent research supports concurrent treatment as best practice for treating trauma and substance use (Garland et al., 2015; Roberts et al., 2023; Schumm & Gore, 2016). This approach to co-occurring treatment supports the holistic approach emphasized by leaders and researchers in the counseling profession (Dollarhide & Oliver, 2014; Fickling, 2023; Kaplan et al., 2014). Valuing client autonomy and personal preferences in navigating recovery is necessary for counselors, which aligns with the individuality of recovery journeys found in our study. This research demonstrates that for many individuals, trauma struggles were not addressed until after they managed substance use effectively, which likely inhibited progress and overall wellness. Additionally, counselors integrating wellness, prevention, and developmental perspectives can help these individuals thrive long after the pathology of acute addiction or trauma symptomology is relieved.
Motivational interviewing and principles of trauma-informed care embrace this stance, including focusing on empowering the individual on their own terms and assuming a natural tendency toward growth (Miller & Rollnick, 2023). Addiction treatment, specifically, has traditionally been confrontational and behaviorally focused (White & Miller, 2007). This contradicts a trauma-informed approach to recovery and is particularly concerning given the high rates of co-occurrence between these struggles (Dore et al., 2012; Giordano et al., 2016). Harm reduction is another approach that fits for dually recovering individuals based on these findings. One of the main hardships that participants described was the experience of stigma because of their substance use. This approach mitigates stigma by focusing on wellness without judgment (Collins & Clifasefi, 2023). Harm reduction is a humanistic and pragmatic approach that prioritizes autonomy and the holistic well-being of the individual. Harm reduction is uniquely suited to co-occurring trauma and addiction, given its emphasis on collaboration with those being helped, a trauma-informed approach, and avoiding retraumatization through power-over dynamics. This philosophy has been adapted as an approach to psychotherapy by multiple scholars (Collins & Clifasefi, 2023; Tatarsky & Kellogg, 2012). Some participants had awareness, knowledge, and experiences receiving or providing harm reduction care and expressed their support for harm reduction within the continuum of services supporting substance use recovery.
With trauma, counselors may wish to engage with post-traumatic growth phenomena, as well as validating the natural tendency toward self-improvement, wellness, and growth. With substance use, counselors can draw from motivational interviewing, harm reduction, and self-guided changes to empower clients to take responsibility for personal change and respect their autonomy in the process. In supporting the dual recovery process, professional counselors can honor the unique strengths and meaning created through relationships, self-discovery, overcoming barriers, and the unfolding pursuit of growth in their clients.
Limitations
The current study did not differentiate the types of substances participants were recovering from, nor did it focus on specific types of trauma. Our research team intentionally focused on self-defined experiences with these struggles and the phenomena of recovery rather than the etiology of the struggle. It is difficult for these themes to be applied to substance use or trauma separately, as most interview questions focused on the participants’ experiences in co-occurring recovery. Sometimes, there was a clear distinction in which process, or sequential experience with recovery, they were referring to; those are noted in the Findings section. However, by design, most of the time, they were speaking about the dual recovery process. It is likely that complex trauma recovery may have phenomenological differences from acute event traumas. Similarly, recovery from different types of substances includes unique needs and experiences, such as medication treatment for opioid use recovery. During the coding and theme development process, our researchers may have been influenced by prior definitions of recovery in the literature. Despite this influence, our research team was diligent in focusing on giving voice to the participants as they reviewed coded statements from the interviews in clustering emergent themes.
Broadly, our study provides nuance in conceptualizing the phenomenon of dual recovery from trauma and substance use, but it cannot be generalized given that it is a qualitative study. Our study was limited geographically and by purposeful sampling. It is noteworthy that peer recovery specialists may have received education or exposure as helpers that has influenced their conceptualizations of recovery, which may differ from the broader population of individuals recovering from trauma and substance use. Finally, recovery as an experience extends to many other struggles beyond trauma and substance use issues, and it is unclear if the themes found in the current study would apply to other medical or mental health recoveries.
Future Research
These findings build on prior studies examining how substance use and trauma experiences are correlated and provide an in-depth look at the phenomenon of recovery with 10 individuals. Future studies may utilize quantitative methodology to determine if the themes found in this study are generalizable to people in recovery from trauma and substance use. Research is also needed to explore the specific experiences of peer recovery specialists in dual recovery. Additionally, further research may also explore factors that differentiate trauma recovery from substance use recovery experiences, both for individuals with co-occurring recoveries and those who only identify as being in recovery from one or the other. The current study adds to the research in a significant way but also reinforces a need for more studies looking at subtleties of recovery experiences.
Conclusion
Recovery is a multidimensional process that is defined by wellness and improved overall functioning (Witkiewitz et al., 2020). The current study examined the experience of recovery for 10 individuals identifying as in recovery from both substance use and trauma using hermeneutic phenomenology. Six themes emerged that conceptualize recovery from trauma and substance use as an ongoing, interconnected, individualized process that includes hardships and self-discovery and is facilitated by relationships and formal services. These findings support existing research calling for a concurrent and holistic approach for counseling individuals pursuing recovery from substance use and trauma-related symptoms.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
American Counseling Association. (2014). ACA code of ethics. https://bit.ly/ACAcodeofethics
American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.).
Bartholomew, T. T., Joy, E. E., Kang, E., & Brown, J. (2021). A choir or cacophony? Sample sizes and quality of conveying participants’ voices in phenomenological research. Methodological Innovations, 14(2), 1–14. https://doi.org/10.1177/20597991211040063
Brewerton, T. D., & Brady, K. (2014). The role of stress, trauma, and PTSD in the etiology and treatment of eating disorders, addictions, and substance use disorders. In T. D. Brewerton & B. Dennis (Eds.), Eating disorders, addictions and substance use disorders (pp. 379–404). Springer Berlin.
https://doi.org/10.1007/978-3-642-45378-6
Brown, P. J., Stout, R. L, & Gannon-Rowley, J. (1998). Substance use disorder-PTSD comorbidity: Patients’ perceptions of symptom interplay and treatment issues. Journal of Substance Abuse Treatment, 15(5), 445–448. https://doi.org/10.1016/s0740-5472(97)00286-9
Collins, S. E., & Clifasefi, S. L. (2023). Harm reduction treatment for substance use. Hogrefe. https://doi.org/10.1027/00507-000
Dollarhide, C. T., & Oliver, K. (2014). Humanistic professional identity: The transtheoretical tie that binds. The Journal of Humanistic Counseling, 53(3), 203–217.
https://doi.org/10.1002/j.2161-1939.2014.00057.x
Dore, G., Mills, K., Murray, R., Teesson, M., & Farrugia, P. (2012). Post-traumatic stress disorder, depression and suicidality in inpatients with substance use disorders. Drug and Alcohol Review, 31(3), 294–302. https://doi.org/10.1111/j.1465-3362.2011.00314.x
Dukes, S. (1984). Phenomenological methodology in the human sciences. Journal of Religion and Health, 23(3), 197–203. https://doi.org/10.1007/BF00990785
Farrugia, P. L., Mills, K. L., Barrett, E., Back, S. E., Teesson, M., Baker, A., Sannibale, C., Hopwood, S., Rosenfeld, J., Merz, S., & Brady, K. T. (2011). Childhood trauma among individuals with co-morbid substance use and post-traumatic stress disorder. Mental Health and Substance Use, 4(4), 314–326.
https://doi.org/10.1080/17523281.2011.598.462
Fickling, M. J. (2023). Greater than the sum of its parts: A view of professional counseling grounded in history and looking toward the future. The Journal of Humanistic Counseling, 62(3), 216–226. https://doi.org/10.1002/johc.12210
Flanagan, J. C., Korte, K. J., Killeen, T. K., & Back, S. E. (2016). Concurrent treatment of substance use and PTSD. Current Psychiatry Reports, 18(8), 70. https://doi.org/10.1007/s11920-016-0709-y
Garland, E. L., Pettus-Davis, C., & Howard, M. O. (2013). Self-medication among traumatized youth: Structural equation modeling of pathways between trauma history, substance misuse, and psychological distress. Journal of Behavioral Medicine, 36(2), 175–185. https://doi.org/10.1007/s10865-012-9413-5
Gidzgier, P. A., Bari, M., López-Atanes, M., Lotzin, A., Grundmann, J., Hiller, P., Shneider, B., & Schäfer, I. (2023). Improving care for SUD patients with complex trauma-relationships between childhood trauma, dissociation, and suicidal behavior in female patients with PTSD and SUD. Frontiers in Psychiatry, 13, 1047274. https://doi.org/10.3389/fpsyt.2022.1047274
Gielen, N., Havermans, R. C., Tekelenburg, M., & Jansen, A. (2012). Prevalence of post-traumatic stress disorder among patients with substance use disorder: It is higher than clinicians think it is. European Journal of Psychotraumatology, 3(1). https://doi.org/10.3402/ejpt.v3i0.17734
Gielen, N., Krumeich, A., Tekelenburg, M., Nederkoorn, C., & Havermans, R. C. (2016). How patients perceive the relationship between trauma, substance abuse, craving, and relapse: A qualitative study. Journal of Substance Use, 21(5), 466–470. https://doi.org/10.3109/14659891.2015.1063717
Giordano, A. L., Prosek, E. A., Stamman, J., Callahan, M. M., Loseu, S., Bevly, C. M., Cross, K., Woehler, E. S., Calzada, R.-M. R., & Chadwell, K. (2016). Addressing trauma in substance abuse treatment. Journal of Alcohol and Drug Education, 60(2), 55–71.
Hawn, S. E., Cusack, S. E., & Amstadter, A. B. (2020). A systematic review of the self-medication hypothesis in the context of posttraumatic stress disorder and comorbid problematic alcohol use. Journal of Traumatic Stress, 33(5), 699–708. https://doi.org/10.1002/jts.22521
Hays, D. G., & Singh, A. A. (2012). Qualitative inquiry in clinical and educational settings. Guilford.
Jacobsen, L. K., Southwick, S. M., & Kosten, T. R. (2001). Substance use disorders in patients with posttraumatic stress disorder: A review of the literature. The American Journal of Psychiatry, 158(8), 1184–1190.
Kaplan, D. M., Tarvydas, V. M., & Gladding, S. T. (2014). 20/20: A vision for the future of counseling: The new consensus definition of counseling. Journal of Counseling & Development, 92(3), 366–372.
https://doi.org/10.1002/j.1556-6676.2014.00164.x
Khoury, L., Tang, Y. L., Bradley, B., Cubells, J. F., & Ressler, K. J. (2010). Substance use, childhood traumatic experience, and posttraumatic stress disorder in an urban civilian population. Depression and Anxiety, 27(12), 1077–1086. https://doi.org/10.1002/da.20751
Kilpatrick, D. G., Resnick, H. S., Milanak, M. E., Miller, M. W., Keyes, K. M., & Friedman, M. J. (2013). National estimates of exposure to traumatic events and PTSD prevalence using DSM-IV and DSM-5 criteria. Journal of Traumatic Stress, 26(5), 537–547. https://doi.org/10.1002/jts.21848
LeTendre, M. L., & Reed, M. B. (2017). The effect of adverse childhood experience on clinical diagnosis of a substance use disorder: Results of a nationally representative study. Substance Use & Misuse, 52(6), 689–697. https://doi.org/10.1080/10826084.2016.1253746
Levin, Y., Bar-Or, R. L., Forer, R., Vaserman, M., Kor, A., & Lev-Ran, S. (2021). The association between type of trauma, level of exposure and addiction. Addictive Behaviors, 118, 106889. https://doi.org/10.1016/j.addbeh.2021.106889
Levitt, H. M., Bamberg, M., Creswell, J. W., Frost, D. M., Josselson, R., & Suárez-Orozco, C. (2018). Journal article reporting standards for qualitative primary, qualitative meta-analytic, and mixed methods research in psychology: The APA Publications and Communications Board task force report. American Psychologist, 73(1), 26–46. https://doi.org/10.1037/amp0000151
May, C. L., & Wisco, B. E. (2016). Defining trauma: How level of exposure and proximity affect risk for posttraumatic stress disorder. Psychological Trauma: Theory, Research, Practice, and Policy, 8(2), 233–240. https://doi.org/10.1037/tra0000077
Miller, W. R., & Rollnick, S. (2023). Motivational interviewing: Helping people grow and change (4th ed.). Guilford.
National Institute on Drug Abuse (2014). Principles of drug addiction treatment: A research-based guide (3rd ed.). https://nida.nih.gov/sites/default/files/podat-3rdEd-508.pdf
Neale, J., Tompkins, C., Wheeler, C., Finch, E., Marsden, J., Mitcheson, L., Rose, D., Wykes, T., & Strang, J. (2015). “You’re all going to hate the word ‘recovery’ by the end of this”: Service users’ views of measuring addiction recovery. Drugs: Education, Prevention and Policy, 22(1), 26–34.
https://doi.org/10.3109/09687637.2014.947564
Patton, M. Q. (2015). Qualitative evaluation and research methods. SAGE.
Piat, M., Sabetti, J., Couture, A., Sylvestre, J., Provencher, H., Botschner, J., & Stayner, D. (2009). What does recovery mean for me? Perspectives of Canadian mental health consumers. Psychiatric Rehabilitation Journal, 32(3), 199–207. https://doi.org/10.2975/32.3.2009.199.207
Priester, M. A., Browne, T., Iachini, A., Clone, S., DeHart, D., & Seay, K. D. (2016). Treatment access barriers and disparities among individuals with co-occurring mental health and substance use disorders: An integrative literature review. Journal of Substance Abuse Treatment, 61, 47–59.
https://doi.org/10.1016/j.jsat.2015.09.006
Roberts, N. P., Lotzin, A., & Schäfer, I. (2023). Psychological treatment of PTSD with comorbid substance use disorder (SUD): Expert recommendations of the European Society for Traumatic Stress Studies (ESTSS). European Journal of Psychotraumatology, 14(2). https://doi.org/10.1080/20008066.2023.2265773
Schumm, J. A., & Gore, W. L. (2016). Simultaneous treatment of co-occurring posttraumatic stress disorder and substance use disorder. Current Treatment Options in Psychiatry, 3(1), 28–36. https://doi.org/10.1007/s40501-016-0071-z
Tatarsky, A., & Kellogg, S. (2012). Harm reduction psychotherapy. In G. A. Martlatt, M. E. Larimer, & K. Witkiewitz (Eds.), Harm reduction: Pragmatic strategies for managing high-risk behaviors (2nd ed., pp. 36–60). Guilford.
Van den Brink, W. (2015). Substance use disorders, trauma, and PTSD. European Journal of Psychotraumatology, 6(1). https://doi.org/10.3402/ejpt.v6.27632
van Manen, M. (2016). Researching lived experience: Human science for an action sensitive pedagogy (2nd ed.). Routledge. https://doi.org/10.4324/9781315421056
Wamser-Nanney, R., & Vandenberg, B. R. (2013). Empirical support for the definition of a complex trauma event in children and adolescents. Journal of Traumatic Stress, 26(6), 671–678. https://doi.org/10.1002/jts.21857
White, W. L., & Miller, W. R. (2007). The use of confrontation in addiction treatment: History, science and time for change. The Counselor, 8(4), 12–30. https://www.researchgate.net/publication/265148872_The_Use_of_Confrontation_in_Addiction_Treatment_History_Science_and_Time_for_Change_A_History_of_Confrontational_Therapies
Witkiewitz, K., Montes, K. S., Schwebel, F. J., & Tucker, J. A. (2020). What is recovery? Alcohol Research: Current Reviews, 40(3), 1. https://doi.org/10.35946/arcr.v40.3.01
Woo, H., Henfield, M. S., & Choi, N. (2014). Developing a unified professional identity in counseling: A review of the literature. Journal of Counselor Leadership and Advocacy, 1(1), 1–15. https://doi.org/10.1080/2326716X.2014.895452
Zemore, S. E., Ziemer, K. L., Gilbert, P. A., Karno, M. P., & Kaskutas, L. A. (2023). Understanding the shared meaning of recovery from substance use disorders: New findings from the What Is Recovery? study. Substance Abuse: Research and Treatment, 17. https://doi.org/10.1177/11782218231199372
Zrineh, A., Al-Usta, M., & Alwawi, A. (2026). Sampling methods and sample size determination in clinical research: An educational review. Journal of General and Family Medicine, 27(1), Article e70096. https://doi.org/10.1002/jgf2.70096
Appendix
Interview Protocol
Research Question: What is the experience of recovery for someone who struggles with substance use and trauma?
- When I say the word “recovery,” what comes to mind? How do you define “recovery”?
- Tell me about the process of your recovery from trauma.
- Tell me about the process of your recovery from substance use.
- Do you feel your recovery process from substance use and trauma are related? If so, can you describe how?
- What are some of the critical moments or turning points in your recovery?
- Describe in as much detail as possible what you struggled with the most during recovery and how you managed those struggles.
- How has being in recovery influenced your life and what have you learned from those experiences?
- If you could go back and change anything about the process of your recovery, what would it be?
Dana Ripley, PhD, LPC (KY, VA), is an associate professor at Northern Kentucky University. Justin R. Jordan, PhD, LPC (VA), LSATP (VA), is an assistant professor at Longwood University. Jyotsana Sharma, PhD, LCMHC (NH), ACS, is an associate professor at Oklahoma State University. Taylor Allesch, MS, LPC (OH), LPCA (KY), is a professional counselor at Be Known: Sex and Relationship Counseling. Correspondence may be addressed to Justin R. Jordan, 201 High Street (222 Hull Hall), Farmville, VA 23909, jordanjr2@longwood.edu.
Apr 1, 2026 | Volume 16 - Issue 1
Emily Goodman-Scott, Rawn Boulden, Aaron Albright, Jenna Alvarez, Betsy M. Perez
The counseling profession is rooted in prevention, wellness, mental health, and a critical social justice approach to serving historically marginalized communities, including people with disabilities. The overarching construct of disability comprises subtypes, such as neurodivergence. Given the prevalence of neurodivergent individuals worldwide (approximately 15%–20%), the counseling profession must be prepared to support this community. At the same time, there is a dearth of peer-reviewed literature on neurodiversity specifically for the counseling profession. In this article, we address a timely topic in the profession. We discuss utilizing a critical counseling lens and centering marginalized identities, such as people with disabilities; prominent disability models, including the neurodiversity paradigm; and suggestions to infuse neurodiversity throughout the counseling profession.
Keywords: neurodiversity paradigm, disabilities, counseling, neurodivergence, disability models
According to the American Counseling Association (ACA), “counseling is a professional relationship that empowers diverse individuals, families, and groups to accomplish mental health, wellness, education, and career goals” (Kaplan et al., 2014, p. 92). These ACA priorities are echoed in seminal counseling texts. The Multicultural and Social Justice Counseling Competencies (MSJCC; Ratts et al., 2016) outline the counseling profession as grounded in a culturally affirming, contextual approach to address systemic oppression and intersectionality. The ACA Advocacy Competencies also center context and identities as critical in advocating for systemic change (Toporek & Daniels, 2018). Thus, the counseling profession promotes a strengths-based approach to prevention and mental health, centering equity, social justice, and the use of a critical lens, particularly for those with marginalized intersectional identities (Hays & Singh, 2023; Proctor & Rivera, 2022).
People with disabilities (PWDs) are a historically marginalized identity or culture that includes neurodivergent individuals (Deroche & Mautz, 2024; Long et al., 2024; Roberson et al., 2021). Because of the prevalence of neurodivergence worldwide (15%–20%; Doyle, 2020), allied professions have started incorporating the neurodiversity paradigm into their scholarship, including psychology (Pellicano & den Houting, 2022), occupational therapy (Chen & Patten, 2021; Rajotte et al., 2025), and speech-language pathology (DeThorne & Searsmith, 2021). However, the neurodiversity movement is largely absent from the peer-reviewed counseling literature (Long et al., 2025). In this article, we fill a gap in the literature, noting: (a) a critical counseling lens and the importance of centering marginalized identities, such as PWDs; (b) prominent disability models, including the neurodiversity paradigm; and (c) suggestions to infuse neurodiversity throughout the counseling profession.
Critical Theories
Overall, critical theories are an overarching paradigm centering the importance of recognizing and changing systemic oppression, advocating for historically marginalized identities, and emphasizing the impact of intersectionality (Hays & Singh, 2023; Proctor & Rivera, 2022). First, critical theorists view the world through the socially constructed dimensions of power, privilege, and marginalization, which suggests that power structures in society were historically developed and are presently maintained to provide power and privilege to some and oppress and marginalize others. These power structures will continue unless identified (i.e., increase critical consciousness) and actively changed (i.e., interrogate and dismantle oppressive systems and move toward more equity and justice). For instance, according to critical theories such as feminism and critical race theory (CRT), dominant established power structures, such as patriarchy and colonialism, should be challenged. Overall, critical theorists prioritize historically marginalized voices and strive to ensure that knowledge is rooted in these communities rather than imposed by dominant outsiders (Hays & Singh, 2023; Proctor & Rivera, 2022).
Next, intersectionality is also central to critical theories (Hays & Singh, 2023; Proctor & Rivera, 2022). Introduced by Kimberlé Crenshaw (1989), intersectionality is a framework that examines how overlapping social identities, such as race, gender, class, and disability, interact to create unique experiences of oppression, privilege, and power. Crenshaw introduced the term to address the ways in which Black women, for example, were often excluded from both feminist and anti-racist discourses, revealing how single-axis analyses failed to capture their experiences. Intersectionality does not simply add identities together. Rather, it highlights how these identities interlock within systems of power and shapes how individuals navigate the world. Therefore, intersectionality accentuates how social activism dismantles systems of oppression and injustice.
Critical Theories and Counseling
Drawing from critical theories, the counseling profession works to expose and uproot oppressive systems that reinforce privilege for some identities while suppressing others (Hays & Singh, 2023; Proctor & Rivera, 2022). Ratts et al. (2016) developed the seminal MSJCC, which underscores the need for counselors to engage in intersectional and social justice practices, as well as acknowledges the impact of marginalized and privileged identities within the counselor–client relationship. Similarly, ACA (2025) has reinforced the crucial need for counselors to support marginalized populations because of the prevalence of systemic injustices.
As such, several scholars have discussed the importance of CRT and anti-racism within counseling. Holcomb-McCoy (2022) called for the counseling profession to utilize an anti-racist lens to interrogate and change inequitable systems that disproportionately harm those with marginalized racial/ethnic identities. Similarly, Mayes and Byrd (2022) proposed a framework for anti-racist school counseling emphasizing critical consciousness, evidence-based practices, and strategies to interrupt harmful school policies. Haskins and Singh (2015) recommended pedagogical strategies for incorporating CRT into counseling programs to promote counselor trainees’ racial awareness.
In a similar vein, scholars like Sharma and Hipolito-Delgado (2021) and Locke (2021) reflected on the role of feminist and Latino CRT, respectively, in fostering critical consciousness and anti-racism in counselor training, particularly for students from marginalized groups. LaMantia et al. (2015) also applied feminist pedagogy to counselor education, promoting student ally behaviors. Further, Shavers and Moore (2019) incorporated Black Feminist Thought to explore the experiences of Black female doctoral students at predominantly White institutions.
Finally, several scholars have utilized a critical lens when discussing LGBTQ+ communities. Moe et al. (2020) brought post-colonial theory to the fore in their exploration of working with LGBTQI+ youth internationally by advocating for culturally aware counseling practices that address Eurocentric biases. Also, Moe et al. (2017) applied queer theory to support queer and genderqueer clients through emphasizing the importance of acknowledging intersectional identities and the unique needs of queer people of color. Similarly, Smith (2013) applied critical theory to LGBTQ+ youth in schools and addressed the capability of the American School Counselor Association’s National Model (2025) to reinforce or dismantle heteronormativity practices. Overall, counseling scholars have applied a critical lens (e.g., CRT, anti-racism, feminism, queer theory) to serve several historically marginalized identities. However, a focus on PWDs and critical disability theory (CDT) is absent from this body of critical counseling scholarship.
Disabilities
Those who identify as PWDs are part of one of the largest historically marginalized groups in the United States, with a population of over 70 million (Centers for Disease Control and Prevention [CDC], 2024). Though the construct of disability can be understood in a variety of ways, we utilize the definition from the U.S. Census Bureau (n.d.): “Disability is a complex process between an individual’s physical, emotional, and mental health, and the environment in which they live, work, and play. . . . individuals may experience disability if they have difficulty with certain daily tasks due to a physical, mental, or emotional condition” (p. 1).
In Multicultural and Social Justice Counseling (2024), authors Deroche and Mautz organized disabilities into three primary categories: (a) physical disabilities, such as paralysis, chronic illness, or blindness; (b) cognitive or neurodivergent disabilities, such as learning, developmental, or intellectual disabilities, including autism spectrum disorder or dyslexia; and (c) psychiatric disabilities, including mental health disorders such as anxiety, depression, and substance use, among others. Further, these authors also relayed that disability is an overarching term to represent diverse, varied, intersecting identities and experiences that are shaped by factors such as disability onset, symptom progression and impact, degree of visibility, and disability models.
Disability Models Historically
The construct of disabilities must be understood within its historical context. U.S. society has utilized several models of disability that have evolved over time (Brown, 2015; Deroche & Mautz, 2024; Olkin, 2002). The moral model is one of the oldest and is closely tied to religion; this perspective holds that disabilities are inherently negative and result from one’s lack of faith or as punishment for immoral behaviors (Deroche & Mautz, 2024; Olkin, 2002). The moral model is seen as problematic because it views disabilities adversely and places responsibility on the PWD for their condition, fostering stigma and shame rather than understanding or support.
More recently, disabilities have been conceptualized by two opposing perspectives: the medical model and the social model. Per the medical model, conditions or disorders are classified by the Diagnostic and Statistical Manual of Mental Disorders (DSM; American Psychiatric Association, 2022), and pathologized as impairments or deficits that deviate from a set standard and need to be treated (Brown, 2015; Chen & Patten, 2021; Long et al., 2024; Olkin, 2002). Thus, the medical model recommends that PWDs receive intervention and accommodations to help them operate more closely to a culturally constructed standard of typical. The medical model is currently the most widely utilized disability model, including in the counseling profession. However, this model is critiqued as being deficit-focused and needing greater consideration for both culture and context (Chen & Patten, 2021; Deroche & Mautz, 2024; Olkin, 2002). Further, privileging and encouraging assimilation to a socially constructed norm has been related to adverse mental health for PWDs, such as anxiety and depression from masking or hiding aspects of oneself from others (DeThorne & Searsmith, 2021).
Countering the medical model, the social model considers disability as a social construct, which places the onus on the environment and larger culture, with the aim of removing socially created barriers hindering PWDs from fully accessing societal institutions and spaces (Chen & Patten, 2021; Long et al., 2024; Olkin, 2002). In other words, according to the social model, PWDs are impacted not by their specific disability, but because of how society has structured the world to be unaligned with the unique needs and experiences of PWDs. Scholars have also suggested that the social model is too concrete (Meekosha & Shuttleworth, 2009) and that disabilities must be considered comprehensively, beyond environmental and cultural factors (Dwyer, 2022).
Contemporary Disability Paradigms
Overall, disability models have been shaped by societal beliefs and historical events, evolving with time, as described by Brown (2015) and Deroche and Mautz (2024). Beginning in the mid-1900s, the larger civil rights movement opened doors for federal protections around disabilities and was crucial in securing legal protections and advancing social inclusion for PWDs. Specifically, the disability rights movement initially addressed workplace discrimination, striving for equitable access to employment and work accommodations; this has since progressed to include advocating for more disability inclusive education, health care, and intersectional identities. Hence, the confluence of these factors—evolving disability models, increased civil rights, activism, and centering diversity—have led to the emergence of the present-day neurodiversity paradigm, a contemporary model of disability rooted in critical theories, such as CDT (Brown, 2015; Deroche & Mautz, 2024).
Critical Disability Theory
Expanding upon the social model, CDT explores the broader systems and structures that influence disability (Botha & Gillespie-Lynch, 2022; Hays & Singh, 2023). In alignment with the overarching lens of critical theories, CDT is a framework that challenges previous models of disability to instead espouse the complex experience of PWDs, centering the voices of this marginalized identity or cultural group (Gillies, 2014; Meekosha & Shuttleworth, 2009). Gaining momentum in the 2000s, CDT explores how society constructs, defines, and responds to disabled bodies and minds within the context of systemic power, privilege, and marginalization (Meekosha & Shuttleworth, 2009). Rather than defining disability as abnormal or a medical condition requiring treatment, CDT challenges these prevailing views. Mainly, scholars who subscribe to this paradigm recognize disability as a natural aspect of society, with the need to transform public policies and perceptions, as well as redistribute power, control, and autonomy (Deroche & Mautz, 2024; Long et al., 2024). As such, supporters of CDT advocate to ensure that PWDs can fully participate in all aspects of society such as employment and social and educational dimensions, as well as having equitable access to rights, opportunities, and resources. Thus, the CDT paradigm, grounded in social justice, activism, and the disability rights movement, calls for viewing disability as a unique culture, a dimension of diversity, and through the lens of historically marginalized, intersectional identities or cultures.
The Neurodiversity Movement
While CDT is a critical theory applied toward disabilities, it has also been a driving force in the neurodiversity movement (Roberson et al., 2021). Chapman and Botha (2023) stated:
The neurodiversity movement is a social justice and civil rights movement led by and for people with neurocognitive, developmental, and psychological disabilities. Neurodiversity theory proposes that divergence from expected functioning (such as autism, attention-deficit/hyperactivity disorder [ADHD], developmental coordination disorder, or dyslexia) are natural variations of human minds, and those who diverge from the norm (neurominorities) are equally deserving of dignity, respect, and accommodation. . . . with the acknowledgement of neurocognitive diversity as natural, valuable, and in need of support. (p. 310)
While neurodivergence is considered to be a type of cognitive disability (e.g., autism, ADHD, dyslexia) impacting approximately nearly one in five individuals worldwide (Doyle, 2020), the neurodiversity paradigm is a larger movement rooted in social justice and civil rights, countering earlier deficit-based disability models, such as the medical model (Deroche & Mautz, 2024; Long et al., 2024; Sonuga-Barke & Thapar, 2021). As a result, neurodiversity is seen as a movement or paradigm influenced by CDT, in addition to being a type of disability.
The neurodiversity movement began in the 1990s with sociologist Judy Singer drawing on Crenshaw’s lens of intersectionality (Botha & Gillespie-Lynch, 2022; Chapman, 2021). Though originally conceptualized for autism, this paradigm has since expanded (Chapman, 2021; Dwyer, 2022). Rather than perpetuating a continuum of typical and atypical neurological functioning, the neurodiversity paradigm reinforces normal diversity in human neurology instead of pathologizing neurological variations (Chapman, 2021; Chen & Patten, 2021; Olkin, 2002).
Because it is aligned with critical theories such as CDT (Hays & Singh, 2023; Roberson et al., 2021), neurological diversity should be viewed through the lens of culture (Long et al., 2025), as well as through societal and historical systems of power and oppression. Thus, like other historically marginalized groups (e.g., cultural, ethnic, and sexual minorities; Chapman & Botha, 2023), proponents of the neurodiversity movement describe unique aspects of a shared culture, pride, and identity (Brown, 2015). One such example is identifying as neurominorities (Chapman & Botha, 2023).
For instance, Roberson and colleagues (2021) posited that, historically, neurodivergent individuals have been viewed through an ableist lens that judged them based on their ability to conform to neurotypical standards. A CDT approach denounces this deficit-based historical framing and instead highlights the positive cognitive traits and leadership of neurodivergent individuals. Rather than emphasizing the obstacles they face in meeting conventional norms, CDT and the neurodiversity paradigm redefine neurodivergence as a valuable and distinctive strength and skill set that can be used for enhancement (Roberson et al., 2021).
Furthermore, scholars have examined the confluence of neurodiversity and intersectionality (e.g., Mallipeddi & VanDaalen, 2022). Botha and Gillespie-Lynch (2022) made the case for including the neurodiversity paradigm within the intersectionality conversation, specifically focusing on autistic individuals. Namely, they highlighted the systemic barriers and inequities disproportionately impacting the Autistic community. This includes restricted access to gender-affirming care for autistic transgender people, which can correspond to increased odds of mental health challenges such as depression and suicidality (Tordoff et al., 2022). Furthermore, these risk factors may be compounded when additional identities are incorporated, such as when persons of color are also economically disadvantaged individuals (Botha & Gillespie-Lynch, 2022). Thus, taking an intersectional lens to the neurodiversity paradigm is not only aligned with CDT, but also exemplifies a more nuanced understanding of how multiple layers of identity or culture (e.g., race, gender, socioeconomic status) interact with neurodivergence in order to address the compounded barriers and inequities faced by marginalized groups. As such, intersectionality has been interwoven into CDT to highlight the layered identities and aspects of power, privilege, and oppression within the neurodiversity movement (Botha & Gillespie-Lynch, 2022).
Counseling, Disabilities, and the Neurodiversity Movement
Despite the prevalence of those with disabilities (CDC, 2024), PWDs are often not seen as an underrepresented group or a culture, leading to misconceptions and often a lack of resources and support (Brown, 2015; Olkin, 2002; Pierce, 2024). Within the counseling profession, Degeneffe and colleagues (2021) studied how disability is addressed in ACA’s flagship journal, the Journal of Counseling & Development (JCD). Their results mirrored previous research, noting “limited scope of disability content in JCD . . . [and that] disability is largely neglected in JCD and other counseling-related journals” (Degeneffe et al., 2021, p. 118).
While counseling scholars have focused on critical theories, the literature on CDT is sparse. Öksüz and Brubaker (2020) discussed the historical lens of counseling PWDs and advocated for CDT to shape counseling training. Aligned with CDT, Pierce (2024) outlined the richness of disability culture, recommending that the counseling profession incorporate greater disability justice.
To our knowledge, there has been one peer-reviewed, U.S.-based journal article discussing the neurodiversity paradigm within the counseling profession. Long and colleagues (2025) conducted a qualitative content analysis, examining 21 peer-reviewed counseling journals published between 2013 and 2022. They searched for what they defined as neurodiversity constructs, or content they conceptualized as relating to neurodiversity. Examples of the most frequent terms, or neurodiversity constructs, that they found include autism, ADHD, and twice exceptional, with the most common word/phrase being neurotypical. Thus, while scholars found counseling scholarship demonstrating neurodiversity constructs, these phrases did not include the actual word or a derivative of neurodiversity. Rather, Long et al. (2025) found content more generally related to the construct. These findings underscore the lack of neurodiversity content within counseling. Though the counseling profession centers critical theories with an emerging focus on CDT, the neurodiversity paradigm is absent from the peer-reviewed counseling literature.
Despite the limited counseling scholarship on the neurodiversity paradigm, a different trend exists within allied professions, and scholars have recommended that clinicians utilize the neurodiversity approach in their work (Chapman & Botha, 2023; Sonuga-Barke & Thapar, 2021). Furthermore, the neurodiversity paradigm is being covered in psychology (Pellicano & den Houting, 2022), occupational therapy (Chen & Patten, 2021; Rajotte et al., 2025), and speech-language pathology (DeThorne & Searsmith, 2021). In terms of therapeutic clinicians across disciplines, Sonuga-Barke and Thapar (2021) described the importance of clinicians moving beyond the deficit-based medical model to instead center the perspectives of neurodivergent individuals. Similarly, Chapman and Botha (2023) stated that the need exists for clinical therapeutic approaches to include practical strategies for supporting neurodiversity, including multidisciplinary work across disciplines.
Incorporating the Neurodiversity Movement Into Counseling: A Call to Action
As Long and colleagues (2025) relayed, “counselors across practice settings encounter neurodivergent clients and are responsible for understanding neurodivergence and its impact on client well-being . . . [and] the social, political, and cultural considerations” (p. 57). As approximately 15–20% of the population is neurodivergent (Doyle, 2020), it is likely that counselors will work with this population. As such, counselors must be informed of the neurodiversity paradigm and how to utilize neuro-affirming practices across counseling specialties and the profession as a whole. Next, we provide a call to action, recommending steps for infusing the neurodiversity paradigm throughout the profession: awareness and introspection; guiding documents; professional organizations; research; clinical practice; and pre-service preparation, supervision, and training. It is important to note that these suggestions are preliminary recommendations acting as a springboard for a litany of additional efforts. More depth and focus are warranted across each of the following topics.
Awareness and Introspection
Neuro-affirming counseling begins by looking at the foundational values guiding our profession. In alignment with critical theories (Hays & Singh, 2023; Proctor & Rivera, 2022), the MSJCC (Ratts et al., 2016), and the ACA Advocacy Competencies (Toporek & Daniels, 2018), we must interrogate and dismantle how the counseling profession and greater society privileges certain abilities and neurological existences while oppressing and marginalizing others. This requires both a paradigm shift and heightened critical consciousness as counselors, as a profession, and for the systems we work within (e.g., schools, agencies, private practices, counselor education programs). The following sample questions guide this introspection: How can the counseling profession challenge the historically deficit-laden conceptualization of disabilities that requires assimilating to a socially constructed norm of typicality? How can counselors advocate for systemic changes that increase access and opportunities for all, rather than placing the onus of change primarily on individuals? How can the profession celebrate and affirm the benefits of diverse ability levels and neurological functioning? How are we incorporating intersectionality within neuro-affirming counseling? How are we ensuring that neurodivergent individuals are leading and integral in the application of the neurodiversity movement within the counseling profession? How can we learn from and collaborate with allied professions engaged in neuro-affirming practices?
Guiding Documents
The counseling profession would benefit from integrating the neurodiversity movement into its core frameworks. For example, though ACA Code of Ethics (2014) standards C.5., E.8., and H.5.d. explicitly reference disability, they make no direct mention of neurodiversity. Furthermore, H.5.d. is the only standard that addresses accessibility, and it is within the context of website creation. While this inclusion is valuable, there remains an opportunity to expand considerations of accessibility, flexibility, and inclusivity to better support neurodivergent clients within the counseling relationship.
Next, the MSJCC (Ratts et al., 2016) provides a conceptual framework that highlights ways in which counselors can incorporate advocacy within their work with a range of individuals who experience marginalization. Mainly, competency area III.1. indicates that competent counselors “are aware of how client and counselor worldviews, assumptions, attitudes, values, beliefs, biases, social identities, social group statuses, and experiences with power, privilege, and oppression influence the counseling relationship” (Ratts et al., 2016, p. 9). Overall, the MSJCC is a broad framework designed for application to counselors and clients who identify with a range of identities and cultures, within the context of the many systems that impact them individually and in their interactions with one another. However, as there is no research specifically exploring disability or neurodiversity through the lens of the MSJCC framework, we recommend that disability and neurodiversity should be discussed and investigated as cultural variables.
Like the MSJCC, the ACA’s Advocacy Competencies (Toporek & Daniels, 2018) outline guidelines for advocacy work. These competencies could be expanded to include neurodiversity and disability by addressing ability status as a key contextual factor. Historically, disability and neurodiversity have been omitted from diversity and social justice conversations, often being overlooked as cultural variables. To affect social change, explicit inclusion of these groups or factors is necessary.
Professional Organizations
ACA is the flagship counseling organization, comprised of subgroups, such as divisions representing specialty areas (e.g., substance abuse, veterans, multicultural counseling, child and adolescent counseling). The American Rehabilitation Counseling Association (ARCA) is often viewed as the primary organization relevant to disability within the counseling profession. According to the organization’s website, ARCA is an association of professionals, educators, and students in rehabilitation counseling who are committed to enhancing the well-being of individuals with disabilities. Its goal is to support the growth of PWDs throughout their lives and to advance the quality of the rehabilitation counseling profession (Dunlap, 2024). While the mission is impactful, both the mission and messaging from the organization as a whole often frame disability in terms of rehabilitation or correction. This perspective is discordant with the strengths-based perspective of neurodiversity, affirming the benefits of diverse abilities. Next, we acknowledge ARCA’s commitment to inclusivity and advocacy, which aligns with key principles of the neurodiversity paradigm. However, instead of viewing it as a supplementary task driven by legal requirements, ARCA could benefit from recognizing neurodiversity as an essential aspect of diversity that enriches both the counseling profession and society at large.
Next, the Association for Multicultural Counseling and Development (AMCD; 2025) is the primary organization for multicultural counseling representation within ACA. Notably, the group includes a variety of subgroups (e.g., Native American, Multiracial-Multiethnic, Latinx, International, Asian American-Pacific Islander, African American, Women’s Concerns). Proponents of the disability rights movement, and the neurodiversity movement in particular, consider disabilities and neurodiversity to be both a unique culture with elements of shared identity and a population that represents an element of diversity and multiculturalism (Brown, 2015; Chapman & Botha, 2023). Hence, the AMCD’s mission of connecting, advocating for, and empowering people across multicultural identities makes it ideal for incorporating a neurodiversity or disability subgroup. This is especially fitting as both CDT and the neurodiversity paradigm emphasize intersectionality, wholeness, and cross-movement solidarity as essential to the advocacy and liberation of people with multiple marginalized identities.
Finally, the Association for Counselor Education and Supervision (ACES; 2021) has several interest networks, including Disability Justice and Accessibility in Counseling. This group seems most aligned with the neurodiversity movement because it prioritizes disability justice, intersectionality, and anti-oppression, and addresses neurodiversity. However, as ACES serves counselor education and supervision, additional counseling organizations can share this focus.
Research
Future research in counseling must intentionally center neurodivergent individuals and their lived experiences with attention to affirming and identity-conscious practices. This research should focus not only on clients, but also on neurodivergent counselors, supervisors, leaders, graduate students, and scholars. Scholars have increasingly called for more rigorous research within counseling and related clinical professions (Botha & Gillespie-Lynch, 2022; Dwyer, 2022; Long et al., 2025), yet the counseling profession continues to lag in fully integrating neuro-affirming approaches. A promising starting point is the development of a conceptual theoretical framework for neuro-affirming counseling, which can be tailored to specific counseling specialty areas. Grounded theory, rooted in the voices and narratives of neurodivergent individuals, may serve as a powerful methodology to generate such a framework. Follow-up studies could include Delphi panels with expert practitioners and neurodivergent partners; concept mapping to refine theoretical constructs; and the development and validation of instruments to assess counselor competence and client outcomes. In addition, researchers should explore the lived experiences of neurodivergent individuals across various counseling settings to better understand barriers to care, perceptions of counselor responsiveness, and markers of affirming practice.
Participatory action research and other inclusive methods should be prioritized to ensure that research is not only about neurodivergent communities but is created with them. Lastly, as the MSJCC offers a meaningful lens through which to examine how counselors engage with clients who identify as neurodivergent and/or PWDs, researchers could explore how the MSJCC framework supports (or falls short in) guiding counselors’ development of awareness, knowledge, and skills in working with this population. These research directions offer rich, essential opportunities to bridge gaps in the literature and advance counseling equity.
Clinical Practice
In alignment with the ACA Code of Ethics (2014), which emphasizes honoring diversity and embracing a multicultural approach, practicing counselors must recognize neurodiversity as a vital aspect of human diversity. As Long et al. (2025) noted, this has historically been overlooked in multicultural counseling, despite the growing advocacy of the neurodiversity movement. Clinicians are called to adopt a neuro-affirming framework that acknowledges and respects neurological differences as natural human variations rather than deficits. This approach aligns with ethical principles of dignity, potential, and uniqueness, and encourages counselors to critically examine their own biases, clinical language, and treatment paradigms. Counselors should broach the topic of neurodivergence with clients when appropriate; tailor treatment planning to reflect clients’ sensory, communication, and identity needs; and shift from symptom-reduction models to those centered in self-advocacy, autonomy, and strengths.
Meaningful application of a neuro-affirming approach requires attention to all stages of the clinical process, from treatment to diagnosis, as well as to the cultural identities and needs of each counselor and client both independently and within the counseling relationship. Counselors should assess how the physical space, documentation practices, and session structures either promote or inhibit accessibility and inclusion. For example, using flexible communication methods or creating low sensory environments may significantly improve comfort and therapeutic rapport. These shifts are especially important given that many counselors practice in systems governed by the medical model (e.g., DSM-driven environments), which can conflict with neuro-affirming values. Clinicians must grapple with this tension, asking: Can we hold space for both DSM-informed practice and neuro-affirming care? Though diagnoses may be necessary for access to care, counselors have an ethical responsibility to advocate for affirming practices, consult with allied professionals, and frame client experiences in ways that empower rather than pathologize. Ultimately, neuro-affirming counseling must be rooted in intersectionality, accessibility, and cultural humility, core values of an inclusive, socially just counseling practice.
Pre-Service Preparation, Supervision, and Training
Counselor preparation plays a critical role in shaping how future professionals engage with neurodivergent individuals. However, current training models often fall short in addressing this population through an affirming, socially just lens. Although the Council for the Accreditation of Counseling and Related Educational Programs (CACREP; 2023) sets the standards for counselor education, its integration of disability, and more specifically, neurodiversity, remains limited and inconsistent. For example, though Standard 3.A.4. encourages the removal of systemic, institutional, architectural, and attitudinal barriers that hinder equity and access, it does not explicitly frame neurodiversity as an element of human diversity. Additionally, Section 3.B., which focuses on social and cultural identities and experiences, omits reference to neurodivergence, disability culture, and ability status as meaningful sociocultural identities. This exclusion reinforces a medicalized view of disability and misses the opportunity to promote a strengths-based, identity-affirming framework that aligns with the neurodiversity paradigm.
To address these gaps, counselor education programs should intentionally integrate disability and neurodiversity content across the curriculum. Courses such as human development, multicultural counseling, ethics, and diagnosis can provide students with information about the neurodiversity movement and CDT, as well as suggest counseling strategies that are strengths-based, utilize a critical systemic lens, and acknowledge disabilities as unique cultural identities. Supervision and training for practicing counselors should do the same by utilizing a neuro-affirming approach and encouraging critical reflection on ableism, diagnostic language, and counselor attitudes toward disability. Moreover, the MSJCC can serve as a guiding framework for both counselor education and clinical supervision to teach awareness, knowledge, skills, and advocacy specific to neurodivergent clients and normalize the perspectives of neurodivergent counseling professionals. Infusing disability culture and neurodiversity into preparation, supervision, and training not only equips pre-service and practicing counselors with the tools to work competently and compassionately but also creates space for neurodivergent individuals within the profession to thrive as students, educators, supervisors, clinicians, and leaders.
Conclusion
According to Kaplan and colleagues (2014), counseling organizations and leaders have come together to clarify a shared professional identity: to strengthen the profession and ensure high-quality practices toward those we serve. The counseling profession has a history of evolving, changing, and improving, incorporating knowledge and new trends as they develop. The neurodiversity paradigm has been increasingly discussed across society, such as in allied professions like psychology (Pellicano & den Houting, 2022). The counseling profession must also evolve to stay relevant. This includes expanding the profession to integrate the neurodiversity paradigm and neuro-affirming practices. Utilizing and embracing neurodiversity in counseling strengthens the profession by better equipping scholars, practitioners, leaders, supervisors, and professional organizations. Incorporating a neuro-affirming lens also contributes to a societal shift of increasing awareness, reducing stigma, and advocating for systemic change, particularly for identities who have been historically marginalized. These are fundamental goals at the root of both the neurodiversity movement and the counseling profession.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
American Counseling Association. (2014). ACA code of ethics. https://bit.ly/acacodeofethics
American Counseling Association. (2025). Working with marginalized communities. https://www.counseling.org/resources/topics/special-considerations/marginalized-communities
American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). https://doi.org/10.1176/appi.books.9780890425787
American School Counselor Association. (2025). ASCA National Model. https://bit.ly/ASCANationalModel
Association for Counselor Education and Supervision. (2021). ACES interest networks. https://acesonline.net/interest-networks
Association for Multicultural Counseling and Development. (2025). Why AMCD? https://www.myamcd.org/about
Botha, M., & Gillespie-Lynch, K. (2022). Come as you are: Examining Autistic identity development and the neurodiversity movement through an intersectional lens. Human Development, 66(2), 93–112. https://doi.org/10.1159/000524123
Brown, S. E. (2015). Disability culture and the ADA. Disability Studies Quarterly, 35(3). https://doi.org/10.18061/dsq.v35i3.4936
Centers for Disease Control and Prevention. (2024). CDC data shows over 70 million U.S. adults reported having a disability. http://cdc.gov/media/releases/2024/s0716-Adult-disability.html
Chapman, R. (2021). Neurodiversity and the social ecology of mental functions. Perspectives on Psychological Science, 16(6), 1360–1372. https://doi.org/10.1177/1745691620959833
Chapman, R., & Botha, M. (2023). Neurodivergence-informed therapy. Developmental Medicine & Child Neurology, 65(3), 310–317. https://doi.org/10.1111/dmcn.15384
Chen, Y.-L., & Patten, K. (2021). Shifting focus from impairment to inclusion: Expanding occupational therapy for neurodivergent students to address school environments. The American Journal of Occupational Therapy, 75(3), 1–7. https://doi.org/10.5014/ajot.2020.040618
Council for the Accreditation of Counseling and Related Educational Programs. (2023). 2024 standards. https://www.cacrep.org/for-programs/2024-cacrep-standards
Crenshaw, K. (1989). Demarginalizing the intersection of race and sex: A Black feminist critique of antidiscrimination doctrine, feminist theory and antiracist politics. University of Chicago Legal Forum, 1989(1), 139–167. https://chicagounbound.uchicago.edu/cgi/viewcontent.cgi?article=1052&context=uclf
Degeneffe, C. E., Doty, H., Martinez, R., Ncube, N., & Nguyen, N. (2021). Disability content in the Journal of Counseling & Development and Social Work: A comparative analysis. Rehabilitation Counseling Bulletin, 66(2), 112–122. https://doi.org/10.1177/00343552211063245
Deroche, M. D., & Mautz, E. K. (2024). Disability and ableism. In J. M. Cook & M. Clark (Eds.), Multicultural & social justice counseling (pp. 292–322). Cognella.
DeThorne, L. S., & Searsmith, K. (2021). Autism and neurodiversity: Addressing concerns and offering implications for the school-based speech-language pathologist. Perspectives of the ASHA Special Interest Groups, 6(1), 184–190. https://doi.org/10.1044/2020_PERSP-20-00188
Doyle, N. (2020). Neurodiversity at work: A biopsychosocial model and the impact on working adults. British Medical Bulletin, 135(1), 108–125. https://doi.org/10.1093/bmb/ldaa021
Dunlap, P. (2024). From the president. American Rehabilitation Counseling Association. https://web.archive.org/web/20250426051651/https://arcaweb.org/from-the-president
Dwyer, P. (2022). The neurodiversity approach(es): What are they and what do they mean for researchers? Human Development, 66(2), 73–92. https://doi.org/10.1159/000523723
Gillies, J. (2014). Critical disability theory. In A. C. Michalos (Ed.), Encyclopedia of quality of life and well-being research (1st ed.; pp. 1348–1350). Springer.
Haskins, N. H., & Singh, A. (2015). Critical race theory and counselor education pedagogy: Creating equitable training. Counselor Education and Supervision, 54(4), 288–301. https://doi.org/10.1002/ceas.12027
Hays, D. G., & Singh, A. A. (2023). Qualitative research in education and social sciences (2nd ed). Cognella.
Holcomb-McCoy, C. (Ed.). (2022). Antiracist counseling in schools and communities. American Counseling Association.
Kaplan, D. M., Tarvydas, V. M., & Gladding, S. T. (2014). 20/20: A vision for the future of counseling: The new consensus definition of counseling. Journal of Counseling & Development, 92(3), 366–372. https://doi.org/10.1002/j.1556-6676.2014.00164.x
LaMantia, K., Wagner, H., & Bohecker, L. (2015). Ally development through feminist pedagogy: A systemic focus on intersectionality. Journal of LGBT Issues in Counseling, 9(2), 136–153. https://doi.org/10.1080/15538605.2015.1029205
Locke, A. F. (2021). Surviving the rollercoaster: The professional identity development of Latinx doctoral students in counseling. Journal of Counselor Preparation and Supervision, 14(2), 1–28. https://research.library.kutztown.edu/jcps/vol14/iss2/9
Long, S. M., Clark, M., Ausloos, C. D., Paul, D., & Finch, K. (2025). A content analysis of neurodiversity constructs in counseling journals. Journal of Mental Health Counseling, 47(1), 56–73. https://doi.org/10.17744/mehc.47.1.04
Long, S. M., Rio, J., & Forristal, K. M. (2024). Emerging topics in diversity. In J. M. Cook & M. Clark (Eds.), Multicultural & social justice counseling: A systemic, person-centered, and ethical approach (pp. 448–477). Cognella.
Mallipeddi, N. V., & VanDaalen, R. A. (2022). Intersectionality within critical Autism studies: A narrative review. Autism in Adulthood, 4(4), 281–289. https://doi.org/10.1089/aut.2021.0014
Mayes, R. D., & Byrd, J. A. (2022). An antiracist framework for evidence-informed school counseling practice. Professional School Counseling, 26(1a). https://doi.org/10.1177/2156759X221086740
Meekosha, H., & Shuttleworth, R. (2009). What’s so “critical” about critical disability studies? Australian Journal of Human Rights, 15(1), 47–75. https://doi.org/10.1080/1323238X.2009.11910861
Moe, J., Bower, J., & Clark, M. (2017). Counseling queer and genderqueer clients. In M. M. Ginicola, C. Smith, & J. M. Filmore (Eds.), Affirmative counseling with LGBTQI+ people (pp. 213–226). https://doi.org/10.1002/9781119375517.ch15
Moe, J., Carlisle, K., Augustine, B., & Pearce, J. (2020). De-colonizing international counseling for LGBTQ youth. Journal of LGBT Issues in Counseling, 14(2), 153–169. https://doi.org/10.1080/15538605.2020.1753625
Öksüz, E. E., & Brubaker, M. D. (2020). Deconstructing disability training in counseling: A critical examination and call to the profession. Journal of Counselor Leadership and Advocacy, 7(2), 163–175. https://doi.org/10.1080/2326716X.2020.1820407
Olkin, R. (2002). Could you hold the door for me? Including disability in diversity. Cultural Diversity and Ethnic Minority Psychology, 8(2), 130–137. https://doi.org/10.1037/1099-9809.8.2.130
Pellicano, E., & den Houting, J. (2022). Annual research review: Shifting from “normal science” to neurodiversity in autism science. Journal of Child Psychology and Psychiatry, 63(4), 381–396. https://doi.org/10.1111/jcpp.13534
Pierce, K. L. (2024). Bridging the gap between intentions and impact: Understanding disability culture to support disability justice. The Professional Counselor, 13(4), 486–495. https://doi.org/10.15241/klp.13.4.486
Proctor, S. L., & Rivera, D. P. (Eds). (2022). Critical theories for school psychology and counseling: A foundation for equity and inclusion in school-based practice. Routledge.
Rajotte, E., Grandisson, M., Couture, M. M., Desmarais, C., Chrétien-Vincent, M., Godin, J., & Thomas, N. (2025). A neuroinclusive school model: Focus on the school, not on the child. Journal of Occupational Therapy, Schools, & Early Intervention, 18(2), 281–299. https://doi.org/10.1080/19411243.2024.2341643
Ratts, M. J., Singh, A. A., Nassar-McMillan, S., Butler, S. K., & McCullough, J. R. (2016). Multicultural and social justice counseling competencies: Guidelines for the counseling profession. Journal of Multicultural Counseling and Development, 44(1), 28–48.
Roberson, Q., Quigley, N. R., Vickers, K., & Bruck, I. (2021). Reconceptualizing leadership from a neurodiverse perspective. Group & Organization Management, 46(2), 399–423. https://doi.org/10.1177/1059601120987293
Sharma, J. & Hipolito-Delgado, C. P. (2021). Promoting anti-racism and critical consciousness through a critical counseling theories course. Teaching and Supervision in Counseling, 3(2), 1–12. https://doi.org/10.7290/tsc030203
Shavers, M. C., & Moore, J. L. (2019). The perpetual outsider: Voices of Black women pursuing doctoral degrees at predominantly White institutions. Journal of Multicultural Counseling and Development, 47(4), 210–226. https://doi.org/10.1002/jmcd.12154
Smith, L. C. (2013). How the ASCA National Model promotes and inhibits safe schools for queer youth: An inquiry using critical theory. Journal of LGBT Issues in Counseling, 7(4), 339–354. https://doi.org/10.1080/15538605.2013.839340
Sonuga-Barke, E., & Thapar, A. (2021). The neurodiversity concept: Is it helpful for clinicians and scientists? The Lancet Psychiatry, 8(7), 559–561. https://doi.org/10.1016/S2215-0366(21)00167-X
Toporek, R. L., & Daniels, J. (2018). American Counseling Association advocacy competencies: Updated. https://www.counseling.org/docs/default-source/competencies/aca-advocacy-competencies-updated-may-2020.pdf?sfvrsn=f410212c_4
Tordoff, D. M., Wanta, J. W., Collin, A., Stepney, C., Inwards-Breland, D. J., & Ahrens, K. (2022). Mental health outcomes in transgender and nonbinary youths receiving gender-affirming care. JAMA Network Open, 5(2), 1–13. https://doi.org/10.1001/jamanetworkopen.2022.0978
U.S. Census Bureau. (n.d.). Disability. https://www.census.gov/data/academy/resources/one-pagers/disability.html
Apr 1, 2026 | Volume 16 - Issue 1
Priscilla Rose Prasath, Devon E. Romero, Claudia G. Interiano-Shiverdecker, John J. S. Harrichand, Leslie Citlalli Garza Mendoza
This study explores the phenomenon of post-traumatic growth (PTG) among survivors of sex trafficking in the United States using a transcendental phenomenological approach. Through in-depth interviews with 10 survivors, the study illuminates the essence of PTG as experienced by participants, emphasizing personal and contextual factors that supported their change. Bracketing was used to reduce researcher bias, allowing the voices and meanings of participants to guide the analysis. Findings highlight two broad themes: internal agency driving change and external factors promoting change. The study offers implications for trauma-informed support and survivor-centered counseling interventions.
Keywords: post-traumatic growth, sex trafficking, internal agency, trauma-informed support, counseling interventions
Post-traumatic growth (PTG) is the positive psychological change following the struggle with traumatic or highly challenging life circumstances (Tedeschi et al., 2018). Tedeschi and Calhoun (2004) argued that trauma is defined not by the event itself but by its effect on an individual’s core schemas or worldview, which may require reconstruction in order to integrate the traumatic experience. PTG’s framework allows us to understand the growth individuals may undergo after trauma (Tedeschi & Calhoun, 1995). This change results in new ways of thinking, feeling, and behaving that move beyond the trauma rather than returning to baseline functioning (Tedeschi & Calhoun, 1995). These long-term changes often emerge through deliberate reflection, not immediate reactions (Tedeschi et al., 2018). PTG is seen as an “ongoing process” rather than a “static outcome” (Tedeschi & Calhoun, 2004, p. 1).
Domains and Factors that Promote PTG
Researchers have identified five domains of PTG: personal strength, close relationships, new possibilities, greater appreciation of life, and spiritual development (Tedeschi & Calhoun, 1995). These domains reflect positive changes following trauma. Personal strength includes enhanced self-reliance, increased fortitude, and a shift from seeing oneself as a “victim” to a “survivor” (Tedeschi et al., 2018, p. 27). Close relationships involve greater compassion, openness to help, and deeper connections (Tedeschi & Calhoun, 2004). New possibilities refer to recognizing new life opportunities, such as changes in interests or careers. Greater appreciation of life includes valuing things once taken for granted. Spiritual development entails changes in beliefs and reflections on life’s meaning (Tedeschi et al., 2018).
PTG may arise after major life crises, often following struggles to cope, though not always immediately (Tedeschi & Calhoun, 1995, 2004). It is important to note that PTG is not an automatic or inevitable outcome of trauma. Tedeschi and Calhoun (2004) emphasized that PTG involves an additional cognitive and emotional burden placed on survivors, who must grapple with the disruption of core schemas in order to reconstruct meaning. In other words, although trauma may create the potential for growth, survivors must actively engage in processes of reflection, sense-making, and struggle for PTG to occur (Tedeschi et al., 2018). Clarifying this distinction helps underscore that PTG requires effortful engagement beyond merely surviving or adapting. Although unplanned and unexpected, certain interventions can support PTG (Tedeschi et al., 2018). Contributing factors include cognitive processing, positive reappraisal, personality traits, trauma characteristics, individual differences, and social support (Henson et al., 2021). Coping strategies such as problem-solving, emotion regulation, forgiveness, religiosity, and spirituality have also been linked to PTG (Park, 2010; Schultz et al., 2020).
PTG in Individuals With Experiences of Sex Trafficking
Sex trafficking is defined as “the recruitment, harboring, transportation, provision, or obtaining of a person for the purpose of a commercial sex act” (Victims of Trafficking and Violence Protection Act of 2000, § 103). Survivors often experience trauma and symptoms of post-traumatic stress disorder. PTG may begin when individuals gain the strength to leave trafficking situations and reclaim control of their lives. Current peer-reviewed literature on PTG among sex trafficking survivors remains limited. Schultz et al. (2020) examined PTG and religious coping, finding that education and faith contributed to hope and resilience. However, their focus on scales and structured reflections did not capture the phenomenological essence of survivor-defined growth. Our study extends this work using a transcendental phenomenological approach, centering survivors’ voices and allowing meaning to emerge from their narratives of change, agency, and empowerment.
Highlighting survivor-defined PTG is important for the counseling profession because it provides a more authentic and nuanced understanding of how growth is experienced by individuals who have endured extreme trauma. Much of the existing counseling literature has conceptualized PTG through researcher-defined domains or standardized measures, which risks overlooking survivor-specific meanings and contexts (Zoellner & Maercker, 2006). By privileging survivor voices, counselors can gain insight into culturally and contextually grounded processes of growth, which informs more effective trauma-informed and strengths-based interventions (Hays & Singh, 2023). This perspective also contributes to the counseling profession’s ethical responsibility to amplify marginalized voices and to design interventions that align with survivors’ lived realities, rather than imposing externally constructed frameworks (Herman, 1997).
In extending this focus, we emphasize survivor-constructed understanding and the process of becoming, rather than solely coping or recovery, filling a gap in the literature. We also distinguish PTG from resilience, defined as the capacity to bounce back to pre-trauma functioning, and from healing, defined as the restoration of well-being, by focusing on psychological and existential growth beyond pre-trauma functioning (Tedeschi & Calhoun, 2004). Although resilience emphasizes adaptation and returning to prior levels of functioning after adversity, and healing involves the restoration of well-being, PTG reflects growth that surpasses baseline functioning (Zoellner & Maercker, 2006). In this study, instances in which growth was described as moving beyond survival or recovery into a redefined sense of identity and purpose were notated as PTG experiences. This framing underscores that PTG is not synonymous with resilience or healing but represents a qualitatively distinct process of change. This survivor-centered perspective contributes to the PTG and sex trafficking discourse, capturing survivor-defined growth that emerges not only from overcoming adversity but also from redefining oneself after exploitation.
Purpose of the Study and Research Question
This study explores the lived experiences of PTG among survivors of sex trafficking in the United States using a transcendental phenomenological approach. By centering survivor voices, it seeks to understand how individuals make meaning of growth after exiting trafficking. This inquiry contributes to academic understanding and offers practical implications for trauma-informed, strengths-based interventions. The guiding research question was: How do survivors of sex trafficking in the United States describe their experiences of PTG?
Methods
Research Design
This study employed transcendental phenomenology to explore how survivors of sex trafficking make sense of their PTG (Moustakas, 1994). Transcendental phenomenology focuses on describing the essence of a phenomenon as experienced by individuals, by setting aside or bracketing the researchers’ own assumptions and biases. Through systematic reduction and imaginative variation, we aimed to identify the core meanings of PTG within participants’ lived experiences. This approach was chosen to allow rich, first-person accounts of healing and growth to emerge, with the research team taking deliberate steps to bracket preconceptions.
Transcendental phenomenology was selected because it emphasizes the description of the universal essence of a phenomenon through the lived experiences of individuals while intentionally setting aside researcher assumptions (Moustakas, 1994). This design aligns with our purpose of privileging survivors’ voices and minimizing interpretive bias, which is particularly important in research involving historically marginalized populations (Hays & Singh, 2023). Compared to interpretive phenomenology, which centers the researcher’s interpretation, transcendental phenomenology places greater weight on participants’ meaning-making, making it well-suited for capturing survivor-defined PTG. This methodology also aligns with the counseling profession’s emphasis on client-centered and strengths-based approaches.
Researcher Positionality
While transcendental phenomenology requires the bracketing of researcher assumptions, we also provide positionality statements to enhance transparency. We engaged in ongoing reflexivity, journaling, and bracketing discussions throughout data collection and analysis. These efforts helped us remain attuned to participants’ meanings and reduce potential bias. Hays and Singh (2023) considered subjectivity statements crucial to inform readers about the context and process of qualitative research. Priscilla Rose Prasath (cisgender female, Asian Indian), Devon E. Romero (cisgender female, biracial), Claudia G. Interiano-Shiverdecker (cisgender female, Latina), and John J. S. Harrichand (cisgender male, biracial/Asian) are current university counselor educators with numerous publications, presentations, and training given to counselors-in-training and professional counselors on sex trafficking. Prasath primarily studies positive psychological constructs such as PTG from a strengths-based perspective. Prasath, Romero, Interiano-Shiverdecker, and Harrichand all hold a license as a Licensed Professional Counselor (LPC); Harrichand also holds an LPC-S. They have a combined 20+ years of clinical experience working with diverse clientele and in a variety of settings. Leslie Citlalli Garza Mendoza (cisgender female, Latina) is currently enrolled as a doctoral student at the same university as Prasath, Romero, and Interiano-Shiverdecker. Having conducted prior research on sex trafficking experiences, we approached this study with certain preconceptions. We anticipated that the findings would align with those of other trauma victims in the existing literature. However, our previous work led us to consider the possibility that PTG may manifest in more areas than the traditionally recognized five PTG domains.
Participants and Sampling
Ten participants were selected using purposive sampling, having lived experience of post-trauma growth following sex trafficking, consistent with phenomenological methods (Moustakas, 1994). PTG was intentionally not an explicit inclusion criterion because one of the central aims of this study was to explore how survivors themselves describe growth following trauma without imposing a predetermined definition of PTG. By not requiring participants to self-identify with the concept of PTG, we were able to capture survivor-constructed understandings of growth, which is consistent with transcendental phenomenology’s emphasis on allowing meaning to emerge from participants’ voices (Moustakas, 1994). Survivors were invited to share their experiences of positive changes and post-trafficking healing, and PTG was identified through analysis when participants described growth beyond baseline functioning. This approach aligns with calls in the literature to privilege survivor perspectives and to avoid constraining data collection to researcher-driven constructs (Hays & Singh, 2023).
With regard to participants’ characteristics, ages ranged from 30 to 42 (M = 36.7, Mdn = 38.5, SD = 5.1). Most participants were White (n = 8), with one American Indian or Alaskan Native participant and one Black participant. Nine were U.S.-born; one was an immigrant residing in the United States for 4 years. Educational attainment ranged from secondary school to graduate school. Marital status included single (n = 3), married (n = 1), separated (n = 2), and divorced (n = 4). To provide additional context, participant demographic information is summarized in Table 1.
Table 1
Survivor Demographics
| Survivor |
Age |
Gender |
Race / Ethnicity |
Marital Status |
Education |
| Annabel |
37 |
Female |
White |
Divorced |
Graduate School |
| Betty |
30 |
Female |
White |
Single |
Graduate School |
| Cassie |
41 |
Female |
White |
Divorced |
College |
| Crystal |
42 |
Female |
American Indian or
Alaskan Native |
Separated |
Some College |
| Gretchen |
30 |
Female |
White |
Divorced |
Some Graduate School |
| Jennifer |
32 |
Female |
White |
Separated |
College |
| Jes |
42 |
Female |
White |
Married |
10th Grade; GED |
| Mia |
41 |
Female |
White |
Single |
Secondary School |
| Monica |
32 |
Female |
White |
Divorced |
College |
| Niki |
40 |
Female |
Black |
Single |
Graduate School |
Note. GED = General Educational Development; age in years.
Data Collection Procedures
After receiving IRB approval from the university, we sought participants through purposeful sampling. Interview questions were developed following Moustakas’ (1994) recommendations for phenomenological research, using open-ended, broad questions that allowed participants to reflect deeply on their lived experiences. To minimize bias, Prasath conducted bracketing activities before and throughout the data collection. Interviews were audio-recorded, transcribed, and reviewed for accuracy.
Inclusion and Recruitment
Participants were required to be sex trafficking survivors over the age of 18. Recruitment began in early 2022. Initially, we reached out to professional networks and advocacy contacts known to members of the research team, including colleagues who had previously collaborated with survivor leaders or anti-trafficking initiatives. This initially yielded one volunteer, but after 2 months, additional participants could not be reached through these connections.
Consequently, we broadened recruitment to additional purposeful sampling strategies. Rather than working exclusively through organizations or mental health professionals, which may have limited access to survivors who publicly self-identify, we directly contacted individuals who had already chosen to share their survivorship openly via social media platforms such as TikTok, Instagram, and Twitter. This strategy aligned with our goal of centering survivor-defined PTG and ensured we recruited participants who were willing to narrate their experiences in their own terms. Through these efforts, nine more individuals volunteered within 2 months. Interested participants completed consent forms, a demographic form, and a one-time Zoom interview. To protect confidentiality, all references to organizations, programs, or initiatives were generalized, and identifying details were removed. Any names used in reporting were pseudonyms chosen by the research team to further protect anonymity. Participants received a $20 gift card for their involvement. Data collection concluded in May 2022.
Interview Protocol Development
The interview questions were developed through an iterative process informed by both the research design and existing scholarship on PTG. We reviewed foundational literature on PTG domains (Tedeschi & Calhoun, 2004) as well as recent studies examining growth among trauma-affected populations (e.g., Schultz et al., 2020). This ensured our protocol included questions that tapped into constructs previously studied, such as changes in relationships, new possibilities, personal strength, and spirituality, while also leaving space for survivor-defined meanings to emerge. Additionally, members of the research team drew on our clinical expertise counseling individuals with trauma histories to ensure that the questions were phrased sensitively and reduced the risk of retraumatization. The resulting semi-structured protocol balanced theoretical grounding with clinical appropriateness, consistent with Smith et al.’s (2009) recommendations for qualitative interviewing.
Interview Content and Process
Harrichand, a counselor educator with expertise in qualitative inquiry and a Certified Clinical Trauma Professional, conducted the interviews. The semi-structured format began with broad, non-threatening prompts (e.g., “Please tell me a little about yourself and your background”) before progressing to more specific questions about change, coping, and growth after trafficking. Questions included: “What do you think are the most common challenges that survivors experience after their sex trafficking experience?”; “Tell me about the person you are today—how does this person compare to who you were before?”; “What helped you overcome the impact of sex trafficking?”; “Were there services or resources that were helpful to you?”; “What is important for counselors to know when working with sex trafficking survivors?”; and “What is important about your experience that I haven’t asked you and you haven’t had the chance to tell me?” This progression followed Smith et al.’s (2009) emphasis on beginning with general questions before moving to potentially sensitive areas. Interviews were conducted with sensitivity and empathy, using counseling skills such as reflections, minimal encouragers, and attending behaviors to facilitate conversation. Interviews ranged from 41 to 145 minutes (M = 80.9), allowing for in-depth exploration of each participant’s lived experience.
Data Analysis
Data analysis followed Moustakas’ (1994) transcendental phenomenological method. We began with epoché, or bracketing, to set aside preconceptions related to trauma and PTG. Prasath and Mendoza independently immersed themselves in the data by reading and re-reading interview transcripts. We conducted horizontalization by first treating all statements as equally valuable. From this pool, we then identified significant statements, defined as those that directly illuminated participants’ experiences of PTG, for further clustering into meaning units. Weekly meetings were held over a semester to review notes and merge coding. Mendoza conducted initial coding, followed by Prasath’s independent coding.
The coding process focused solely on identifying PTG, defined as growth beyond baseline functioning and recovery. Statements that reflected only symptom relief or a return to prior levels of functioning were not coded as PTG. In contrast, when participants described new perspectives, redefined identity, or discovery of new possibilities, these were categorized as PTG. Ambiguous expressions, such as “I am happy,” were coded as PTG only when participants explicitly tied such expressions to broader meaning-making or identity shifts. Coding judgments were discussed in team debriefings to ensure consistency and credibility.
Through imaginative variation, we then explored how context shaped meaning. Textural descriptions (what was experienced) and structural descriptions (how it was experienced) were synthesized into a composite narrative. For example, even when not directly prompted, participants’ accounts revealed structural descriptions of PTG as integral to their lived experiences.
Strategies of Trustworthiness
To ensure rigor, we followed Moustakas’ (1994) guidelines and qualitative research best practices (Hays & Singh, 2023). Prasath and Mendoza maintained bracketing journals and engaged in regular reflexive dialogues to manage assumptions. Researcher triangulation was achieved through independent coding by team members from varied professional backgrounds, followed by collaborative debriefings to reach consensus. To strengthen credibility, we conducted peer debriefings and obtained an external audit by a qualitative research expert. Member checking was limited to transcript verification to remain consistent with phenomenological principles. An audit trail was maintained, and thick, descriptive narratives supported by direct quotations enhanced transferability and confirmability.
Results
We categorized the experiences of participants into two broad themes: Internal Agency Driving Change and External Factors Promoting Change (see Table 2).
Table 2
Themes and Subthemes
| Experiences of PTG |
Themes |
Subthemes |
Internal Agency
Driving Change |
Personal Strengths Resources |
· Warrior and survivor mindset
· Self-awareness
· Confidence
· Forgiveness |
| Finding Meaning in the Everyday |
· Acceptance and gratitude
· Positive reframed perspective toward life and self |
| Creating Paths Forward |
· Pursuing new career path as an advocacy agent
· Entrepreneurial mindset
· Educating and training others
· Empowering other survivors |
| Spiritual Grounding and Rediscovery |
· Meaning-making of experiences
· Faith as a healing pathway
· Transition to spirituality or redefining spiritual identity |
| Past Survival Mechanisms Evolving Into Coping Strategies |
· Acceptance coping
· Skilled crisis management
· Dissociation
· Substance coping
· Avoidance coping |
External Factors
Promoting Change |
Close Relationships |
· Navigating trust and vulnerability
· Balancing isolation and connection
· Survivor-led peer support |
Supportive Resources
and Services |
· Access to basic needs
· Trauma-informed resources and programs
· Survivor-led initiatives
· Barriers to access |
| Counseling Experiences and Alternative Paths to Healing |
· Counselor characteristics—knowledge, skills, dispositions, and practices
· Importance of tailored counseling approaches
· Multidisciplinary trauma-informed teams
· Alternative therapeutic modalities
· Support groups |
Internal Agency Driving Change
Within the theme Internal Agency Driving Change, most participants identified the following five areas: Personal Strengths Resources, Finding Meaning in the Everyday, Creating Paths Forward, Spiritual Grounding and Rediscovery, and Past Survival Mechanisms Evolving Into Coping Strategies. To illustrate how they manifested in survivors of sex trafficking, we coupled each subtheme with representative quotes.
Personal Strengths Resources—“A Warrior and Survivor Mindset”
All 10 participants shared the subtheme of Personal Strengths Resources, including confidence, forgiveness, self-awareness, and developing a warrior and survivor mindset. Many described reclaiming their confidence, learning self-forgiveness, enhancing their intuition for protection, and embracing a resilient mindset, with Monica summing up this subtheme by expressing, “I’m a survivor and a warrior first.” Niki shared the process of relearning that she “cannot control the actions of other[s] . . . but I can control what I can do to make myself safe to move on with my life . . . I can act—advocate for myself . . . giv[e] myself that space.” Six participants expressed confidence in their narratives—which was taken from them while being trafficked. Participants shared, “I like myself now,” “I’m happy,” and “I’m way more confident.”
Four of the participants described their capacity to participate in forgiveness of self and others even after their experiences of sex trafficking. Annabel shared, “I guess my capacity to empathize with people who were like <laughing> doing awful stuff to me . . . I guess is endearing . . . an internal quality.” Monica noted that her healing journey involved forgiveness and “being compassionate again.” She explained, “The hardest action we have to take for ourselves and our mental state is forgiving those who trafficked us. . . . only then I feel like we can actually start forgiving ourselves and that’s been a really difficult piece.” She added, “I have forgiven myself.”
Like intuition, nine participants expressed increased self-awareness following their life of sex trafficking. Cassie reflected, “I’ve had to really kind of figure things out on my own.” She noted that self-awareness allows her to be present in the life she is living today. While Monica expressed that she is “finding her identity . . . doing everything for me authentically. . . . it’s releasing all that, it’s fully taking down that mask and being authentic . . . feeling emotion again.” Seven participants highlighted traits such as intelligence and resilience. Mia also emphasized the importance of stubbornness in her journey to healing, stating, “When I started the journey to healing, it was ‘I want healing at any cost.’” She further elaborated, “That’s why I was created so stubborn . . . digging my heels into the sand, being like, I’m not going to let them win. I’m not. And if it takes me 40 years, I’m not gonna let them.”
The final quality that was noted as a personal strength by all 10 participants was having both a warrior and survivor mindset. Crystal expressed this mindset by saying, “I refuse to let them [sex traffickers] win. . . . it took a lot of work to come back. . . . They tried to take my voice, but they didn’t. . . . I started voice therapy . . . and it’s already a little bit better.” Gretchen shared that feeling “powerful again . . . I am you know, like f*ck it. F*ck all of you, like, I’ll just do whatever . . . instead of feeling those true, awful, sad emotions . . . like, what happened to me wasn’t my choice.” Mia ascribed such a strength to her willingness to take risk, while Monica summarized it as, “I’m a warrior, I have superpowers, and I’m a superwoman.”
Finding Meaning in the Everyday—“I Have Joy”
All 10 participants highlighted Finding Meaning in the Everyday despite their traumatic experiences from sex trafficking, with many expressing acceptance, gratitude, and self-empowerment as they reclaimed their lives and healed, exemplified through narratives of finding their voice, embracing happiness, reconciling with their bodies, drawing strength from their faith, and engaging in acts to make a new beginning. Annabel’s story captured this subtheme when she acknowledged the struggle of getting “comfortable exercising those new muscles” of learning to “value” oneself, to do “something healthy,” and doing things that make one “happy.”
Participants expressed a sense of acceptance and gratitude for where they are today. Niki expressed, “I’m <pause> having to accept that I am not the same person. . . . I’m just doing my best in that moment and being okay with that, instead of, like, trying to beat myself up.” Betty shared that her life could have been worse: “I’m pretty fortunate that I didn’t have any other long-term . . . like, I don’t have HIV, or Hep-C, or I didn’t have kids.” Monica noted that acceptance involved permitting herself to be happy: “I was truly in this push and pull of, like, is happiness real? . . . It’s okay to be happy. . . . It’s okay to feel fulfilled, it’s okay to feel abundance.” Cassie captured the magnitude of time it has taken her to heal and accept her body: “I have spent the last probably 15 years coming back into my body.”
Most participants reframed their perspective toward life and self-identity. Some of them, like Crystal, experienced this reframe because of their faith: “I have joy, which is like that inner contentment, that peace . . . that surpasses all understanding.” She went on to say, “The Crystal that I am now is who God intended me to be; the person that I was before is who my family made me think that I was.” Others, like Mia, reframed the way they viewed life after sex trafficking, emphasizing the potential for the experience to change and empower oneself.
Creating Paths Forward—“I Just Want to Get Out There and Do My Part”
While five participants identified education as key to their story, all 10 participants shared about Creating Paths Forward after their life of sex trafficking. This involved pursuing a new career path, having an entrepreneurial mindset, desiring to educate and train other professionals, and having the drive to empower other survivors. All participants were pursuing a new career path focused on mental health, nursing, shelter coordination, or advocacy work. Participants discussed how education and work helped them find a new sense of purpose. Jennifer emphasized, “Education is key. That was probably one big part of my story.” Betty similarly noted that “finding something to give yourself purpose . . . finding purpose helps you overcome everything.” For Cassie, securing student loans was a step toward this new purpose. Crystal expressed a deep love for learning, while Betty pursued her goal of going to nursing school. Jes found that engaging in sales jobs when she left sex trafficking was “powerful for deep inner healing,” understanding how these avenues contributed to a sense of empowerment and recovery.
These professional roles highlighted how survivors’ traumas led them to engage in trauma-informed care, helping others navigate similar difficult experiences while healing from their past traumas. For example, Betty shared, “I am a nurse now. I’m a nurse educator,” and one of her main goals “is to integrate sex trafficking education for nursing staff.” Cassie commented on becoming a shelter coordinator for a “domestic violence and sexual prevention program,” and that she loves what she does: “I love helping other people—I don’t care how I’m helping them, what capacity, as long as I’m helping, I am happy.”
Participants shared how they developed an entrepreneurial mindset, starting nonprofits or other organizations to bridge gaps in services, such as emergency response and long-term support programs. Crystal expressed the desire to open a nonprofit organization to help women escape sex trafficking: “I’m trying to bridge that gap. . . . I’m not gonna wait and say, ‘Oh you have to call me back so we can do an intake process to see if you’re good fit or not [to get help].’” Similarly, Monica’s platform is focused on “bring[ing] awareness that survivors are not a threat or they’re not a victim . . . they need to be treated with such respect as an identity, like a superpower.”
Participants also expressed the desire to educate and train other professionals, helping others and making systemic changes, particularly in health care, law enforcement, and legal systems. For example, Mia has visited “14 countries on four continents doing missions work and working with non-government organizations doing humanitarian work” in which she focuses on helping lawmakers or government agencies specifically around child trafficking. She is using her story of sex trafficking “to help police departments and DAs and lawmakers . . . see [sex trafficking]. . . . I want to be able to equip, you know, whether it be therapists or cops, or law enforcement, or you know, the legal system.
A final dimension of this subtheme highlighted by all 10 participants was the desire to empower other survivors, shifting the narrative from victimhood to empowerment. Their stories also revealed the challenges faced in overcoming criminal records, trauma, and societal stigma, inspiring them to advocate for more respect and understanding of survivors’ journeys. Crystal shared, “I’m trying to save people’s lives. People saved my life . . . I intend to use [it] to help other women . . . I just want to get out there and do my part.” Jennifer described working as the shelter coordinator and also serving as “a part-time deputy” to help other survivors. And Monica is using her education as a life coach to help survivors with their “trauma response and transformation. . . . I really work hard on helping survivors heal . . . [to] stop placing themselves as victims and start thriving as survivors and leaders.” Collectively, these narratives underline the resilience of survivors and their dedication to using their experiences to educate, advocate, and support others within and beyond their communities.
Spiritual Grounding and Rediscovery—“Untangling the Mess”
Seven participants reported relying on religion to cope with the aftermath of their sex trafficking experiences and to search for deeper meaning. Crystal stated, “That’s been the best thing out of all this, like kind of makes it all worth it, because the relationship I have with God now, yeah. It was worth going through everything I went through.” The discovery of purpose and strength through religion and spiritual practices was commonly reported among participants. Crystal emphasized the importance of her faith, stating, “Obedience to God is the only thing that kept me here.” Jes added, “I just started searching for answers,” reflecting a journey of meaning-making that helped anchor her during her healing.
They found comfort in their faith as they navigated the healing process, valuing the relationship and sense of meaning that emerged from their sex trafficking experiences. Six participants reported continuing to practice religion and finding a silver lining in their experiences. Gretchen reported, “Hopefully, God willing, I will be able to move away from here someday, but I think, you know, I have, like, really big faith and, like, God put me here for a reason.” For others, spirituality became a path for self-discovery and identity formation. Mia described being on a journey to understand who she truly was, while Monica highlighted the role of spiritual beliefs in helping her recognize and embrace her identity as a survivor. Of them, three participants described reframing their view of religion, recognizing that individuals have some control over their divine life, destiny, and purpose. For example, Mia and Monica spoke about their journeys of self-discovery and finding their identity through spiritual exploration. In contrast, two participants expressed redefining their spiritual identity as neither religious nor spiritual. Betty shared her journey: “I absolutely decided like I’m not Christian. For a long time, I considered myself an atheist, I don’t believe in anything, but over time I have really connected with my spiritual self . . . I would consider myself a Pagan now.”
Past Survival Mechanisms Evolving Into Coping Strategies
All 10 participants identified past survival mechanisms that once shielded them from immediate psychological harm but have since evolved into coping strategies, facilitating PTG. These mechanisms, such as acceptance, handling crisis situations, substance coping, and avoidance coping, highlight the participants’ resilience and ability to navigate challenging environments while seeking healing
and growth.
Acceptance coping emerged as a pivotal process for participants, marked by an eventual awareness of their trauma and a willingness to confront it. Many described the delayed realization of their experiences, often occurring long after the traumatic events. Jennifer shared how she initially failed to recognize her reality, noting that when she was in the midst of it, she “didn’t even realize that’s what it was.” Similarly, Annabel reflected on how she spent years believing her experiences were normal or expected, only to later understand the severity of her situation. She recalled a conversation with a friend who said, “I can’t believe I know a victim of trafficking,” to which Annabel responded, laughing, “Who?” Her friend’s reply, “You,” was a startling revelation. As participants moved toward acceptance, many began dismantling survival personas they had developed to protect themselves. Monica explained how she had “played roles and characters” during her trauma, but healing required her to “take down that mask” and embrace her authentic self. For her, the journey to authenticity involved intense healing and self-discovery, which she described as both liberating and transformative.
Participants also demonstrated exceptional crisis management skills, or a sense of keen intuition, often rooted in their need to survive. Jes shared needing to “read body language and understand how to perceive people,” a skill that became second nature over time. Mia further commented that “trafficking survivors have been taught to read their audience. . . . they’re gonna be able to see it on your face because that’s what they’ve been trained to do. . . . I still to this day can read people really well.” Dissociation also played a significant role, allowing participants to detach from their immediate realities. Cassie explained how she “detached from [herself]” as a survival mechanism, while Betty noted that dissociation led to “huge blocks of memories that are gone,” which helped protect her from the overwhelming trauma. For Annabel, dissociation was both a liability and a tool that allowed her to function. She reflected on how it helped her succeed in academic and workplace settings, as it gave the impression that she was “much more functional.” While acknowledging its downsides, she described her dissociation as more “managed” now, highlighting its adaptive value.
Substance use was identified as another critical survival mechanism, providing temporary relief from the pain and chaos participants endured. For Annabel, drug use was a means of survival, as she admitted that “a good stint of drug use” likely saved her life. She described how substances helped her tolerate what she was experiencing, echoing sentiments shared by Betty and Cassie, who also turned to drugs as a way of coping with their trauma. Although harmful in the long term, substance use offered an escape during moments of extreme distress. As participants transitioned into recovery, some replaced illicit substances with prescribed medications to manage ongoing challenges. Gretchen, for example, explained how she now uses medication to address high blood pressure and anxiety, demonstrating a shift toward healthier coping strategies.
Finally, avoidance strategies, including running away and emotional distancing, were essential survival tools for many participants. Crystal shared how physical avoidance, or running, was a literal means of staying alive for her. Emotional avoidance also played a role, with Betty describing herself as “very distrustful” of others as a way to protect herself. Although these strategies sometimes prevented participants from fully engaging with their trauma, they were vital in enabling them to navigate and survive their immediate environments.
Together, these diverse coping mechanisms, whether acceptance, dissociation, substance use, spirituality, or avoidance, illustrate the complex, adaptive ways in which survivors of trafficking have navigated their pasts. Over time, these mechanisms have evolved, allowing participants to pursue growth and healing while continuing to adapt to the challenges of their unique journeys.
External Factors Promoting Change
All participants highlighted various external contextual factors that supported their growth and healing, ranging from supportive resources and services to meaningful social support systems, including the role of counselors. We organized these insights into three subthemes: Close Relationships, Supportive Resources and Services, and Counseling Experiences and Alternative Paths to Healing.
Close Relationships—“I Needed Somewhere to Go”
This subtheme was endorsed by all 10 participants, reflecting the significant challenges and complexities survivors of sex trafficking face in their relationships, trust, and healing. Participant narratives revealed the profound challenges of forming and maintaining close relationships, alongside the critical role of family, community, and pivotal interventions in their healing. Although many survivors continue to grapple with distrust and self-protection, the presence of supportive networks and key turning points fosters resilience and PTG, enabling them to navigate their journeys toward recovery.
Firstly, all participants described how trust and vulnerability became extremely difficult after their trafficking experiences. Monica, for example, explained how it takes time to feel safe opening up to loved ones, contrasting it with the transactional nature of sex trafficking. Despite being 7 years removed from her trafficking experience, Monica noted she is “still working on trust issues,” particularly in the context of her small, close-knit community. Additionally, Betty and Annabel highlighted how survival mechanisms during trafficking carried over into their post-trafficking lives. Betty described herself as “distrustful” and admitted to avoiding romantic relationships entirely, saying, “I don’t really bond with men. . . . Like, I could see myself being single forever.” Though initially difficult, she shared that she has come to terms with this choice, adding, “I am finally at a point now where I am okay with being alone.” Annabel, on the other hand, described how she learned to maintain superficial relationships as a way to stay safe, stating that she became “really good at superficial relationships” and intentionally shares “just enough personal details so that people think they have some understanding of me.”
The lasting effects of trauma created further barriers to forming close relationships. Crystal spoke about the overwhelming impact of triggers, explaining that “the nightmares, the flashbacks . . . smells, areas” make it difficult to rebuild trust. She poignantly concluded, “You can’t teach somebody how to trust again. You just can’t.” Secondly, despite these challenges, five participants described how community support played a crucial role in their healing process. Niki emphasized the normalizing and validating effect of being in a survivor community, noting that connecting with others who had similar experiences made her feel less isolated and helped her develop compassion for herself and others. She reflected, “It’s given me a new level of grace for . . . people’s brokenness.” Mia encapsulated the importance of collective care in her statement that “it takes a village to have a human trafficking survivor recover and live a meaningful life.” Thirdly, support from family members emerged as a critical factor for most participants. Monica expressed deep gratitude toward her daughter, who encouraged her to seek help and begin her recovery journey. Similarly, Betty described the unwavering support of her parents, who were aware of what she had endured but never judged or mistreated her. Betty also described how her family helped her escape, recalling, “They packed up my apartment and moved me to an undisclosed location. And that’s kind of how I actually found my freedom.” Jennifer noted that her mother played an essential role in her recovery, sharing that “she was always there for everything, if I needed to talk, if I needed somewhere to go.” Gretchen echoed this sentiment, reflecting on how her family stepped in to help her, saying, “Luckily, I had family that would help me.” Other participants recalled individuals who helped them envision a different future. Betty shared how a preceptor during her training encouraged her to pursue nursing, saying, “She’s like, ‘You shouldn’t be a medical assistant; you need to be a nurse and go back to school.’”
Next, several participants highlighted how their upbringing and privilege laid a foundation for resilience. Betty reflected on her stable background, saying, “I had a great family . . . a wonderful upbringing. I was a middle-class White female from a very conservative military family.” Gretchen similarly described her childhood as “pretty normal,” emphasizing the stability of having “both my parents together” and a mother who had a successful career. Finally, Jes added that she consciously uses her privilege to make a difference, stating, “I use my privilege to kick open the door.”
Supportive Resources and Services
All 10 participants described the availability and access to various services as crucial factors in promoting their PTG experience. Frequently mentioned were access to education, housing, mental health services, substance abuse recovery centers, and advocacy agencies. For example, Crystal emphasized the importance of “resources for education and housing,” while Cassie underscored the value of “having survivor leaders in those types of programs” to foster a deeper sense of understanding and connection. Similarly, Annabel highlighted the importance of mental health deputies who are “trained to respond to her unique needs,” explaining how they could “use the powers of law enforcement to quickly get to me, before I get too far.”
Participants also shared names of specific organizations and programs that played influential roles in their recovery journeys. Some of them were nonprofit organizations, or a community-based advocacy initiative, or a faith-based program. Additionally, many found the scholarship support that some of the school programs offered to be incredibly helpful. Many also emphasized the role of programs that offered vocational training and legal assistance to be extremely instrumental in regaining stability.
Participants experienced interventions or moments that prompted lasting change. Health care providers, educators, family members, and peers often served as catalysts for PTG. Betty credited her primary care doctor for recommending her first counselor after learning about her trauma during a routine clinical exam. She explained, “I wouldn’t have seen that first counselor at Kaiser if it wasn’t recommended by my primary care doctor.” For Mia, safe spaces at school—like time spent with the librarian—provided much-needed respite: “I could escape for half an hour, 45 minutes.” These supports were often intertwined with personal growth and self-discovery. Jes highlighted how sales training helped her “establish better boundaries and figure out who I was and how I wanted to help people,” while Gretchen shared how bodybuilding boosted her confidence and strengthened her faith.
Niki credited exercise for rebuilding trust in herself and staying physically present: “It was really helpful for me because I was checking out all the time.”
Spirituality and faith were also recurring themes. Many participants found strength through religious programs, community resources, or personal faith. Gretchen described how faith and bodybuilding were interwoven in her journey to healing. Finally, advocacy agencies and survivor-led programs emerged as critical enablers of recovery. Cassie stressed the importance of survivor leaders, noting, “It takes someone who is a survivor who is really going to be able to understand how to respond.” Similarly, Gretchen noted the value of advocacy agencies and peer support groups, while Annabel highlighted the role of trauma-informed law enforcement and ritual abuse trafficking supports.
Counseling Experiences and Alternative Paths to Healing
All participants described varied experiences with mental health services, which were pivotal in their journeys toward PTG. Key themes included the importance of counseling, support groups, and alternative healing methods. Critical factors were counselor characteristics, multidisciplinary support, and access to alternative therapies.
For many, counseling played a central role in healing. Cassie shared attending therapy “off and on, pretty much [her] whole life,” while Gretchen found it consistently helpful. Monica said, “Because of therapy, I got in touch with my first nonprofit,” which led to public speaking and professional growth. Therapy addressed trauma and empowered participants to explore their potential. Mia found strength in her therapist’s gentle honesty, and Monica credited therapy with healing from sex addiction. Jes emphasized that having the “right therapist” was essential.
Participants identified key counselor traits in four areas: knowledge, skills, disposition, and practices. Annabel emphasized the importance of understanding trafficking-specific dynamics. Creativity was a valued skill. Jes appreciated a “tender heart” balanced with desensitization, while Mia praised “gentle reality checks with massive doses of compassion.” Patience and honesty were highlighted repeatedly as essential for building trust. Monica and Annabel emphasized the importance of safety and collaboration, while Annabel also recommended involving survivor mentors.
Participants also turned to alternative healing approaches. Betty credited her dog for saving her life and praised animal therapy. Niki found yoga and dance helped release trauma: “Trauma can get locked in your body . . . doing certain movements helps.” Somatic therapies such as massage, float therapy, and trauma touch therapy were described as deeply calming. Mia appreciated trauma touch therapy because “you don’t have to say a word . . . it simply lets your body release the trauma.” Reiki, bodybuilding, retreats, and art therapy also provided outlets for recovery. One participant described reiki as emotionally freeing, while another found smashing objects helped release rage.
Support groups were vital, especially when individual counseling wasn’t accessible. One participant noted that support from peers “made a big difference,” while another participant saw survivor groups as protective against re-trafficking. Another participant stated that she gained confidence speaking in group settings, while one other participant stressed the importance of a coordinated trauma response and informed professionals who could meet survivors where they were in their healing.
Discussion
This study examined the lived experiences of PTG among sex trafficking survivors using a transcendental phenomenological approach. By bracketing assumptions and centering participant voices, we identified themes reflecting both internal agency and external influences. Rather than imposing a framework, we allowed themes to emerge from survivor narratives and later contextualized them through PTG scholarship. Findings highlight the complex nature of growth and the dynamic interplay between survival mechanisms, personal development, and supportive environments.
Internal Agency Driving Change
Participants’ narratives revealed that PTG was not linear but a dynamic process rooted in reclaiming power, identity, and meaning. Survivors drew on personal strengths such as resilience, confidence, forgiveness, and self-awareness. Developing a “warrior” and “survivor” mindset marked a shift from victimhood to agency as participants redefined their self-concept and resisted being reduced to their past. These accounts align with the PTG domain of personal strength (Tedeschi & Calhoun, 2004), though the framing came from survivors’ voices. Resilience was seen as both empowering and protective, reflecting a nuanced understanding of strength (Luthans et al., 2006). Survivors acknowledged vulnerability not as weakness but as a space for growth. Healing required confronting fear and suffering while reclaiming agency—consistent with trauma-informed resilience, which emphasizes growth through engagement with pain (Courtois & Ford, 2013).
Survivors also cultivated joy, gratitude, and acceptance through reflection and reframing. This shift supported a more empowered relationship with self and others. These experiences mirror findings on the role of gratitude in fostering growth (Fredrickson et al., 2003; Park & Ai, 2006). Redefining purpose through advocacy and education emerged as another form of internal agency. Survivors pursued careers and roles that allowed them to “do their part,” transforming past suffering into purposeful action. Advocacy became a way to reclaim power, support others, and create change. These findings align with research linking prosocial behavior to PTG (Linley & Joseph, 2004) and reflect both personal and relational redefinition (Park & Ai, 2006; Tedeschi et al., 2018). Spiritual grounding also contributed to identity reconstruction, with survivors finding meaning through faith or redefining their beliefs. This spiritual growth reflected personal framing and aligned with broader PTG literature (Park & Ai, 2006).
A novel insight was the recontextualization of survival mechanisms such as dissociation, substance use, and hypervigilance, which were described as adaptive tools that later evolved into coping strategies. Survivors did not view these as inherently maladaptive but as necessary for survival. Over time, they became integrated into intentional healing. This perspective affirms trauma-informed models that recognize these behaviors as adaptive (van der Kolk, 2014). For example, hypervigilance was reframed as intuition, and dissociation transitioned into mindful awareness, demonstrating survivors’ capacity to extract meaning from adversity (Luthans et al., 2006).
External Factors Promoting Change
External support systems played a vital role in participants’ growth. Survivors emphasized the value of close relationships with family, mentors, or peers, while also naming the difficulty of rebuilding trust. Survivor-led networks helped them connect without fear of judgment, underscoring the importance of relational safety in trauma recovery. Though many initially struggled with vulnerability, forming safe connections brought healing benefits, even amid ongoing trust issues. This finding aligns with attachment-based trauma recovery models, which highlight the reparative potential of secure relationships (Courtois & Ford, 2013; Herman, 1997).
Access to counseling and trauma-informed relationships was also pivotal in supporting participants’ growth. Participants valued counselors who showed patience, honesty, warmth, and structure. These were reported as some qualities that foster trust and reflection. These traits reflect trauma-informed principles (Hays & Singh, 2023; Herman, 1997). Support groups further offered validation and community, reinforcing survivor networks as protective against re-trafficking. Survivors also engaged in non-traditional healing approaches, including movement-based therapy, spiritual practices, creative arts, retreats, and animal-assisted interventions. These practices enabled emotional release, reconnection with the body, and creativity, affirming the need for individualized, culturally relevant care.
Implications for Practice
This study underscores the complexity of PTG among sex trafficking survivors, demonstrating that growth involves both internal processes and external sources of support. By centering participants’ voices, we uncovered themes that reflect established PTG domains (Tedeschi & Calhoun, 2004) while expanding the framework to include survival mechanisms as foundations for growth.
The findings offer insights for enhancing trauma-informed care and guiding counselors, researchers, and policymakers. Key implications include integrating strengths-based, individualized interventions that emphasize support networks, empowerment, and community engagement. Counselors should view survival mechanisms like dissociation or substance use as adaptive responses and help survivors reconceptualize them into healing tools. Creativity, patience, and honesty were identified as essential counseling traits. Therapies such as somatic work, art, and movement-based interventions should be considered. Involving survivors in treatment planning helps tailor care to their unique goals.
Support groups and survivor-led programs are vital for fostering PTG and preventing re-trafficking. Counselors should collaborate with nonprofits and survivor communities to build peer support models that offer connection and validation. A multidisciplinary approach is essential, requiring collaboration among mental health professionals, social workers, medical providers, and legal advocates. Training in trauma-specific competencies such as recognizing trafficking indicators and addressing ritualistic abuse is critical. Survivors also emphasized rediscovering identity and agency. Counselors can support this by creating leadership opportunities including mentoring, advocacy, writing, or speaking. Incorporating survivor voices into policies and services can strengthen the effectiveness of survivor-centered care.
Finally, consistent with the counseling profession’s emphasis on strengths-based approaches, our findings underscore the importance of recognizing and building upon survivors’ existing resources, including resilience, agency, and the warrior mindset described in their narratives. Counselors can integrate trauma-informed best practices with these strengths to promote empowerment, identity reconstruction, and long-term well-being (Courtois & Ford, 2013; Hays & Singh, 2023).
Limitations and Recommendations for Future Research
Although this study offers valuable insights into PTG among sex trafficking survivors, several limitations should be noted. Participants were recruited primarily through advocacy networks and social media, which likely attracted individuals already engaged in healing or public advocacy. This self-selection may reflect those already experiencing PTG and may have excluded individuals in earlier or more complex stages of recovery. Future research should include more diverse survivor experiences, especially those in the immediate aftermath of trauma, to capture a broader range of recovery trajectories.
The study’s limited cultural and racial diversity also affects generalizability, underscoring the need to explore how cultural factors influence PTG and intervention effectiveness. The cross-sectional design offered only a snapshot of PTG. Longitudinal research could better illuminate how survival mechanisms like dissociation evolve into adaptive strategies. Further research is needed to examine the role of alternative practices such as somatic approaches, yoga, or animal-assisted activities, which some survivors found meaningful, though their effectiveness in addressing mental health concerns remains under investigation. Finally, engaging survivors as co-researchers can ensure their lived experiences meaningfully shape future research and advocacy.
Given these limitations in generalizability, future research should also focus on refining theory related to survivor-defined PTG. Clearer theoretical frameworks are needed to distinguish PTG from related constructs such as resilience and healing, and to guide counseling interventions that are both evidence-based and survivor-centered.
Conclusion
This study examined survivor-defined PTG among sex trafficking survivors, highlighting resilience, identity shifts, and renewed purpose. Survivors described PTG as more than recovery, involving meaning-making, agency, and hope. These findings support strengths-based, trauma-informed counseling that amplifies survivor voices and fosters growth beyond symptom relief. Training programs should prepare counselors to recognize and support PTG, while future research can expand survivor-centered definitions across diverse contexts and evaluate interventions that intentionally promote growth.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
Courtois, C. A., & Ford, J. D. (2013). Treatment of complex trauma: A sequenced, relationship-based approach. Guilford.
Fredrickson, B. L., Tugade, M. M., Waugh, C. E., & Larkin, G. R. (2003). What good are positive emotions in crisis? A prospective study of resilience and emotions following the terrorist attacks on the United States on September 11th, 2001. Journal of Personality and Social Psychology, 84(2), 365–376. https://doi.org/10.1037/0022-3514.84.2.365
Hays, D. G., & Singh, A. A. (2023). Qualitative research in education and social sciences (2nd ed). Cognella.
Henson, C., Truchot, D., & Canevello, A. (2021). What promotes post traumatic growth? A systematic review. European Journal of Trauma & Dissociation, 5(4), 100195. https://doi.org/10.1016/j.ejtd.2020.100195
Herman, J. L. (1997). Trauma and recovery: The aftermath of violence—From domestic abuse to political terror. Basic Books.
Linley, P. A., & Joseph, S. (2004). Positive change following trauma and adversity: A review. Journal of Traumatic Stress, 17(1), 11–21. https://doi.org/10.1023/B:JOTS.0000014671.27856.7e
Luthans, F., Youssef, C. M., & Avolio, B. J. (2006). Psychological capital: Developing the human competitive edge. Oxford University Press. https://doi.org/10.1093/acprof:oso/9780195187526.001.0001
Moustakas, C. (1994). Phenomenological research methods. SAGE.
Park, C. L. (2010). Making sense of the meaning literature: An integrative review of meaning making and its effects on adjustment to stressful life events. Psychological Bulletin, 136(2), 257–301. https://doi.org/10.1037/a0018301
Park, C. L., & Ai, A. L. (2006). Meaning making and growth: New directions for research on survivors of trauma. Journal of Loss and Trauma, 11(5), 389–407. https://doi.org/10.1080/15325020600685295
Schultz, T., Canning, S. S., & Eveleigh, E. (2020). Posttraumatic stress, posttraumatic growth, and religious coping in individuals exiting sex trafficking. Journal of Human Trafficking, 6(3), 358–374. https://doi.org/10.1080/23322705.2018.1522924
Smith, J. A., Flowers, P., & Larkin, M. (2009). Interpretative phenomenological analysis: Theory, method and research (1st ed.). SAGE.
Tedeschi, R. G., & Calhoun, L. G. (1995). Trauma and transformation: Growing in the aftermath of suffering. SAGE.
Tedeschi, R. G., & Calhoun, L. G. (2004). Posttraumatic growth: Conceptual foundations and empirical evidence. Psychological Inquiry, 15(1), 1–18. https://doi.org/10.1207/s15327965pli1501_01
Tedeschi, R. G., Shakespeare-Finch, J., & Taku, K. (2018). Posttraumatic growth: Theory, research, and applications (1st ed.). Routledge. https://doi.org/10.4324/9781315527451
van der Kolk, B. A. (2014). The body keeps the score: Brain, mind, and body in the healing of trauma. Penguin Books.
Victims of Trafficking and Violence Protection Act of 2000, Pub. L. No. 106-386, § 103, 114 Stat. 1470.
Zoellner, T., & Maercker, A. (2006). Posttraumatic growth in clinical psychology—A critical review and introduction of a two-component model. Clinical Psychology Review, 26(5), 626–653. https://doi.org/10.1016/j.cpr.2006.01.008
Apr 1, 2026 | Volume 16 - Issue 1
Danielle Pester Boyd, Laura K. Jones, Courtney Maier, Danica G. Hays
The intentional exploration or broaching of topics related to the social determinants of mental health (SDoMH) throughout the counseling process helps align clinical practice with the profession’s focus on multicultural and social justice counseling competency. This article identifies six SDoMH broaching behaviors for counselors: (a) counselor development, (b) client psychoeducation, (c) contextualization, (d) attending to differences, (e) addressing emergent needs, and (f) termination practices. These SDoMH broaching behaviors span counselor preparation, assessment, intervention, and termination, empowering counselors to address SDoMH in their work. We conclude with implications for fostering SDoMH broaching behaviors within counselor education.
Keywords: broaching, social determinants of mental health, multicultural, counseling competency, counselor education
Counselors are increasingly called upon to integrate multicultural competence and social justice advocacy into their practice, particularly when addressing systemic and environmental factors that shape client well-being. The Multicultural and Social Justice Counseling Competencies (MSJCC; Ratts et al., 2016) and relevant constructs, such as the social determinants–based counseling model (SDCM; Pester Boyd et al., 2025) and the multidimensional model of broaching behavior (MMBB; Day-Vines et al., 2020), provide guiding frameworks for ensuring culturally responsive care. Taken together, these models inform concrete methods for integrating discussions of systemic, environmental, and structural influences into counselor–client interactions, which create a foundation for a set of broaching behaviors focused specifically on the social determinants of mental health (SDoMH).
Social determinants of health (SDOH) refer to “the conditions in which people are born, grow, live, work, and age that shape health outcomes” (World Health Organization [WHO], 2025, para. 1). These determinants include economic stability (e.g., employment, income), health care access, education, neighborhood safety, and social relationships, all of which impact physical and mental health. The SDoMH focus specifically on the social and structural factors influencing mental health outcomes, such as exposure to discrimination, adverse childhood experiences, community violence, economic disparities, and barriers to mental health care (Compton & Shim, 2020), influences that are reflected in the MSJCC.
The SDCM is an empirically based systemic framework for addressing SDoMH across various practice settings (Pester Boyd et al., 2025). It guides counselors in identifying barriers, such as economic hardship, discrimination, and limited access to resources, and then provides a structured process for broaching these concerns in session. Beyond simple recognition, the SDCM emphasizes implementing culturally responsive interventions, including connecting clients with community supports, advocating for policy changes, or adapting treatment plans to account for systemic stressors. This systemic responsiveness communicates to clients that their external challenges are legitimate and central to their mental health care, which reinforces the therapeutic alliance by integrating advocacy with clinical practice. Given the links among the MSJCC, SDoMH, and therapeutic outcomes, it is imperative that counselors are familiar with SDoMH, understand their impact, and are prepared to broach topics related to SDoMH with clients. Therefore, integrating the SDCM with known broaching models like the MMBB can serve to operationalize these action strategies as concrete methods to demonstrate the MSJCC.
The MMBB provides a framework to explicitly explore or broach racial, ethnic, and cultural (REC) factors with clients throughout the therapeutic process (Day-Vines et al., 2020, 2021). These broaching behaviors focus on four distinct contexts: intracounseling, intraindividual, intra-REC, and inter-REC domains. Specifically, counselors acknowledge REC concerns that impact the counselor–client relationship (intracounseling), the intersections of the client’s identity (intraindividual), the client’s cultural group membership (intra-REC), and their experiences with structural inequality (inter-REC). By intentionally attending to these layers, counselors demonstrate cultural humility and multicultural competency that affirms the realities of clients’ REC concerns. Effective broaching has been linked to enhanced client trust, increased depth of client self-disclosure, higher levels of client satisfaction, and improved therapeutic outcomes, which make it a critical component of effective multicultural counseling (Depauw et al., 2025; Gantt-Howrey et al., 2024; King & Borders, 2019; Zhang & Burkard, 2008).
By integrating the SDCM with the MMBB, we developed a set of SDoMH-specific broaching behaviors. The MMBB strengthens the relational dimension of counseling through cultural engagement while the SDCM equips counselors to act on systemic barriers that influence client well-being. Together, these models ultimately foster trust, collaboration, and empowerment and establish counseling as a space where both individual experiences and broader structural inequities are acknowledged and addressed.
SDoMH Broaching Behaviors
This article describes six SDoMH broaching behaviors for counselors grounded in the MMBB and the SDCM: counselor development, client psychoeducation, contextualization, attending to differences of lived experience, addressing emergent needs, and SDoMH-informed termination practices. These SDoMH broaching behaviors represent an interactive approach in which counselors shift among the behaviors throughout their own development as well as during assessment, intervention, and termination within the counseling relationship.
Counselor Development
The first SDoMH broaching behavior is initiated during a counselor’s preparation to work with clients. In alignment with the MSJCC (Ratts et al., 2016), counselors are expected to continually foster both knowledge and self-awareness related to the multicultural and social justice issues facing their clients, including client experiences with SDoMH. In order to develop their knowledge of SDoMH scholarship, counselors can familiarize themselves with the seminal SDOH/SDoMH frameworks (e.g., Compton & Shim, 2020; Lund et al., 2018; WHO, 2025); guiding practice models related to broaching behaviors and best practices for addressing the SDoMH (e.g., MMBB, SDCM; Day-Vines et al., 2020; Pester Boyd et al., 2025); general scholarship on SDoMH application in training, practice, and research (e.g., Johnson et al., 2023; Lenz & Lemberger-Truelove, 2023; Lenz & Litam, 2023; Mason et al., 2023; Neal Keith et al., 2023; Pester et al., 2023); and, when applicable, setting-specific SDoMH resources for school counselors (e.g., Brookover, 2024; Johnson & Brookover, 2021), career counselors (Johnson et al., 2024), and family counselors (Robins et al., 2022).
Next, to facilitate self-awareness, counselors are encouraged to engage in reflective practices that identify areas of strength in addressing SDoMH with clients and areas that require skill and dispositional development. First, counselors should reflect on any personal experiences with SDoMH and how those experiences may both inform and potentially bias their work with clients. For example, counselors who have dealt with their own experiences of economic instability may need to watch for emerging countertransference with clients having similar experiences. We recommend that counselors review existing SDoMH frameworks and identify which determinants have affected them personally and interpersonally with peers, family members, and colleagues. In addition, they can consider what strategies were helpful or harmful as they personally navigated SDoMH.
Counselors should also reflect on any prior experiences working with clients who were dealing with SDoMH and how those prior professional experiences might inform and potentially bias their ability to help new clients with SDoMH. For example, counselors might view clients as resistant if they do not consistently attend counseling sessions, although those clients may be dealing with circumstances impacted by SDoMH (e.g., unstable transportation, lack of childcare, unreliable internet access). Mechanisms such as supervision or consultation can be helpful for facilitating counselor awareness and development related to being nonjudgmental, showing unconditional positive regard, and embodying congruence, which are all vital components of creating and maintaining a strong therapeutic alliance.
Additionally, counselors or counseling supervisors can administer the Addressing Client Needs with Social Determinants of Health Scale (ACN:SDH, Johnson, 2023) to more formally assess readiness for addressing SDoMH. This tool measures a provider’s SDOH competency related to knowledge, awareness, biases, skills, and preparedness. The ACN:SDH findings can be reviewed within supervision or consultation. For areas where data reflect a lack of readiness, counselors can process feelings associated with their limited readiness and brainstorm resources that may be useful for building readiness. Ultimately, as counselors focus inward to broach and support their professional development related to the SDoMH framework, they will be more prepared to implement the remaining SDoMH broaching behaviors in client interactions.
Client Psychoeducation
Client psychoeducation is the next SDoMH broaching behavior that begins during the intake and assessment process. Psychoeducation is an evidence-based intervention that integrates client education into the counseling process by connecting clinical outcomes to increased client self-awareness and skill development across many mental health presenting concerns (e.g., anxiety, depression, schizophrenia; Dolan et al., 2021; Luo et al., 2025). We suggest that counselors mindfully introduce SDoMH psychoeducation into the intake and assessment process to increase client knowledge and awareness about the potential impact of SDoMH on well-being.
Furthermore, there is growing support for universal SDoMH screening (Gantt-Howrey et al., 2024; Johnson & Brookover, 2021; Johnson et al., 2023), with many available screeners for counselors to use, including the Protocol for Responding to and Assessing Patients’ Assets, Risks, and Experiences (PRAPARE; 2022); the Accountable Health Communities Health-Related Social Needs Screening Tool (Center for Medicare and Medicaid Innovation, n.d.); and the WE CARE Survey (Garg et al., 2007). These screeners can be incorporated into intake processes to establish a baseline of SDoMH data for clients. For example, the PRAPARE assessment identifies both individual areas of risk related to social determinants and an overall risk tally score. Counselors can use this data to inform both the focus of the psychoeducation intervention and the client’s treatment plan.
Many clients may not fully understand why they are being asked about these areas of their lives or be aware of how these determinants may influence well-being. Therefore, counselors should first define SDoMH and explain the overall framework using jargon-free language. For example:
Social determinants of mental health are different social and environmental factors that can positively or negatively influence our physical and mental health. These can be factors like having your basic needs of food, housing, and employment met; having access to quality education and health care; living in a safe environment free of violence and risk; and having strong social and community support. The more people are surrounded by supportive social and environmental conditions, the easier it is to improve overall health and mental health. When people do not have adequate access to these conditions, it can lead to a higher risk of health and mental health concerns. It is important for the work that we are going to do together to have a clear picture of how your environment is influencing your physical and mental health so that we can work to increase conditions that will support the positive mental health changes you are wanting to make.
Counselors can also consider using visual tools in session, such as handouts that depict SDoMH in an easily understandable format (see Figure 1 for a sample).
Counselors should then use the SDoMH data collected through the assessment process to provide data-driven psychoeducation about the specific social determinant risk areas identified in a client’s assessment, outlining the research and known physical and mental health risks and outcomes of those determinants. For example, one item on the PRAPARE assessment asks, “How often do you see or talk to people that you care about and feel close to?” If a client answers less than three times per week, they are flagged for a risk tally on this item; the counselor could provide psychoeducation on the impact of social connection and community support alongside the risks of social isolation (U.S. Department of Health and Human Services, 2023). A counselor might broach the topic by saying:
I noticed when you were asked how many times you see or talk to people you care about that you answered less than three times per week. I ask this question on the screener because at times the number and quality of our social connections can have an influence on our physical and mental health. For example, social isolation has been linked to increased risk of anxiety and depression, lower academic and job performance, greater susceptibility to viruses and respiratory illnesses, and even long-term risk of diseases such as heart disease and stroke. Healthy social connection can protect us from disease and increase our sense of safety, meaning, and resilience. Tell me more about what social connection looks like in your life.
By broaching the subject in this way, the counselor can intentionally assess the impact of a specific social determinant on the client’s overall well-being and health. In the example, the counselor would seek to understand the quantity, quality, and impact of the client’s relationships while also screening for any potential physical symptoms that might require an external referral. This practice of broaching SDoMH through client psychoeducation and assessment allows the counselor to implement data-driven practices that provide a multitiered therapeutic framework to conceptualize client concerns across various socioecological levels (e.g., individual, interpersonal, community, public policy). This in turn supports the development of a more holistic treatment plan that incorporates both individual and community interventions.
Figure 1
Visual Depiction of the Social Determinants of Mental Health for Clinical Use
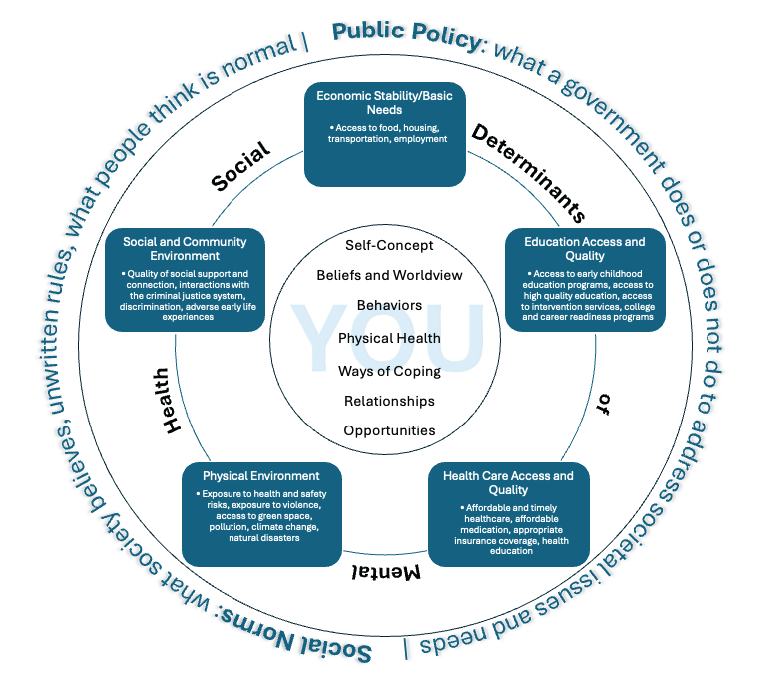
Note. Adapted from Social Determinants of Health, by Office of Disease Prevention and Health Promotion, 2025 (https://odphp.health.gov/healthypeople/objectives-and-data/social-determinants-health) and “Social Determinants of Mental Health” by Compton, M. T., & Shim, R. S., 2015, Focus, 13(4), p. 420 (https://doi.org/10.1176/appi.focus.20150017).
Contextualizing SDoMH for Each Client
As a client develops understanding and awareness of the social determinants impacting their well-being, the counselor should also use broaching to contextualize that knowledge on an individual level. In this way, counselors go beyond educating clients about SDoMH in general and instead seek to collaborate with the client to understand how they are uniquely impacted by those factors. This practice of contextualizing SDoMH allows the client to make connections between their lived experiences, intrapsychic concerns, and the larger social and environmental context.
This broaching behavior aligns well with the MMBB and its intraindividual, intra-REC, and inter-REC broaching dimensions. Counselors can apply these broaching dimensions to the contextualization process. For example, intraindividual broaching can be used to acknowledge how SDoMH impact a client’s identity dimensions (e.g., race, gender, socioeconomic status, sexual orientation, immigration status). A counselor could say, “It sounds like financial strain has limited your transportation options to get to your appointments. Let’s find some free or low-cost alternatives that might better fit within your budget.” Intra-REC broaching, or the exploration of within–cultural group concerns, can help the counselor discuss any client issues impacted by SDoMH that are culture-specific. A counselor might say to the client, “I imagine it could be difficult to ask family and friends for a ride to your appointments if mental health is stigmatized in those relationships.” Finally, a counselor may apply inter-REC broaching by exploring a client’s experiences with discrimination:
Relying on public transportation resources in this city has caused you to miss important appointments and events. It sounds like these public resources don’t meet the needs of residents. I plan to write a letter to the city council explaining some of the issues. Is there anything specific that you would like me to communicate or any way that you would like to advocate for changes?
By integrating these specific broaching dimensions, counselors can help clients gain both self and situational awareness by better understanding the possible role of social determinants in their own lives. In turn, this allows the counselor and client to better address challenges by understanding the client’s unique needs in context. From the previous example, the counselor might consider the following: Does the client need help identifying additional transportation resources? Would virtual counseling sessions be a more accessible option? Can I advocate for improved public transportation in the local community by providing key context to local leaders about how unreliable transportation affects the health of their constituents? Are there self-advocacy skills that I could help the client develop? Through targeted discussions on SDoMH like these, counselors can ensure that they are providing culturally responsive care that meets their clients’ unique needs.
Broaching Differences in the Counselor–Client Relationship
As SDoMH factors are integrated into the therapeutic process, counselors must also attend to the interpersonal process of the therapeutic alliance by intentionally broaching any differences that may exist between the counselor and client. Clients from historically marginalized backgrounds may experience factors that may differ significantly from their counselor’s lived experiences, such as heightened economic instability, community violence, and health care barriers (Compton & Shim, 2015). The MMBB, through its intracounseling domain, emphasizes that a counselor must actively acknowledge and explore REC differences between the counselor and client to attend to any disruptive interpersonal processes that might impact the therapeutic relationship (Day-Vines et al., 2020). We suggest that differences in lived experience related to SDoMH be treated comparably to ensure culturally responsive and effective care.
Research suggests that counselors who fail to broach REC concerns and SDoMH-related disparities risk reinforcing dominant cultural narratives that dismiss or minimize the structural challenges clients face, potentially leading to client disengagement, cultural miscommunication, and premature termination of counseling services (Day-Vines et al., 2021; Drinane et al., 2018; Owen et al., 2014). Thus, it is incumbent upon counselors to broach these differences with cultural humility, openness, and a willingness to engage in difficult but necessary conversations (Newton & Steele, 2025). To effectively broach these conversations, a counselor should adopt a collaborative, client-centered approach by acknowledging potential differences in lived experiences while affirming the client’s perspective.
One strategy is for the counselor to invite open discussions by saying:
I recognize that my experiences may be different from yours, and I don’t want to make assumptions about the challenges that you face. I’d like to understand more about how factors like financial stress, health care access, or discrimination may be affecting your mental health. Would you be open to sharing what that has been like for you?
This type of broaching explicitly acknowledges differences in identity, privilege, and lived experience between the counselor and client while creating a nonjudgmental and validating therapeutic space for the client to share their reality (Day-Vines et al., 2021).
Another example of effective intracounseling broaching can be seen in a case where a White counselor works with a Black client who describes frequent racial discrimination in the workplace. To avoid deflecting or minimizing the client’s experience, the counselor might say, “I want to acknowledge that my lived experience may not reflect what you’re describing, but I want to understand how these challenges impact your well-being.” This affirming, non-defensive approach allows for deeper exploration of SDoMH factors such as racial stress, economic opportunity, and access to mental health care (Newton & Steele, 2025). Such intentional broaching behaviors can also help mitigate client mistrust, validate sociocultural realities, and strengthen the therapeutic alliance (Day-Vines et al., 2021).
Building rapport and trust is central to the broaching process, particularly when addressing systemic disparities. Trust building requires empathy, active listening, and a willingness to acknowledge one’s own biases (Day-Vines et al., 2021). Integrating clients’ interests, cultural values, and lived experiences into sessions makes counseling more relevant, while creating a safe space grounded in unconditional acceptance encourages openness and authenticity. Together, these broaching practices foster trust, empower clients to take an active role in the process, and strengthen the foundation for growth and change.
Broaching Emergent Needs in Session
Counselors should also be mindful to broach emergent client needs throughout the therapeutic process. Though counselors may assess clients for SDoMH at the beginning of the counseling process, that information must be viewed within a dynamic client context that requires an ongoing response rather than a one-time assessment. Therefore, counselors must remain attuned to emerging SDoMH needs throughout the therapeutic process and utilize immediacy skills to broach and address concerns as they arise.
Many clients face barriers related to income, health care access, transportation, and social support networks, all of which can create stressors that directly influence mental health outcomes because they add layers of stress that can overshadow therapeutic work (Compton & Shim, 2015). When basic needs are not met, clients may experience heightened anxiety, hopelessness, or distraction, which can limit their ability to fully engage in treatment.
Ongoing systemic barriers can also reinforce feelings of disempowerment and make it harder for clients to trust the counseling process or believe change is possible. As a result, unresolved SDoMH challenges often lead to inconsistent attendance, premature termination, or reduced treatment effectiveness. By addressing these barriers within the counseling process, counselors not only improve client retention and engagement but also enhance overall wellness by affirming that external stressors are legitimate and integral to mental health care.
For example, a client who discloses heightened anxiety over an overdue utility bill may struggle to engage in therapy until the pressing financial stressor is addressed. A counselor might broach this concern by saying, “I can see how this situation is overwhelming and I want to support you in finding a solution. Would it be helpful to take a few minutes to explore assistance programs or a payment plan?” This response validates the client’s distress while offering immediate, actionable support to address a pressing external challenge. Similarly, a client struggling with transportation barriers may benefit from a session in which the counselor helps them identify local transit options, employer benefits, or community-based ride services to ensure consistent access to mental health care. Meeting such immediate, concrete needs within the session fosters greater trust, retention, and engagement in the counseling process (Day-Vines et al., 2021; Newton & Steele, 2025). Additionally, addressing pressing SDoMH concerns in real time reinforces the message that both psychological distress and external stressors are valid therapeutic concerns. This approach ensures that counseling remains responsive and supportive of the client’s holistic well-being.
Beyond directly helping clients address pressing needs in session, the counselor can support self-advocacy and empowerment by equipping clients with the knowledge and skills to independently resolve their emergent needs. Developing self-advocacy skills enables clients to engage more effectively with health care providers, employers, and social service agencies providing skills that bridge the counseling office into everyday life (Compton & Shim, 2020). Self-advocacy intervention empowers clients to actively pursue resources, assert their rights, and confront systemic barriers with confidence. Moreover, self-advocacy skills foster resilience and equip clients to not only overcome immediate obstacles but to also sustain progress in the face of future challenges. In this way, developing self-advocacy skills is not just a counseling technique but a vital outcome that supports long-term growth and empowerment.
The counselor can facilitate the development of self-advocacy skills by helping clients identify resources, role-play difficult conversations, and anticipate potential barriers they may encounter when seeking support. For example, a client experiencing housing insecurity may feel intimidated about reaching out to a local housing agency because of past negative experiences or uncertainty about eligibility requirements. A counselor might role-play the conversation by saying, “Let’s practice how you might explain your situation when calling the housing agency. You could start by saying, ‘I’m looking for assistance with securing stable housing. Can you help me understand the eligibility requirements and next steps?’” This approach allows the client to rehearse the interaction in a supportive setting, boosting their confidence before making the actual call. Additionally, the counselor can help the client identify potential challenges, such as long wait times or required documentation, and develop strategies to navigate them, ensuring that they feel prepared and empowered when seeking resources.
Through active collaboration, counselors can help clients recognize their strengths; build resilience to adapt, recover, and grow when faced with adversity; and gain confidence in advocating for themselves in settings that may otherwise feel disempowering. This approach fosters an environment where clients feel seen, supported, and empowered to navigate both personal and systemic challenges as they arise.
Termination Considerations
Finally, SDoMH need to be broached in the context of termination because of their impact on client dropout rates and early termination of treatment (Roberts et al., 2022). Although counselors are traditionally taught that termination should be gradual and that clients should share readiness, that is not always the reality because of the influence of social determinants. For example, electricity or phone service may be terminated because of an inability to pay bills, thereby limiting the client’s access to virtual sessions; limited transportation or childcare may prevent continued session attendance. Although counselors hope that they will be able to have a final session, that is not always realistic.
Nevertheless, the termination period represents a critical phase of the clinical process and must be attended to as part of the counseling process (Baum, 2005; Goode et al., 2017; Knox et al., 2011; Lee et al., 2023; Vasquez et al., 2008). Therefore, incorporating SDoMH broaching behaviors throughout the counseling relationship lays the foundation for effective clinical termination, even if termination occurs prematurely. For example, enhancing skills such as self-advocacy and incorporating discussions of resource identification and utilization can help empower clients in the event of unexpected termination.
When a formal termination is possible, continuing to broach SDoMH throughout that process can strengthen therapeutic gains and enhance overall therapeutic outcomes. As such, a counselor may engage clients in discussions around how SDoMH have impacted their therapeutic experience and goal attainment during counseling. This conversation can extend to how SDoMH may influence goal attainment after counseling, including brainstorming potential challenges that may arise. Discussions around how to apply skills gained during counseling to navigate those challenges and address relevant social determinants can also be impactful.
Additionally, a counselor should recognize that clients who discontinue care because of SDoMH-related barriers may choose to reengage in counseling once those barriers have been resolved. Thus, using a screen door approach (Pester Boyd et al., 2025) to termination can be helpful. This may include broaching the process of how clients can return to counseling (e.g., whether a new intake is required, potential waitlist considerations), available options for returning (e.g., in person, telehealth, in-home), and factors that might warrant reengagement in counseling.
Broaching SDoMH during termination should also include providing and discussing a list of referrals and resources to support clients beyond counseling. These resources should address both immediate mental health needs and the social determinants that impact overall well-being. Clients may wish to discuss these referrals and resources further to better understand the process of accessing them. This may include empowering clients with language they can use in various settings, such as navigating legal, social services, or medical resources, or even role-playing those conversations.
Given the potential role of SDoMH in early termination, such discussions should begin early in the clinical process. For example, a counselor might say, “You mentioned concerns that you may lose your health insurance. Can we talk through what that may look like if that were to happen?” This helps the counselor address factors related to counseling and mental health while also helping the client brainstorm challenges, solutions, and resources. Using the other SDoMH broaching behaviors to sustain these conversations throughout the counseling process can lead to effective client termination, even if termination occurs unexpectedly.
SDoMH Broaching Behaviors and Counselor Education
There is a growing call within counseling and related mental health fields to enhance SDoMH training and increase counselor readiness to broach these topics in practice (Gantt-Howrey et al., 2024; Johnson & Robins, 2021; Newton & Steele, 2025; Pester Boyd et al., 2025). As such, counselor education programs at the master’s and doctoral levels should incorporate discussion and clinical practice opportunities to help counselors-in-training (CITs) build awareness of SDoMH and develop best practices for broaching and addressing their impact on client well-being. Counselor education programs can embed SDoMH broaching across coursework, supervision, and experiential learning to prepare CITs for ethical and effective practice.
Integrating SDoMH in Coursework and Supervision
SDoMH training may be integrated in a number of counselor education courses and aligns with Council for the Accreditation of Counseling and Related Educational Programs (CACREP; 2023) standards (Gantt-Howrey et al., 2024; Pester Boyd et al., 2025). For example, suggested activities per course/CACREP core area include: (a) examining ethical considerations of broaching SDoMH, including advocacy responsibilities and potential boundary issues when addressing systemic barriers (i.e., professional orientation and ethics); (b) helping CITs connect the MSJCC to SDoMH through case study analysis (i.e., social and cultural diversity); (c) highlighting how developmental outcomes are shaped by SDoMH (i.e., human growth and development); (d) addressing how economic stability, employment, and educational inequities intersect with career counseling (i.e., career development); (e) having CITs practice broaching SDoMH through role-plays to become aware of how SDoMH affects rapport, trust, and client disclosure (i.e., counseling and helping relationships); (f) integrating experiential activities in which students design psychoeducational groups focused on wellness promotion, social support, or navigating systemic barriers (i.e., group counseling and group work); (g) teaching CITs to administer and interpret SDoMH screening tools and to incorporate results into case conceptualizations (i.e., assessment and evaluation); and (h) requiring that CITs design projects to investigate the impact of SDoMH on client outcomes or evaluate community-based interventions (i.e., research and program evaluation).
In addition, practicum and internship supervision provides an important space for modeling SDoMH broaching and supporting CITs in developing cultural humility and ethical decision-making through structured activities. Supervisors might, for example, guide CITs in identifying protective factors through a strengths mapping exercise that charts client supports across individual, relational, community, and cultural identities. They can also facilitate role-plays in which CITs practice acknowledging the protective role of extended family, religious communities, cultural traditions, or neighborhood engagement. Site supervisors may also connect practicum activities to systemic issues, such as collaborating with schools or agencies on wellness or resource initiatives. Finally, reflective supervision discussions can help CITs analyze their own responses to client strengths and SDoMH barriers and notice whether they default to problem-solving or strength-building.
SDoMH Broaching in Experiential Learning
Experiential activities provide CITs with opportunities across coursework, practicum, and internship to connect theory to practice. Experiential activities may include case analysis, role-plays, assessment practice, community engagement, and classroom discussions focused on ethical dilemmas. First, CITs can analyze case vignettes to examine how SDoMH affect individuals and families. For example, dyads might review a case through the lens of a specific determinant such as housing insecurity or underemployment, discuss the client’s presenting concerns in context, and brainstorm broaching strategies. Second, structured role-plays further allow students to develop confidence in directly addressing SDoMH with clients. For example, in triadic supervision, CITs can rotate roles as counselor, client, and observer, while peers and supervisors provide feedback on the clarity and effectiveness of broaching behaviors.
Third, assignments that incorporate SDoMH assessment tools (e.g., PRAPARE, WE CARE Survey) also prepare CITs to integrate systemic factors into case conceptualization. CITs may practice administering and interpreting screeners with hypothetical clients and then learn to translate results into simple, jargon-free explanations for use in sessions. Fourth, community engagement projects deepen this preparation by connecting CITs to the systemic realities clients face. Examples include researching local issues such as food insecurity and mapping neighborhood resources.
Ethical reflection is also a part of experiential learning. Classroom discussions may explore balancing advocacy efforts with professional boundaries or managing countertransference when counselors share similar systemic challenges with their clients. In addition, classroom dialogue can highlight positive determinants of mental health by fostering empathy and compassion. Storytelling circles or guided conversations can invite CITs to share their own lived experiences of belonging or exclusion and consider how these experiences influence their empathy and ethical decision-making.
Cultural humility is the foundation for effective SDoMH broaching. To strengthen cultural humility and responsiveness, counselor education programs can embed the abovementioned experiential learning strategies across coursework and supervision. Self-reflection exercises may include journaling prompts such as: “What identities give me privilege and how might that shape my assumptions with clients?”; “How have I responded when a client’s worldview or values conflicted with my own? What could I do differently to remain open and nonjudgmental?”; and “Recall a time you felt excluded, misunderstood, or powerless. How does that experience shape your empathy for clients navigating systemic inequities?” These reflections can be revisited across the program to track growth in self-awareness and cultural responsiveness.
Guided discussions can be facilitated through fishbowl discussions in which CITs share and listen to experiences of privilege, discrimination, or cultural differences, followed by role-plays that practice broaching these issues in counseling. Counselor educators can model effective broaching and provide feedback on student language and presence during these exercises.
Promoting Positive Social Determinants
In addition to addressing negative SDoMH (e.g., discrimination, housing insecurity, poverty, community violence), counselor educators can help CITs recognize and promote positive SDoMH that build resilience. These determinants include self-care practices, strong social support, inclusive environments, cultural affirmation, and opportunities for growth and connection. In addition, counselor educators can model and encourage strengths-based approaches that affirm client identities, such as validating cultural, gender, or spiritual expressions, during intake and treatment planning.
Wellness models and self-care planning can be integrated into coursework to benefit both CITs and future clients. For example, assignments might include creating a personal self-care plan; evaluating wellness models and interventions across cultures; or designing a client-friendly handout that translates wellness strategies (e.g., mindfulness, exercise, nutrition, social connection) into accessible, culturally responsive language.
Counselor education programs can embed advocacy projects across coursework to promote systemic conditions that support mental health equity. Examples include partnering with schools to develop anti-bullying campaigns; creating culturally inclusive mental health awareness workshops for parents and teachers; and collaborating with community agencies to expand access in areas such as housing assistance, after-school programs, health care access, or transportation services. CITs might also design stigma-reduction campaigns with public health organizations.
Service-learning projects can further immerse students in community contexts by mapping resources, conducting needs assessments, or partnering with organizations addressing issues such as refugee resettlement, food insecurity, or housing justice. As service-learning projects conclude, CITs can be asked, “What systemic barriers did you observe and how might they affect mental health?”; “How did this experience shape your understanding of your role as advocate?”; and “How might insights from this project influence how you broach SDoMH with clients in practice?”
Preparing for SDoMH Broaching Challenges
Although broaching SDoMH is a critical counseling skill, CITs may face obstacles when attempting to apply it in future practice. Agency settings may limit the time available to explore systemic issues, and some trainees may feel anxious about making missteps when discussing topics such as poverty, discrimination, or community violence. Clients themselves may hesitate to disclose experiences of marginalization out of fear of judgment or because such issues have been dismissed in past encounters with helping professionals.
Counselor educators can support student development by intentionally acknowledging these challenges within the classroom and supervision spaces. For example, they might facilitate a structured dialogue in which CITs share their concerns about broaching while the counselor educator normalizes discomfort and models language for difficult conversations. In these dialogues, they might ask CITs, “What feelings come up for you when you think about broaching SDoMH with a client?”; “What makes these conversations challenging in practice?”; or “How might you respond if a client resists or shuts down when SDoMH are introduced?” Such discussions can help trainees recognize that hesitation is common and that growth comes from practice and feedback rather than perfection.
Another way to strengthen readiness is through guided debriefing of role-plays or client simulations. After a broaching exercise, counselor educators can ask CITs to reflect on moments in which they felt stuck, explore how power dynamics may have shaped the exchange, and brainstorm alternative approaches. For instance, a CIT might role-play broaching transportation barriers with a hypothetical client who frequently misses sessions. After the role-play, other CITs within the classroom or supervision session could examine the CIT’s wording and the client’s reaction and then suggest alternative ways to frame the issue that both validate the client’s struggle and highlight systemic factors.
Counselor educators can also discuss the limitations of broaching within supervision. When reviewing case presentations, supervisors might ask CITs not only how they addressed SDoMH but also what structural limitations they encountered and how those shaped the counseling process. For example, a CIT might describe working with a client who lacked consistent childcare and therefore missed several sessions. The supervisor could guide the student to consider how systemic gaps in affordable childcare both constrained the counseling process and required exploration of advocacy or referral options. These conversations emphasize that although broaching can validate client experiences, it cannot by itself dismantle inequities, thus highlighting the importance of community collaboration and ongoing advocacy. As counselor educators intentionally and thoroughly analyze the process together, CITs can learn to approach barriers not as failures but as opportunities to deepen cultural humility.
Evaluating SDoMH Broaching Behaviors
Currently, there are no existing measures to evaluate SDoMH broaching behaviors, and future research should prioritize the development of validated tools to assess both counselor competency in SDoMH broaching and client perceptions of these efforts. Quantitative studies could focus on designing and testing new measures that assess the clarity, timing, cultural responsiveness, and impact of SDoMH broaching within the counseling relationship. Counseling researchers could utilize these instruments to conduct longitudinal studies and controlled intervention studies exploring the influence that SDoMH broaching has on client trust, client engagement in counseling, and therapeutic outcomes.
Until instruments specific to SDoMH broaching have been developed, researchers can use existing scales that independently measure broaching behaviors (e.g., Day-Vines et al., 2013; Day-Vines et al., 2024), SDoMH readiness (e.g., Johnson, 2023) and SDoMH assessment (e.g., Gantt-Howrey et al., 2024) to understand effective counseling behavior related to these constructs.
In addition to quantitative approaches, qualitative studies can help inform the impact of broaching behaviors on clients, CITs, and counselors. Studies that explore client experiences with counselors who broach SDoMH can provide contextual nuance and enhance multiculturally competent practice. For instance, interviews or focus groups with clients might uncover how broaching influences their feelings of safety, empowerment, or stigma reduction. Furthermore, researchers could conduct case studies of counselors in varied settings to examine how SDoMH broaching unfolds in practice. Data from session transcripts and client and counselor interviews could reveal additional best practices for addressing SDoMH, promoting positive social determinants, and counteracting challenges that counselors may have while broaching SDoMH.
Conclusion
Learning to effectively broach SDoMH provides an opportunity for counselors to further operationalize Ratts et al.’s (2016) MSJCC. As the cross-disciplinary call for universal SDoMH screening practices continues to grow across health professions, to remain leaders among the mental health professions, counselors must begin intentionally broaching SDoMH with clients. However, as a profession, broaching SDoMH may require reexamining the professional counselor identity, expanding advocacy roles, and reviewing ethical standards that may inadvertently create barriers to effectively addressing the impact of social determinants on clients’ lives.
Preliminary research suggests that effectively broaching SDoMH throughout the counseling process supports a number of short- and long-term benefits to clinical practice, which warrants its further integration and evaluation in the counseling profession. Counselors perceive that in the short term, broaching SDoMH strengthens the therapeutic relationship while fostering MSJCC (Pester Boyd et al., 2025). These early benefits can give way to enhanced client empowerment and improved access to interprofessional resources and services, both of which can lead to better treatment outcomes. Long-term, effectively broaching SDoMH can result in improved overall health of the client, improved community health, and decreased marginalization.
The MMBB (Day-Vines et al., 2020) and SDCM (Pester Boyd et al., 2025) provide needed frameworks to enhance these client outcomes. Using the integration of these frameworks as a foundation, we identified six SDoMH broaching behaviors for counselors: (a) counselor development, (b) client psychoeducation, (c) contextualization, (d) attending to differences of lived experience, (e) addressing emergent needs, and (f) SDoMH-informed termination practices. These broaching behaviors provide specific guidance for how to integrate SDoMH into counseling practice, which operationalizes the mandate of the MSJCC to address systemic and environmental factors impacting client mental health. We suggest that counselors integrate the identified SDoMH broaching behaviors throughout all stages of the therapeutic process to support a strong counselor–client relationship, enhanced client self-disclosure, increased client satisfaction, and improved therapeutic outcomes.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
Baum, N. (2005). Correlates of clients’ emotional and behavioral responses to treatment termination. Clinical Social Work Journal, 33(3), 309–326. https://doi.org/10.1007/s10615-005-4946-5
Brookover, D. L. (2024). The career development and social determinants framework: An integrative approach. Professional School Counseling, 28(1), 1–12. https://doi.org/10.1177/2156759X241290494
Center for Medicare & Medicaid Innovation. (n.d.). The accountable health communities health-related social needs screening tool. https://innovation.cms.gov/files/worksheets/ahcm-screeningtool.pdf
Compton, M. T., & Shim, R. S. (2015). The social determinants of mental health. Focus, 13(4), 419–425. https://doi.org/10.1176/appi.focus.20150017
Compton, M. T., & Shim, R. S. (2020). Why employers must focus on the social determinants of mental health. American Journal of Health Promotion, 34(2), 215–219. https://doi.org/10.1177/0890117119896122c
Council for the Accreditation of Counseling and Related Educational Programs. (2023). 2024 CACREP standards. https://www.cacrep.org/wp-content/uploads/2024/04/2024-Standards-Combined-Version-4.11.2024.pdf
Day-Vines, N. L., Bryan, J., and Griffin, D. (2013). The Broaching Attitudes and Behavior Survey (BABS): An exploratory assessment of its dimensionality. Journal of Multicultural Counseling and Development, 41(4), 210–223. https://doi.org/10.1002/j.2161-1912.2013.00037.x
Day-Vines, N. L., Cluxton-Keller, F., Agorsor, C., & Gubara, S. (2021). Strategies for broaching the subjects of race, ethnicity, and culture. Journal of Counseling & Development, 99(3), 348–357. https://doi.org/10.1002/jcad.12380
Day-Vines, N. L., Cluxton-Keller, F., Agorsor, C., Gubara, S., & Otabil, N. A. A. (2020). The multidimensional model of broaching behavior. Journal of Counseling & Development, 98(1), 107–118. https://doi.org/10.1002/jcad.12304
Day-Vines, N. L., Zhang, J., Cluxton-Keller, F., Hicks, D., Jones, C., Spann, R. T., Daga, D., & Agorsor, C. (2024). The development and validation of an instrument to examine clients’ perspectives about their counselors’ ability to broach racial, ethnic, and cultural concerns. Journal of Multicultural Counseling and Development, 52(3), 173–188. https://doi.org/10.1002/jmcd.12300
Depauw, H., Van Hiel, A., Talal, H., Dierckx, K., Geenen, F., Valcke, B., & De Clercq, B. (2025). The development of the Broaching Assessment Scale: A client-rated measure of therapists’ broaching behaviour in clinical counselling. Psychotherapy Research, 35(3), 424–440. https://doi.org/10.1080/10503307.2024.2301948
Dolan, N., Simmonds-Buckley, M., Kellett, S., Siddell, E., & Delgadillo, J. (2021). Effectiveness of stress control large group psychoeducation for anxiety and depression: Systematic review and meta-analysis. British Journal of Clinical Psychology, 60(3), 375–399. https://doi.org/10.1111/bjc.12288
Drinane, J. M., Owen, J., & Tao, K. W. (2018). Cultural concealment and therapy outcomes. Journal of Counseling Psychology, 65(2), 239–246. https://doi.org/10.1037/cou0000246
Gantt-Howrey, A., Lin, M., Shaikh, A., Johnson, K. F., Preston, J. W., & Wilson, L. (2024). Assessing social determinants of mental health: Client experiences and counselor practices. Journal of Counseling & Development, 102(4), 394–405. https://doi.org/10.1002/jcad.12519
Garg, A., Butz, A. M., Dworkin, P. H., Lewis, R. A., Thompson, R. E., & Serwint, J. R. (2007). Improving the management of family psychosocial problems at low-income children’s well-child care visits: The WE CARE Project. Pediatrics, 120(3), 547–558. https://doi.org/10.1542/peds.2007-0398
Goode, J., Park, J., Parkin, S., Tompkins, K. A., & Swift, J. K. (2017). A collaborative approach to psychotherapy termination. Psychotherapy, 54(1), 10–14. https://doi.org/10.1037/pst0000085
Johnson, K. F. (2023). Development and initial validation of the Addressing Client Needs with Social Determinants of Health Scale (ACN: SDH). BMC Health Services Research, 23(1), 374. https://doi.org/10.1186/s12913-023-09292-z
Johnson, K. F., & Brookover, D. L. (2021). School counselors’ knowledge, actions, and recommendations for addressing social determinants of health with students, families, and in communities. Professional School Counseling, 25(1). https://doi.org/10.1177/2156759X20985847
Johnson, K. F., Cunningham, P. D., Tirado, C., Moreno, O., Gillespie, N. N., Duyile, B., Hughes, D. C., Scott, E. G., & Brookover, D. (2023). Social determinants of mental health considerations for counseling children and adolescents. Journal of Child and Adolescent Counseling, 9(1), 21–33. https://doi.org/10.1080/23727810.2023.2169223
Johnson, K. F., Gantt-Howrey, A., Duyile, B. E., Robins, L. B., & Dockery, N. (2024). Career counselors addressing social determinants of mental health in rural communities. The Professional Counselor, 14(1), 1–14. https://doi.org/10.15241/kfj.14.1.1
Johnson, K., & Robins, L. B. (2021). Counselor educators experiences and techniques teaching about social-health inequities. Journal of Counselor Preparation and Supervision, 14(4). https://research.library.kutztown.edu/jcps/vol14/iss4/ 7
King, K. M., & Borders, L. D. (2019). An experimental investigation of White counselors broaching race and racism. Journal of Counseling & Development, 97(4), 341–351. https://doi.org/10.1002/jcad.12283
Knox, S., Adrians, N., Everson, E., Hess, S., Hill, C., & Crook-Lyon, R. (2011). Clients’ perspectives on therapy termination. Psychotherapy Research, 21(2), 154–167. https://doi.org/10.1080/10503307.2010.534509
Lee, P.-S., Wang, L.-F., & Swift, J. K. (2023). Clients’ and counselors’ termination decisions and experiences in counseling. Current Psychology, 42, 3734–3744. https://doi.org/10.1007/s12144-021-01725-4
Lenz, A. S., & Lemberger-Truelove, M. E. (2023). The social determinants of mental health and professional counseling: A call to action. Journal of Counseling & Development, 101(4), 375–380. https://doi.org/10.1002/jcad.12489
Lenz, A. S., & Litam, S. D. A. (2023). Integrating the social determinants of mental health into case conceptualization and treatment planning. Journal of Counseling & Development, 101(4), 416–428. https://doi.org/10.1002/jcad.12487
Lund, C., Brooke-Sumner, C., Baingana, F., Baron, E. C., Breuer, E., Chandra, P., Haushofer, J., Herrman, H., Jordans, M., Kieling, C., Medina-Mora, M. E., Morgan, E., Omigbodun, O., Tol, W., Patel, V., & Saxena, S. (2018). Social determinants of mental disorders and the sustainable development goals: A systematic review of reviews. The Lancet Psychiatry, 5(4), 357–369. https://doi.org/10.1016/S2215-0366(18)30060-9
Luo, H., Li, Y. L., Luo, X. J., Xia, L., Xiao, J., Xiao, H., & Chen, J. (2025). The efficacy of psychoeducation-based programs on internalized stigma in patients with schizophrenia: A systematic review and meta-analysis. Psychiatry Research, 350, 116540. https://doi.org/10.1016/j.psychres.2025.116540
Mason, S., Ragan, M., Gilbert, S. H., & Lenz, A. S. (2023). Social determinants of mental health: Implications for measurement, research, and evaluation. Journal of Counseling & Development, 101(4), 440–448. https://doi.org/10.1002/jcad.12490
Neal Keith, S., Coleman, M. L., Hicks Becton, L. Y., & Springfield, J. (2023). Assessing the social determinants of mental health in counseling practice. Journal of Counseling & Development, 101(4), 381–391. https://doi.org/10.1002/jcad.12470
Newton, C., & Steele, J. M. (2025). The broaching readiness framework: A path for psychologists to embrace cultural opportunities. Counselling Psychology Quarterly, 38(4), 1135–1152. https://doi.org/10.1080/09515070.2025.2458034
Office of Disease Prevention and Health Promotion. (2025). Social determinants of health. https://odphp.health.gov/healthypeople/objectives-and-data/social-determinants-health
Owen, J., Tao, K. W., Imel, Z. E., Wampold, B. E., & Rodolfa, E. (2014). Addressing racial and ethnic microaggressions in therapy. Professional Psychology: Research and Practice, 45(4), 283–290. https://doi.org/10.1037/a0037420
Pester, D. A., Jones, L. K., & Talib, Z. (2023). Social determinants of mental health: Informing counseling practice and professional identity. Journal of Counseling & Development, 101(4), 392–401. https://doi.org/10.1002/jcad.12473
Pester Boyd, D. A., Hays, D. G., & Jones, L. K. (2025). Assessing and addressing social determinants of mental health in counseling: A grounded theory investigation. Journal of Counseling & Development, 103(4), 469–483. https://doi.org/10.1002/jcad.70003
PRAPARE. (2022). Protocol for responding to and assessing patient assets, risks, and experiences: Implementation and action toolkit. https://prapare.org/wp-content/uploads/2022/09/Full-Toolkit_June-2022_Final.pdf
Ratts, M. J., Singh, A. A., Nassar-McMillan, S., Butler, S. K., & McCullough, J. R. (2016). Multicultural and social justice counseling competencies: Guidelines for the counseling profession. Journal of Multicultural Counseling and Development, 44(1), 28–48. https://doi.org/10.1002/jmcd.12035
Roberts, T., Esponda, G. M., Torre, C., Pillai, P., Cohen, A., & Burgess, R. A. (2022). Reconceptualising the treatment gap for common mental disorders: A fork in the road for global mental health? The British Journal of Psychiatry, 221(3), 553–557. https://doi.org/10.1192/bjp.2021.221
Robins, L. B., Johnson, K. F., Duyile, B., Gantt-Howrey, A., Dockery, N., Robins, S. D., & Wheeler, N. (2022). Family counselors addressing social determinants of mental health in underserved communities. The Family Journal, 31(2), 213–221. https://doi.org/10.1177/10664807221132799
U.S. Department of Health and Human Services. (2023). Our epidemic of loneliness and isolation: The U.S. Surgeon General’s advisory on the healing effects of social connection and community. https://www.hhs.gov/sites/default/files/surgeon-general-social-connection-advisory.pdf
Vasquez, M. J. T., Bingham, R. P., & Barnett, J. E. (2008). Psychotherapy termination: Clinical and ethical responsibilities. Journal of Clinical Psychology, 64(5), 653–665. https://doi.org/10.1002/jclp.20478
World Health Organization. (2025). Social determinants of health. https://www.who.int/health-topics/social-determinants-of-health#tab=tab_1
Zhang, N., & Burkard, A. W. (2008). Client and counselor discussions of racial and ethnic differences in counseling: An exploratory investigation. Journal of Multicultural Counseling and Development, 36(2), 77–87. https://doi.org/10.1002/j.2161-1912.2008.tb00072.x
Danielle Pester Boyd, PhD, NCC, LPC (TX), RPT, is an assistant professor at Auburn University. Laura K. Jones, PhD, is an associate professor at the University of North Carolina at Asheville. Courtney Maier, MEd, NCC, APC, is a doctoral student at Auburn University. Danica G. Hays, PhD, is a dean and professor at the University of Nevada Las Vegas. Correspondence may be addressed to Danielle Pester Boyd, 345 West Samford Avenue, Suite 3188, Auburn, AL 36849, danielle.boyd@auburn.edu.
Apr 1, 2026 | Volume 16 - Issue 1
Brian J. Clarke, Michael T. Hartley, Austin M. Guida
Impostor phenomenon (IP), characterized by persistent self-doubt despite objective success, is prevalent during the early stages of counselor development, often emerging as individuals transition from training into professional practice. This study examined whether self-compassion mediates relationships between IP, resilience, and mental health among 281 counselors-in-training enrolled in departments accredited by the Council for the Accreditation of Counseling and Related Educational Programs. Mediation analyses showed that self-compassion fully mediated the effects of IP on resilience and depression and partially mediated the effect on anxiety. MANOVA results indicated that higher self-compassion corresponded with lower IP, anxiety, and depression, and greater resilience, with robust effects. Findings identify self-compassion as a developmental competency that supports balanced self-evaluation, emotional regulation, and sustainable counselor well-being. Integrating self-compassion training into counselor education and supervision may help developing counselors manage impostor-related distress, strengthen resilience, and promote ethical, sustainable professional practice.
Keywords: impostor phenomenon, counselor development, self-compassion, resilience, mental health
Building resilience and prioritizing mental health are vital during the formative stages of counselor development. During the early stages of training and supervised practice, developing counselors experience the inherent emotional demands and elevated anxiety common while learning to integrate theoretical knowledge into clinical practice (Skovholt & Trotter-Mathison, 2024; Stoltenberg & McNeill, 2010). Although these feelings may diminish with increased experience, enduring self-doubt and inadequacy may signal impostor phenomenon (Clance & Lawry, 2024). Imposter phenomenon (IP), characterized by persistent feelings of fraudulence and incompetence despite evidence of success, impacts nearly all developing counselors (Clarke et al., 2025; Tigranyan et al., 2021). Those experiencing IP may struggle to internalize mastery experiences and fail to consolidate moments of success into genuine confidence (Gadsby & Hohwy, 2024; Roskowski, 2010). Individual differences in coping with IP may be partially explained by self-compassion, which may buffer IP’s negative effects on counseling self-efficacy and well-being (Clarke et al., 2025).
The persistent fear of being exposed as a fraud becomes a harmful cycle whereby individuals ruminate on perceived shortcomings, discount positive feedback, and misattribute positive outcomes to external factors (Clance & Lawry, 2024). Behaviors associated with IP include extreme perfectionism, procrastination, and/or exhausting overpreparation, which can inhibit counselor development (Clarke et al., 2025; Nguyen, 2023). Because IP is rooted in shame and feelings of inadequacy, it contributes to isolation, burnout, and compassion fatigue (Garba et al., 2024; Ojeda, 2024).
IP undermines the reflective, relational, and self-evaluative capacities that are central to counselor development. Counselors who experience chronic self-doubt may hesitate to disclose errors in supervision, question their competence, and struggle to sustain resilience, patterns that can jeopardize client care and professional longevity (Delaney, 2018; Housenecht & Swank, 2022). Given the demands of counselor training and practice, protective factors such as resilience and self-compassion may be critical for developing counselor well-being and persistence.
Resilience is a protective factor to cope with mental distress and burnout (Gerber & Anaki, 2021; Webb & Rosenbaum, 2019). Emerging from the positive psychology movement, resilience explains why some individuals behave adaptively under great stress while others do not. Beyond recovery from adversity, resilience is a process of successful adaptation and coping during challenging or threatening circumstances (Webb & Rosenbaum, 2019). Cultivating new coping mechanisms and fostering personal growth, resilience can sustain well-being and performance during difficult experiences. The limited research on resilience among developing counselors has identified self-awareness and self-compassion as critical protective factors to cope with the emotional demands of becoming a counselor (Hou & Skovholt, 2020).
As a protective factor, self-compassion can play an important role in the resilience and mental health of developing counselors, especially in the presence of IP (Clarke et al., 2025; Neff et al., 2005). Self-compassion is comprised of three interrelated dimensions: mindfulness, common humanity, and self-kindness (Neff, 2023). Mindfulness, the core of self-compassion, involves maintaining awareness of present experiences with reduced reactivity and self-judgment. The common humanity dimension refers to the acceptance that suffering is inherent to our shared human experience. By normalizing challenging experiences, this perspective helps prevent the isolation that may arise from perceiving failures as uniquely personal. Finally, self-kindness encompasses behaviors and ways of relating intrapersonally that offer support and comfort during times of suffering or setbacks. Rather than defaulting to self-criticism, overidentification with failures, or isolation, self-compassion enables understanding and resilience, reducing the impact of IP and the fear of failure during counselor development (Clarke et al., 2025; Warren et al., 2016).
The theoretical alignment between self-compassion and resilience is rooted in their shared emphasis on adaptive emotional regulation, growth through adversity, and the development of a stable and supportive inner identity (Warren et al., 2016). Self-compassion supports sustainable resilience by reducing self-criticism and perfectionism and fostering a growth mindset (Neff, 2023; Warren et al., 2016). Indeed, a recent meta-analysis indicated that self-compassion is consistently linked to positive outcomes among mental health professionals, including enhanced competence, improved therapeutic presence, and a greater willingness to seek guidance and supervision (Crego et al., 2022).
Because of its regulating effects, self-compassion may help developing counselors to tolerate the stress of IP through improved emotional self-regulation (Crego et al., 2022; Neff, 2023). In this way, self-compassion can function as an emotion-focused coping mechanism that reduces the mental distress associated with IP (Clarke, 2024; Crego et al., 2022; Gerber & Anaki, 2021). Ultimately, when individuals experience IP-related distress, self-compassionate responses (mindfulness, common humanity, self-kindness) may interrupt the IP cycle, preserving resilience and mental health (Neff et al., 2005).
The purpose of this study is to examine how self-compassion functions as a protective factor in the relationship between IP, resilience, and mental health during counselor development. Research has found self-compassion to support resilience among health care providers (Delaney, 2018), yet much less is known about the relationship between self-compassion and resilience among developing counselors who experience IP. Addressing the negative impact of IP on counselor development, this article explores how self-compassion might mitigate IP’s negative relationships with resilience and mental health (Clarke et al, 2025; Roskowski, 2010; Tigranyan et al., 2021). The guiding research questions were:
- To what extent does self-compassion mediate the relationships between IP and the outcomes of resilience and mental health?
- How do levels of self-compassion relate to variations in IP, resilience, and mental health among the sample?
We hypothesized that IP would have a significant negative relationship with resilience and mental health, and that self-compassion will significantly mediate these negative associations. Specifically, higher levels of self-compassion will relate to lower IP and improved mental health and resilience. Our findings offer valuable insights into how self-compassion can enhance resilience and promote mental health during counselor development.
Methods
Procedure
The study received IRB approval prior to the recruitment of master’s-level counseling students from across the United States. Data were collected between April and October 2023, using an online survey disseminated via email to Council for the Accreditation of Counseling and Related Educational Programs (CACREP)–accredited program liaisons. These emails described the study and outlined informed consent procedures and inclusion criteria. Eligible participants were individuals enrolled in CACREP-accredited counseling programs aged 18 or older. After consenting, participants were presented with the measures and a demographic questionnaire developed by the authors. Engagement with the study concluded once participants either completed or exited the survey.
Participants
The sample consisted of 281 counseling students attending CACREP-accredited counseling programs from 37 U.S. states and the District of Columbia. Although the present sample consisted of counselors-in-training (CITs), the term developing counselors is used throughout this paper to reflect the broader developmental continuum that spans counselor training and early professional practice (Stoltenberg & McNeill, 2010).
Consistent with the population of CITs, most participants identified as White (n = 190, 67.29%) with lower percentages identifying as Hispanic or Latinx (n = 43, 15.2 %), Asian (n = 17, 6.0%), African American or Black (n = 13, 4.6%), multiracial (n = 13, 4.6%), American Indian or Alaskan Native (n = 3, 1.1%) and Middle Eastern (n = 2, 0.7%). The majority (n = 237, 83.7%) identified as female, with 32 (11.3%) identifying as male, 6 (2.1%) as non-binary, 4 (1.4%) as genderqueer, and 2 (0.7%) choosing not to disclose their gender identity. Participants were from clinical mental health (n = 170, 60.1%), school counseling (n = 49, 17.3%), rehabilitation counseling (n = 49, 17.3%), and marriage and family counseling (n = 13, 4.6%) programs. The average participant age was 32 years (SD = 10.35), with an age range from 21 to 67 years.
Measures
Self-Compassion Scale-Short Form (SCS-SF)
The SCS-SF is a short form of the Self-Compassion Scale (Neff, 2003), consisting of 12 self-report items selected from the original scale (Raes et al., 2011). Items are rated on a 5-point Likert-type scale ranging from 1 (almost never) to 5 (almost always). Examples include “I try to see my failings as part of the human condition” and “I’m disapproving and judgmental about my own flaws and inadequacies” (Neff, 2003, p. 2). SCS-SF scores have shown good internal consistency (α = .86), with its total scores strongly correlating with those of the full version (r = .98; Raes et al., 2011). Factor analysis has confirmed that the SCS-SF shares the same factor structure as the original scale (Neff et al., 2019; Raes et al., 2011). Scores are interpreted as levels of self-compassion: low (1–2.4), moderate (2.5–3.5), and high (3.51–5). In the present study, SCS-SF scores demonstrated good internal consistency reflected in an alpha of .85, and omega of .85.
Academic Resilience Scale-6 (ARS-6)
The ARS-6 is a concise self-report scale designed to measure academic resilience, defined as the ability to manage challenges, stress, and setbacks within a learning environment (Martin & Marsh, 2006). Items include statements such as “I’m good at bouncing back from a poor grade or difficult feedback” and “I don’t let a bad grade or feedback affect my confidence.” Responses are rated on a 7-point Likert-type response scale ranging from 1 (strongly disagree) to 7 (strongly agree), with higher scores reflecting greater academic resilience. Item and factor level construct validity was supported through factor score estimates, correlation, path analysis, and cluster analysis, showing the ARS scores were closely aligned with related constructs including self-efficacy, control, planning, low anxiety, and persistence (Martin & Marsh, 2006). ARS-6 scores have demonstrated good internal consistency, with an alpha coefficient of .89 (Martin & Marsh, 2006). In the current study, the ARS-6 scores showed acceptable reliability supported by alpha and omega scores of .83.
Clance Impostor Phenomenon Scale (CIPS-10)
The CIPS-10 (Wang et al., 2022) is a condensed, 10-item version of the original 20-item Clance Impostor Phenomenon Scale (CIPS) designed to assess impostor feelings (Clance, 1985). A systematic review by Mak et al. (2019) supported the CIPS-20 as a valid (construct, criterion, and content) measure of IP. The CIPS-10 utilizes a Likert-type response scale ranging from 1 (not at all true) to 5 (very true) and includes items from the CIPS-20, such as “I’m afraid people important to me may find out that I’m not as capable as they think I am” and “I feel my success was due to some kind of luck rather than competence.” Wang et al. (2022) reported strong internal reliability for the CIPS-10 (α = .93), with total scores closely aligning with those of the CIPS-20. Construct validity was supported through factor score estimates, revealing a single-factor structure similar to the 20-item version. In this study, CIPS-10 scores were interpreted using adjusted categories from Clance (1985): few IP (less than 20), moderate IP (20–29), frequent IP (30–39), and intense IP (40–50). Within the current sample, CIPS-10 scores demonstrated good internal consistency with an alpha of .88 and omega of .90.
Patient Health Questionnaire-4 (PHQ-4)
The PHQ-4 is a 4-item, self-report assessment screening tool for depression and anxiety (Kroenke et al., 2009). The Likert-type responses are 0 (not at all), 1 (several days), 2 (more than half the days), and 3 (nearly every day). A total score of 3 or more, across both items, indicates the presence of moderate-to-severe symptoms (Kroenke et al., 2009). In meta-analyses, PHQ-4 scores have shown good internal consistency (α = .89) and have yielded valid and diagnostically accurate depression and anxiety scores (Khubchandani et al., 2016; Kroenke et al, 2009). Construct validity was supported using a varimax-rotated principal components analysis conducted on the four screening items (PHQ-2 and GAD-2), yielding two components that together explained 83% of the overall variance. Likewise, criterion validity was indicated by individuals diagnosed with depression or anxiety by a health care professional scoring significantly higher on the PHQ-2, GAD-2, and PHQ-4 compared to participants without a clinical diagnosis (Khubchandani et al., 2016). In the present sample, the PHQ-4 scores showed good internal consistency with an alpha score of .87 and omega of .84.
Data Analysis
Portions of this data set informed a previously published manuscript that focused on how self-compassion can mitigate IP’s negative relationship with counselor self-efficacy (Clarke et al., 2025). Although the two manuscripts share IP and self-compassion data, the current manuscript is distinct and extends this line of inquiry by its unique focus on the benefits of self-compassion for counselor resilience and mental health, despite the presence of IP.
All analyses were performed using SPSS (v29) with a p ≤ .01 benchmark to reduce the likelihood of Type I error and ensure that the most reliable effects are interpreted as statistically meaningful. Preliminary analyses were conducted to examine statistical assumptions for the mediation and MANOVA models. Normality was confirmed for all variables via Shapiro-Wilk (all p > .05). Box’s M test supported homogeneity of variance–covariance matrices (p = .021), and observations were independent. In addition to all VIF scores being < 2, no bivariate correlations exceeded r = .80, suggesting that multicollinearity was not a concern. Collectively, these results suggest that the data met all assumptions necessary for the planned analyses (Tabachnick & Fidell, 2019).
We selected a regression-based mediation analysis because of the study’s focus on specific indirect effects of self-compassion and the moderate sample size, both of which made alternative analyses less ideal (Hayes, 2022). Because the variables tested were represented by composite scores rather than latent constructs, a mediation was statistically appropriate and provided a parsimonious method to examine self-compassion as a buffer for IP. Although cross-sectional mediation cannot establish temporal precedence or causation, it can identify statistical pathways that warrant future longitudinal investigation (Fairchild & McDaniel, 2017; Hayes, 2022). The 99% confidence intervals (CI) of the effects were derived from 10,000 bootstrap samples. If the upper and lower bounds of the CI did not include zero, they were considered statistically significant.
Finally, MANOVA was used to determine how the severity of IP affected its relationships with resilience, anxiety, depression, and self-compassion. The four levels of IP used in this analysis were defined as few, moderate, frequent, and intense IP according to the CIPS author (Clance, 1985). MANOVA effect size was described using partial eta squared values of 0.01 (small), 0.059 (medium), and 0.14 (large; Richardson, 2011). Cohen’s d was used to interpret effect sizes for follow up Tukey analyses, small effect (d = 0.2), medium (d = 0.5), and large (d ≥ 0.8; Gignac & Szodorai, 2016).
A priori power analysis for mediation effects (Fritz & MacKinnon, 2007) indicated a minimum sample of 148 participants would provide .80 power to detect medium-sized indirect effects using bias-corrected bootstrapping. For MANOVA with three groups and four dependent variables, G*Power indicated 158 participants would yield .80 power for detecting medium effects (f² = .25). Our sample of 281 exceeded both requirements.
Results
Descriptives
Pearson correlations indicated significant (< .01) bivariate relationships among self-compassion, impostor phenomenon, depression, anxiety, and academic resilience (Table 1). There were no significant differences in self-compassion, IP, resilience, anxiety, or depression across demographics or counseling program emphasis.
Table 1
Descriptive Statistics and Bivariate Correlations
|
Mean |
SD |
1 |
2 |
3 |
4 |
|
| 1. Self-Compassion |
3.06 |
0.74 |
– |
|
|
|
| 2. Impostor Phenomenon |
32.81 |
8.22 |
−.54* |
– |
|
|
| 3. Depression |
1.27 |
1.60 |
−.42* |
.35* |
– |
|
| 4. Anxiety |
2.54 |
1.78 |
−.55* |
.46* |
.59* |
– |
| 5. Academic Resilience |
27.66 |
6.51 |
.53* |
−.36* |
−.23* |
−.40* |
*p ≤ .01.
The sample included high levels of impostor phenomenon (M = 32.81, SD = 8.22), with over 65% falling in the frequent-to-intense range. IP showed strong negative correlations with self-compassion (r = −.54) and resilience (r = −.36), and strong positive correlations with anxiety (r = .46) and depression (r = .35).
Mediation Analysis
Mediation analyses were used to explore the statistical associations among IP, self-compassion, and the outcome variables of resilience, anxiety, and depression. Results indicated that self-compassion functioned as a statistical mediator in the relationships between IP and each outcome.
Figure 1
Mediation Analysis: Impostor and Resilience
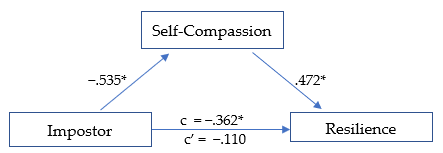
*p ≤ .01
The first model (Figure 1) was significant, R² = .290, F(1, 278) = 59.78, p < .01. The total effect (c) of IP on academic resilience was negative and significant, β = −.362, SE = .126, t = −2.868, p < .01, suggesting that higher IP scores were associated with lower resilience. When self-compassion was included in the model, the direct effect (c′) of IP on resilience was no longer significant, β = −.110, SE = .060, t = −1.838, p = .07, consistent with full statistical mediation (Hayes, 2022). The indirect pathway through self-compassion represented 69.6% of the total standardized association. IP was negatively associated with self-compassion (β = −.535, p < .01; large effect), and self-compassion was positively associated with resilience (β = .472, p < .01; large effect). The overall indirect effect was significant (β = −.252, p < .01).
Figure 2
Mediation Analysis: Impostor and Anxiety
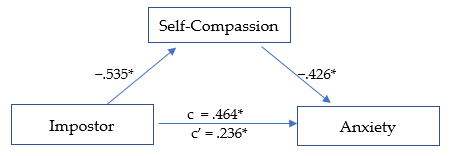
*p ≤ .01.
The second model (Figure 2) was significant, R² = .345, F(1, 278) = 73.159, p < .01. The total effect (c) of IP on anxiety was positive and significant, β = .464, SE = .053, t = 8.747, p < .01, indicating that higher IP scores were related to higher anxiety levels. After including self-compassion, the direct effect (c′) was reduced but remained significant, β = .236, SE = .057, t = 4.110, p < .01, suggesting partial statistical mediation. The indirect pathway through self-compassion accounted for 49.2% of the total standardized association. IP was negatively associated with self-compassion (β = −.535,p < .01; large effect), and self-compassion was negatively associated with anxiety (β = −.426, p < .01; medium effect). The overall indirect effect was significant, β = −.228, p < .01.
Figure 3
Mediation Analysis: Impostor and Depression
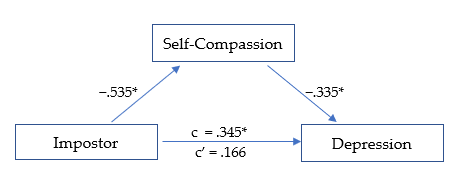
*p ≤ .01.
The third model (Figure 3) was significant, R² = .199, F(1, 278) = 34.484, p < .01. The total effect (c) of IP on depression was positive and significant, β = .345, SE = .056, t = 6.135, p < .01, indicating that higher IP scores were associated with higher depression levels. After accounting for self-compassion, the direct effect (c′) was reduced and no longer significant, β = .166, SE = .064, t = 2.611, p = .02, suggesting full statistical mediation. The indirect pathway through self-compassion represented 51.9% of the total standardized association. IP was negatively related to self-compassion (β = −.535, p < .01; large effect), and self-compassion was negatively related to depression (β = −.335, p < .01; medium effect). The overall indirect effect was significant, β = −.179, p < .01.
MANOVA
Self-compassion scores were divided into three levels (low, moderate, and high) as suggested by Neff (2003) to determine if the effect of self-compassion was consistent across each level. MANOVA analyses revealed that IP, resilience, depression, and anxiety each varied significantly based on level of self-compassion, F(8, 550) = 20.790, p < .01, Wilk’s Λ = 0.590, ηp2 = .232, indicating a large effect size.
The MANOVA results revealed that IP scores varied according to level of self-compassion, F(2, 281) = 48.807, p < .01, ηp2 = .260, with a large effect size. IP decreased significantly at each rising level of self-compassion, from low to moderate (d = 0.666, p < .01) and moderate to high (d = 0.987, p < .01), with medium and large effect sizes, respectively. The greatest decrease in IP was seen as self-compassion rose from moderate to high.
Resilience was significantly higher at each increasing level of self-compassion F(2, 281) = 39.323, p < .01, ηp2 = .221, with a large overall effect size. Resilience rose linearly across each level of self-compassion, from low to moderate (d = −0.756, p < .01), and from moderate to high (d = −0.790, p < .01), each with a medium-high effect size.
Depression scores lowered significantly as self-compassion level increased, F(2, 281) = 20.232, p < .01, ηp2 = .127, with an overall medium effect size. The decrease in depression was noted across levels of self-compassion, from low to moderate (d = 0.446, p < .01), and from moderate to high (d = 0.625, p < .01), each with a medium effect size. The largest decrease in depression was observed as self-compassion rose from moderate to high.
Anxiety scores decreased significantly as the level of self-compassion increased, F(2, 281) = 45.898, p < .01, ηp2 = .248, with a large overall effect size. Anxiety scores were lower as self-compassion rose from low to moderate (d = 0.895, p < .01), and from moderate to high (d = 0.711, p < .01), with large and medium effect sizes, respectively. The largest decrease in anxiety was noted as self-compassion increased from low to moderate.
Discussion
Our findings indicate that self-compassion is a strong protective factor and may enhance resilience and promote mental health among developing counselors, despite impostor feelings. Specifically, self-compassion fully mediated the negative relationship between IP, resilience, and depression, while partially mediating the relationship between IP and anxiety. This suggests that even when experiencing IP, higher self-compassion may help to maintain greater resilience and significantly reduced anxiety and depression. The results are promising and suggest that cultivating self-compassion may facilitate professional growth by interrupting the IP cycle. Our results offer further insights into how self-compassion can support resilience and mental health (Housenecht & Swank, 2022).
Descriptive Statistics
Descriptive analyses revealed a notably high prevalence of IP in the sample, with 96.1% (n = 270) reporting moderate to intense symptoms. Scores were skewed toward the higher end of the scale, with 65.1% of participants in the frequent-to-intense range and 21% in the highest category. Compared with earlier samples, these findings suggest that the severity of IP has increased substantially over the past 15 years (Roskowski, 2010; Tigranyan et al., 2021). For example, only 27.6% of a 2010 sample fell into the frequent-to-intense categories, compared with nearly two-thirds in the present study. Likewise, the proportion of students in the highest IP range has risen fivefold, from 4.1% in 2010 to 21% here. Although this increase may be influenced by broader cultural or educational factors, the trend underscores the importance of implementing effective coping strategies to support counselor well-being and persistence.
Consistently elevated IP scores across studies suggest that impostor feelings may be a common element of counselor development. Such feelings are often fueled by both internal and environmental pressures, particularly graduate students’ unreasonably high expectations of their performance and rapid development (Clance & Lawry, 2024). These unrealistic standards can generate unnecessary self-doubt, distorted self-assessments, and persistent self-criticism (Gadsby & Hohwy, 2024). Importantly, the current results indicate that self-compassion is a powerful counterbalance to IP. Higher self-compassion was associated with lower IP, anxiety, and depression, and with greater resilience, findings that align with previous research (Liu et al., 2023).
Mediation Models
Self-Compassion, IP, and Resilience
The first mediation analysis revealed that self-compassion fully mediated the negative relationship between IP and resilience. When accounting for self-compassion, the negative relationship between IP and resilience was rendered statistically non-significant. This outcome suggests that developing counselors with higher self-compassion may more easily adapt and recover when experiencing impostor-related distress. Self-compassion may assist key aspects of resilience, including stress management, coping with adversity, and maintaining a stable and supportive inner identity (Webb & Rosenbaum, 2019).
Although IP encourages harsh self-criticism and rumination on perceived failures, it is possible that through increased self-acceptance and soothing kindness, counselors can embody greater resilience when confronting areas of growth with less fear of failure. Additionally, a common humanity perspective can encourage acceptance of struggles as a normal part of counselor development and one shared by their peers. These soothing and normalizing aspects of self-compassion can encourage community rather than isolation when struggling, helping counselors to maintain resilience amidst adversity (Hou & Skovholt, 2020; Neff, 2023). Without effective coping practices, the challenges of counselor development can wear down resilience, creating vulnerability to mental distress, burnout, and counselor impairment (Cook et al., 2021; Gerber & Anaki, 2021).
Self-Compassion, IP, and Mental Health
Our results indicate that self-compassion is associated with less anxiety among those experiencing IP. Because anxiety is prevalent in this population and a primary emotional response to IP, efforts to increase self-compassion can have widely beneficial outcomes (Crego et al., 2022; Garba et al., 2024). The common humanity and mindfulness components of self-compassion may be critical to this outcome, as they can help limit emotional reactivity, normalize the IP experience, and reduce the isolation and fear of being exposed as an impostor (Clarke & Guida, 2025). This process involves mindfully recognizing that others share similar experiences and feelings, empowering developing counselors to seek support and reduce fear of failure (Neff, 2023). Likewise, practicing self-kindness may counter the harsh self-criticism associated with IP and encourage them to embrace the developmental process, including their imperfections (Patzak et al., 2017; Warren et al., 2016).
Anxiety and depression are closely linked and often co-occur (Beck & Alford, 2009). Though depression may not correlate as strongly with IP as anxiety does, it remains a common outcome (Garba et al., 2024). IP is persistent and sustained by cognitive distortions and misattributions, which also contribute to depressive thought patterns (Beck & Alford, 2009). However, our analysis revealed that self-compassion fully mediated the relationship between IP and depression. This suggests that a combination of mindful awareness and active self-kindness may facilitate more balanced self-assessment, countering perfectionism and harsh self-criticism commonly associated with IP (Clarke & Hartley, 2025; Pákozdy et al., 2023).
Although IP significantly predicted anxiety and depression, the buffering effect of self-compassion suggests that those with more compassionate self-perceptions may better tolerate the uncertainty and challenges common to counselor training. For example, those with a self-compassionate mindset may reinterpret failures as growth opportunities, a shift that may protect against anxious and depressive symptoms (Crego et al., 2022; Warren et al., 2016). These findings highlight the regulatory potential of self-compassion in reducing emotional reactivity to impostor-related distress.
Level of Self-Compassion in Relation to IP, Resilience, and Mental Health
MANOVA was utilized to determine whether the level of self-compassion (categorized as low, moderate, or high) was related to the level of IP, resilience, anxiety, and depression (Neff, 2003). Self-compassion had a significant positive relationship with mental health and resilience; however, the relationships varied significantly based on level of self-compassion (Figure 4). The results demonstrate that even lower levels of self-compassion were related to significantly lower IP, anxiety, and depression, as well as increased resilience. This pattern suggests that even modest improvements in self-compassion can correspond to improved well-being among developing counselors (Luo et al., 2023). For example, IP severity decreased significantly as self-compassion levels increased, revealing a linear reduction in IP from low to high self-compassion levels, with the most pronounced decrease occurring between the moderate and high categories.
Similarly, resilience scores also increased consistently across each level of self-compassion. The increase was linear, with the most substantial increase occurring when self-compassion rose from low to moderate. The steady increase in resilience across all self-compassion levels points to a possible dose-response relationship. Initial gains in self-compassion may bolster developing counselors’ ability to persevere through challenges (Neff et al., 2005), and interventions resulting in modest enhancements in self-compassion could yield significant improvements in resilience.
Figure 4
IP, Resilience, Depression, and Anxiety Across Levels of Self-Compassion
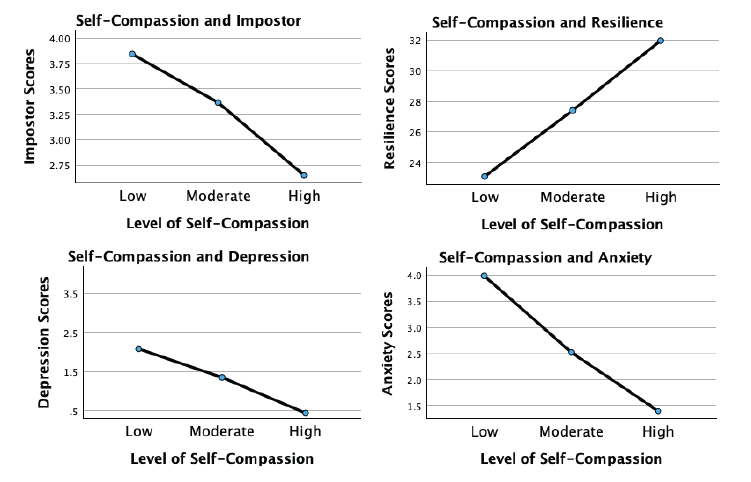
Although more variable, the association of self-compassion with anxiety and depression was similarly beneficial. Anxiety levels decreased significantly with each incremental increase in self-compassion, with the largest reduction occurring from low to moderate levels. This underscores the potential that even lower levels of self-compassion may still meaningfully alleviate anxiety. For depression, a significant decrease occurred across self-compassion levels, with the most substantial reduction noted as self-compassion increased from moderate to high. This suggests that self-compassion may interrupt the internal feedback loop of shame, self-criticism, and hopelessness that sustains depressive thinking in the context of IP.
These findings indicate that self-compassion is an important protective factor for developing counselor mental health. Contrary to expectations, even lower levels of self-compassion significantly relate to reduced IP, anxiety, and depression while increasing resilience (Luo et al., 2023). Integrating strategies to enhance self-compassion into counselor training programs could incrementally increase self-compassion, build emotional tolerance, and create a more stable internal environment from which resilience and well-being can emerge.
Implications and Future Directions for Counselor Development
Despite IP’s prevalence and association with diminished resilience and psychological distress, it remains underexamined in the counseling literature. Beyond a self-care strategy, self-compassion may build resilience and maintain mental health during and after counselor training. Integrating self-compassion into counselor education and early career development may cultivate a more supportive environment and provide counselors with evidence-based ways to manage IP and enhance resilience. Whereas, if left unaddressed, IP can lead to unnecessary distress, burnout, and professional attrition (Coaston & Lawrence, 2019; Ojeda, 2024).
Growing evidence suggests that self-compassion is vital for counselor development and ethical practice (Clarke et al., 2025; Coaston & Lawrence, 2019). The American Counseling Association (ACA) Code of Ethics (2014) emphasizes that professional counselors must engage in ongoing self-assessment and maintain their effectiveness through self-care practices. Similarly, CACREP (2023) standards require counselor education programs to integrate “self-care, self-awareness, and self-evaluation strategies for ethical and effective practice” (3.A.11.). Without meaningful coping strategies, IP can directly undermine these ethical mandates by diminishing well-being and distorting self-evaluation necessary for competent practice (Gadsby & Hohwy, 2024).
Regular engagement in reflective activities promoting balanced self-evaluation is essential to counselor development. If such exercises lack a compassionate focus, they may inadvertently reinforce impostor-related distortions by encouraging rumination and inaccurate self-critique. Matching reflective self-assessment with self-compassion practice may allow developing counselors to internalize feedback and move attention away from self-criticism and toward a growth mindset, transforming internal narratives dominated by IP (Warren et al., 2016).
Counselor educators and professional agencies can integrate self-compassion training through multiple pathways. Brief interventions, such as abbreviated versions of the Mindful Self-Compassion program (Germer & Neff, 2019), offer evidence-based approaches for enhancing counselor resilience. If limited by time and resources, supervisors and mentors can model self-compassionate practices by normalizing struggles, demonstrating constructive self-talk, and providing balanced growth-oriented feedback. The disclosure of faculty or supervisor IP experiences may be particularly powerful, reframing vulnerability and self-care as professional strengths rather than weaknesses.
Because IP is a contextual and environmentally fueled experience, counseling agencies and community mental health settings can foster organizational climates that prioritize compassion and collaboration and normalize challenges during the growth process (Coaston, 2019). When institutions reward openness, reflection, and learning from error, rather than perfection and productivity, developing counselors are more likely to engage in authentic self-assessment and seek help when struggling.
Early career peer support groups and compassion-focused initiatives can also counter the competitive, perfectionistic culture that sustains IP in professional practice (Clark et al., 2022). These approaches challenge the isolating belief that self-doubt is uniquely shameful, and foster community and belonging (Clarke & Guida, 2025; Hou & Skovholt, 2020). Future research should employ longitudinal and experimental designs to test targeted self-compassion interventions, clarifying causal relationships between self-compassion, resilience, and mental health outcomes in counselor education and professional contexts.
Clinical Supervision
Developmentally, the transition from classroom learning to applying theory and skills in clinical practice naturally provokes stress and anxiety (Skovholt & Trotter-Mathison, 2024). Although clinical supervision provides an ideal context for fostering openness and resilience (Coaston, 2019), experiencing IP may be a barrier to disclosing challenges because of emotional distress and fear of exposing perceived inadequacies (DeCandia Vitoria, 2021). Maintaining a façade of competence can compromise development and hinder the supervisory relationship (Thériault et al., 2009). These perfectionistic tendencies and IP are often motivated by context, suggesting that supervisors’ approaches may significantly alleviate these patterns.
Coaston (2019) provides a practical framework for applying self-compassion principles and philosophy in clinical supervision. Rooted in humanistic and developmental theory, this approach emphasizes that supervisors can accompany supervisees through the inevitable discomfort and vulnerability of professional growth by responding with compassion rather than judgment. By adopting a compassionate approach, the supervisory relationship can deepen, normalizing challenges and facilitating an authentic dialogue about IP-related uncertainties. In this way, clinical supervisors can address common cognitive and affective challenges.
A compassionate supervisory environment promotes balanced self-reflection and can reduce the shame-based fear of exposure that drives impostor defenses. This may allow supervisees to explore their conceptual skills openly, reframe unrealistic expectations, and persist despite challenges (Hou & Skovholt, 2020; Stoltenberg & McNeill, 2010). Future research can investigate how self-compassion contributes to the supervisory relationship, comfort with disclosure, and the integration of constructive feedback during supervised practice.
Clinical supervisors can also create a culture of shared vulnerability by modeling self-compassion and transparency about their own developmental struggles and self-doubt. This enables supervisees to internalize feedback and approach self-evaluation with less emotional reactivity. Enhancing collaboration within the alliance empowers supervisees to feel more competent in navigating their development independently (Skovholt & Trotter-Mathison, 2024). Given the potential benefits of this approach, we recommend that future research examine how embodiment and facilitation of self-compassion affect counselor development and well-being.
Limitations
Although the results of this study are encouraging, there are limitations. The cross-sectional design limits the data to a single point in time rather than showing fluctuations in self-compassion, IP, resilience, and mental health over time. Likewise, the present results do not establish causality. Replicating this study using a longitudinal approach can provide greater insight into these fluctuations. Furthermore, self-report measures introduce limitations such as social desirability bias and reliance on participant self-awareness. Likewise, individuals with a personal connection to IP may have been more likely to participate, potentially skewing results.
Participants were not asked about their matriculation status as counseling students, leaving their stage of development unknown. Future research should include clinical experience (i.e., none, practicum, internship) and matriculation status. This information would provide greater insight into how experience and counselor development interact with IP. The current study used a general IP assessment, while future research should use the Counselor Impostor Scale (CIS; Nguyen, 2023), which was published after data collection for this study was complete. The CIS is designed specifically for the counseling domain and could provide more nuanced insights. Additionally, because maladaptive coping strategies such as procrastination and perfectionism sustain IP, subsequent studies should explore these constructs, which could inform more targeted interventions.
Conclusion
The growth process during counselor training is inherently challenging and often gives rise to IP, which increases anxiety and depression while diminishing resilience. Self-compassion is a promising method for enhancing resilience and well-being, despite the presence of IP. Once learned, self-compassion is an accessible practice and relies on applying skills with which counselors are familiar, such as kindness and compassion toward themselves. The results of this study are encouraging and robust, suggesting that self-compassion can enhance resilience by supporting adaptive emotional regulation and fostering a growth-oriented mindset. Self-compassionate counselors can maintain their well-being despite experiencing IP. Importantly, the positive impact of self-compassion was consistent and significant even at lower levels, which is especially important given the prevalence and severity of IP among CITs. The findings support integrating self-compassion into counselor training and clinical supervision through modeling, training, and practice. This approach can provide effective coping for IP and improve resilience, mental health, and persistence.
Conflict of Interest and Funding Disclosure
The authors reported no conflict of interest
or funding contributions for the development
of this manuscript.
References
American Counseling Association. (2014). ACA code of ethics. https://www.counseling.org/docs/default-source/default- document-library/ethics/2014-aca-code-of-ethics.pdf
Beck, A. T., & Alford, B. A. (2009). Depression: Causes and treatment (2nd ed.). University of Pennsylvania Press.
Council for the Accreditation of Counseling and Related Educational Programs (2023). 2024 standards. https://www.cacrep.org/wp-content/uploads/2023/06/2024-Standards-Combined-Version-6.27.23.pdf
Clance, P. R. (1985). Clance Impostor Phenomenon Scale (CIPS). [Database record]. APA PsycTests. https://doi.org/10.1037/t11274-000
Clance, P., & Lawry, S. (2024). Impostor phenomenon: Origins and treatment. In K. Cokley (Ed.), The impostor phenomenon: Psychological research, theory, and interventions (pp. 17–43). American Psychological Association.
Clark, P., Holden, C., Russell, M., & Downs, H. (2022). The impostor phenomenon in mental health professionals: Relationships among compassion fatigue, burnout, and compassion satisfaction. Contemporary Family Therapy, 44(2), 185–197. https://doi.org/10.1007/s10591-021-09580-y
Clarke, B. J. (2024). Emerging adult life satisfaction and mental health: The mediating role of self-compassion and social support. Emerging Adulthood, 12(6), 1137–1147. https://doi.org/10.1177/21676968241279490
Clarke, B. J., & Guida, A. M. (2025). Self-compassion to community: The mediating effect of belonging on college student mental health and life satisfaction. Journal of College Student Mental Health. Advance online publication. https://doi.org/10.1080/28367138.2025.2552484
Clarke, B. J., & Hartley, M. T. (2025). Contemplative dispositions and mental health: The supportive role of self-compassion and mindfulness on college students’ resilience. Journal of College Student Mental Health, 39(1), 142–164. https://doi.org/10.1080/28367138.2024.2331931
Clarke, B. J., Hartley, M. T., & Button, C. (2025). Impostor phenomenon and counselor development: The critical role of self-compassion. Journal of Counseling & Development, 103(2), 149–160. https://doi.org/10.1002/jcad.12544
Coaston, S. C. (2019). Cultivating self-compassion within the supervision relationship. The Clinical Supervisor, 38(1), 79–96. https://doi.org/10.1080/07325223.2018.1525596
Coaston, S. C., & Lawrence, C. (2019). Integrating self-compassion across the counselor education curriculum. Journal of Creativity in Mental Health, 14(3), 292–305. https://doi.org/10.1080/15401383.2019.1610536
Cook, R. M., Fye, H. J., Jones, J. L., & Baltrinic, E. R. (2021). Self-reported symptoms of burnout in developing professional counselors: A content analysis. The Professional Counselor, 11(1), 31–45. https://doi.org/10.15241/rmc.11.1.31
Crego, A., Yela, J. R., Riesco-Matías, P., Gómez-Martínez, M. Á., & Vicente-Arruebarrena, A. (2022). The benefits of self-compassion in mental health professionals: A systematic review of empirical research. Psychology Research and Behavior Management, 15, 2599–2620. https://doi.org/10.2147/PRBM.S359382
DeCandia Vitoria, A. (2021). Experiential supervision: Healing impostor phenomenon from the inside out. The Clinical Supervisor, 40(2), 200–217. https://doi.org/10.1080/07325223.2020.1830215
Delaney, M. C. (2018). Caring for the caregivers: Evaluation of the effect of an eight-week pilot Mindful Self-Compassion (MSC) training program on nurses’ compassion fatigue and resilience. PLoS ONE, 13(11), e0207261. https://doi.org/10.1371/journal.pone.0207261
Fairchild, A. J., & McDaniel, H. L. (2017). Best (but oft-forgotten) practices: Mediation analysis. The American Journal of Clinical Nutrition, 105(6), 1259–1271. https://doi.org/10.3945/ajcn.117.152546
Fritz, M. S., & MacKinnon, D. P. (2007). Required sample size to detect the mediated effect. Psychological Science, 18(3), 233–239. https://doi.org/10.1111/j.1467-9280.2007.01882.x
Gadsby, S., & Hohwy, J. (2024). Negative performance evaluation in the impostor phenomenon. Current Psychology, 43, 9300–9308. https://doi.org/10.1007/s12144-023-05030-0
Garba, R., Coleman, C., & Kelley, T. (2024). The impostor phenomenon and mental health. In K. Cokley (Ed.), The impostor phenomenon: Psychological research, theory, and interventions (pp. 61–79). American Psychological Association.
Gerber, Z., & Anaki, D. (2021). The role of self-compassion, concern for others, and basic psychological needs in the reduction of caregiving burnout. Mindfulness, 12, 741–750. https://doi.org/10.1007/s12671-020-01540-1
Germer, C., & Neff, K. (2019). Teaching the Mindful Self-Compassion program: A guide for professionals. Guilford.
Gignac, G. E., & Szodorai, E. T. (2016). Effect size guidelines for individual differences researchers. Personality and Individual Differences, 102, 74–78. https://doi.org/10.1016/j.paid.2016.06.069
Hayes, A. F. (2022). Introduction to mediation, moderation, and conditional process analysis: A regression-based approach (3rd ed.). Guilford.
Hou, J.-M., & Skovholt, T. M. (2020). Characteristics of highly resilient therapists. Journal of Counseling Psychology, 67(3), 386–400. https://doi.org/10.1037/cou0000401
Housenecht, A., & Swank, J. (2022). Motivation, belonging, and support: Examining persistence in counseling programs. Teaching and Supervision in Counseling, 4(2), Article 3. https://doi.org/10.7290/tsc04g4iv
Khubchandani, J., Brey, R., Kotecki, J., Kleinfelder, J., & Anderson, J. (2016). The psychometric properties of PHQ-4 depression and anxiety screening scale among college students. Archives of Psychiatric Nursing, 30(4), 457–462. https://doi.org/10.1016/j.apnu.2016.01.014
Kroenke, K., Spitzer, R. L., Williams, J. B. W., & Löwe, B. (2009). An ultra-brief screening scale for anxiety and depression: The PHQ–4. Psychosomatics, 50(6), 613–621.
Liu, S., Wei, M., & Russell, D. (2023). Effects of a brief self-compassion intervention for college students with impostor phenomenon. Journal of Counseling Psychology, 70(6), 711–724. https://doi.org/10.1037/cou0000703
Luo, X., Che, X., & Lei, Y. (2023). Characterizing the effects of self-compassion interventions on anxiety: Meta-analytic evidence from randomized controlled studies. Journal of Contextual Behavioral Science, 30, 132–141. https://doi.org/10.1016/j.jcbs.2023.10.004
Mak, K. K. L., Kleitman, S., & Abbott, M. J. (2019). Impostor phenomenon measurement scales: A systematic review. Frontiers in Psychology, 10, 671. https://doi.org/10.3389/fpsyg.2019.00671
Martin, A. J., & Marsh, H. W. (2006). Academic resilience and its psychological and educational correlates: A construct validity approach. Psychology in the Schools, 43(3), 267–281. https://doi.org/10.1002/pits.20149
Neff, K. (2003). Self-compassion: An alternative conceptualization of a healthy attitude toward oneself. Self and Identity, 2(2), 85–101. https://doi.org/10.1080/15298860309032
Neff, K. D. (2023). Self-compassion: Theory, method, research, and intervention. Annual Review of Psychology, 74, 193–218. https://doi.org/10.1146/annurev-psych-032420-031047
Neff, K. D., Hsieh, Y. P., & Dejitterat, K. (2005). Self-compassion, achievement goals, and coping with academic failure. Self and Identity, 4(3), 263–287. https://doi.org/10.1080/13576500444000317
Neff, K. D., Tóth-Király, I., Yarnell, L. M., Arimitsu, K., Castilho, P., Ghorbani, N., Guo, H. X., Hirsch, J. K., Hupfeld, J., Hutz, C. S., Kotsou, I., Lee, W. K., Montero-Marin, J., Sirois, F. M., de Souza, L. K., Svendsen, J. L., Wilkinson, R. B., & Mantzios, M. (2019). Examining the factor structure of the Self-Compassion Scale in 20 diverse samples: Support for use of a total score and six subscale scores. Psychological Assessment, 31(1), 27–45. https://doi.org/10.1037/pas0000629
Nguyen, L. T. (2023). Development and validation of the Counseling Impostor Scale (Doctoral dissertation). Texas A&M University–Corpus Christi.
Ojeda, L. (2024). Impostor phenomenon and burnout. In K. Cokley (Ed.), The impostor phenomenon: Psychological research, theory, and interventions (pp. 81–110). American Psychological Association.
Pákozdy, C., Askew, J., Dyer, J., Gately, P., Martin, L., Mavor, K. I., & Brown, G. R. (2023). The impostor phenomenon and its relationship with self-efficacy, perfectionism, and happiness in university students. Current Psychology, 43, 1–10. https://doi.org/10.1007/s12144-023-04672-4
Patzak, A., Kollmayer, M., & Schober, B. (2017). Buffering impostor feelings with kindness: The mediating role of self-compassion between gender-role orientation and the impostor phenomenon. Frontiers in Psychology, 8, Article 1289. https://doi.org/10.3389/fpsyg.2017.01289
Raes, F., Pommier, E., Neff, K. D., & Van Gucht, D. (2011). Construction and factorial validation of a short form of the Self-Compassion Scale. Clinical Psychology & Psychotherapy, 18(3), 250–255. https://doi.org/10.1002/cpp.702
Richardson, J. T. E. (2011). Eta squared and partial eta squared as measures of effect size in educational research. Educational Research Review, 6(2), 135–147. https://doi.org/10.1016/j.edurev.2010.12.001
Roskowski, J. C. R. (2010). Impostor phenomenon and counseling self-efficacy: The impact of impostor feelings (Doctoral dissertation). Ball State University.
Skovholt, T. M., & Trotter-Mathison, M. (2024). The elevated stressors of the novice practitioner. In T. M. Skovholt & M. Trotter-Mathison (Eds.), The resilient practitioner: Burnout and compassion fatigue prevention and self-care strategies for the helping professions (4th ed., pp. 42–68). Taylor & Francis.
Stoltenberg, C. D., & McNeill, B. W. (2010). IDM supervision: An integrative developmental model for supervising counselors and therapists (3rd ed.). Routledge.
Tabachnick, B. G., & Fidell, L. S. (2019). Using multivariate statistics (7th ed.). Pearson.
Thériault, A., Gazzola, N., & Richardson, B. (2009). Feelings of incompetence in developing therapists: Consequences, coping, and correctives. Canadian Journal of Counselling, 43(2), 105–119.
Tigranyan, S., Byington, D. R., Liupakorn, D., Hicks, A., Mathis, M., & Rodolfa, E. (2021). Factors related to the impostor phenomenon in psychology doctoral students. Training and Education in Professional Psychology, 15(4), 298–305. https://doi.org/10.1037/tep0000321
Wang, B., Andrews, W., Bechtoldt, M. N., Rohrmann, S., & de Vries, R. E. (2022). Validation of the short Clance Impostor Phenomenon Scale (CIPS-10). European Journal of Psychological Assessment, 40(2), 158–168. https://doi.org/10.1027/1015-5759/a000747
Warren, R., Smeets, E., & Neff, K. (2016). Self-criticism and self-compassion: Risk and resilience. Current Psychiatry, 15(12), 18–33. https://self-compassion.org/wp-content/uploads/2016/12/Self-Criticism.pdf
Webb, R. E., & Rosenbaum, P. (2019). Resilience and thinking perpendicularly: A meditation or morning jog. Journal of College Student Psychotherapy, 33(1), 75–88. https://doi.org/10.1080/87568225.2018.1449687
Brian J. Clarke, PhD, NCC, LAC, is an assistant professor at the University of Arizona. Michael T. Hartley, PhD, CRC, is a professor at the University of Arizona. Austin M. Guida, PhD, NCC, LAC, is an assistant professor at Northern Arizona University. Correspondence may be addressed to Brian J. Clarke, Department of Disability and Psychoeducational Studies, College of Education, 1430 E. 2nd Street, Room 422, Tucson, AZ, 85721-0069, bclarke14@arizona.edu.

